- Who May Be Eligible for Nonsurgical Treatment for Prostate Cancer?
- Ayurvedic Nonsurgical Treatment for Prostate Cancer
- Varuna–Kanchanara Avaleha for Nonsurgical Prostate Cancer Treatment
- Measuring Nonsurgical Treatment for Prostate Cancer
- Evidence for Nonsurgical Treatment for Prostate Cancer
- Questions Before Nonsurgical Treatment for Prostate Cancer
- Nonsurgical Treatment for Prostate Cancer Review
- FAQs
- References
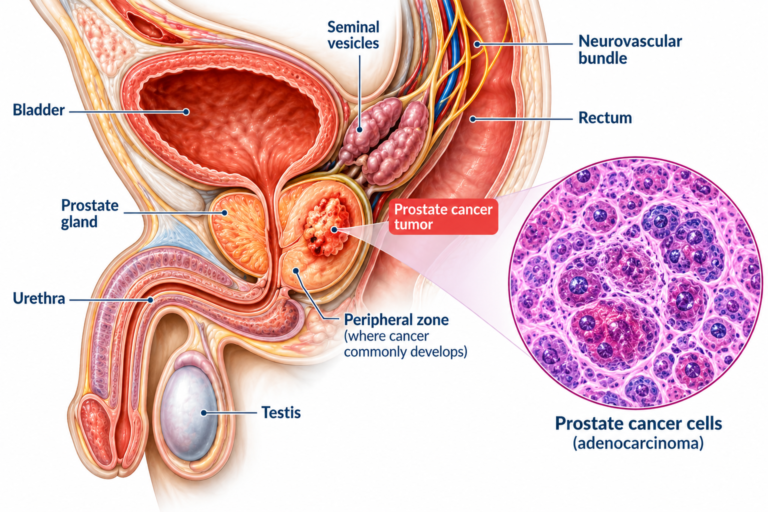
Who May Be Eligible for Nonsurgical Treatment for Prostate Cancer?
Nonsurgical treatment for prostate cancer may be appropriate for men with low-risk localised disease, carefully selected favourable intermediate-risk cancer, patients who prefer radiotherapy to prostate removal, men whose medical condition increases operative risk, and patients with recurrent, locally advanced or metastatic disease for whom radiation or systemic treatment is more appropriate than prostatectomy. Eligibility cannot be determined from age, PSA or symptoms alone. It requires combined interpretation of the biopsy Grade Group, amount and location of cancer, PSA density and trend, clinical stage, magnetic resonance imaging, staging scans, general health, estimated life expectancy, baseline urinary function and the patient’s treatment priorities [4–10].
Table: Who May Be Eligible for Nonsurgical Treatment for Prostate Cancer?
| Patient profile | Nonsurgical option to discuss | Key eligibility factors |
|---|---|---|
| Very-low- or low-risk localized prostate cancer | Active surveillance | Grade Group 1, limited cancer volume, favorable MRI, PSA pattern, reliable follow-up |
| Selected favorable intermediate-risk cancer | Active surveillance or radiotherapy | Selected Grade Group 2, limited pattern 4, low biopsy burden, favorable imaging |
| Localized cancer when surgery is declined | EBRT, SBRT or brachytherapy | Stage, urinary function, prostate anatomy, bowel health, treatment goals |
| High-risk localized cancer | Radiotherapy plus hormone therapy | Grade Group, PSA, clinical stage, nodal risk, fitness |
| Locally advanced prostate cancer | Radiotherapy plus systemic treatment | Local extension, lymph-node risk, imaging, general health |
| Older or medically frail patient | Watchful waiting or adapted active treatment | Life expectancy, frailty, symptoms, competing illnesses |
| PSA recurrence after prostatectomy | Salvage radiotherapy ± hormone therapy | PSA level and trend, pathology, margins, imaging |
| Selected recurrence after radiotherapy | Salvage focal therapy, brachytherapy or systemic treatment | Site of recurrence, biopsy, imaging, previous radiation |
| Metastatic prostate cancer | Hormone and systemic treatment ± radiotherapy | Disease burden, hormone sensitivity, symptoms, molecular findings |
| Selected patient seeking Ayurvedic care | Individualized Ayurvedic plan with objective monitoring | Pathology, stage, PSA, imaging, organ function, current oncology treatment |
Men With Very-Low- or Low-Risk Localised Prostate Cancer
Men with Grade Group 1 prostate cancer confined to the prostate are often the strongest candidates for active surveillance. This pathway may be appropriate when the biopsy shows Gleason 3+3 disease, only a limited number of cores are involved, cancer occupies a small proportion of each positive core, magnetic resonance imaging does not show extensive or aggressive disease, and the PSA findings are consistent with a low-risk tumour [5,8,10].
Table: Active Surveillance Eligibility for Prostate Cancer
| Clinical factor | More favorable for active surveillance | Requires greater caution |
|---|---|---|
| Grade Group | Grade Group 1 | Selected Grade Group 2 only |
| Gleason pattern 4 | None | Preferably less than 10% in selected GG2 cases |
| PSA | Usually below 10 ng/mL in classic criteria | Higher PSA requires contextual assessment |
| Clinical stage | cT1c–cT2a | Greater local extension reduces suitability |
| PSA density | Lower values are more reassuring | Increasing/high PSA density warrants closer review |
| Biopsy extent | Small-volume disease | Multiple heavily involved cores |
| Grade Group 2 cores | Limited | EAU example: no more than 3 positive GG2 cores |
| Cancer per core | Limited | EAU example: no more than 50% involvement per GG2 core |
| MRI | Low disease extent | Progressing or extensive lesion |
| Cribriform/intraductal disease | Absent | Presence generally argues against surveillance |
A PSA below 10 ng/mL is commonly associated with low-risk disease, but it is not an independent eligibility rule. PSA can be affected by prostate volume, benign enlargement, urinary infection, inflammation, recent instrumentation, ejaculation and medicines such as finasteride or dutasteride. PSA density, calculated by comparing PSA with prostate volume, and the pattern of change over time can provide more clinically useful information than one isolated result [8,10].
Active surveillance is an organised treatment strategy rather than an absence of care. It usually involves scheduled PSA testing, clinical review, repeat magnetic resonance imaging and further biopsy when required. The purpose is to delay or avoid treatment-related urinary, sexual and bowel effects while retaining the opportunity for curative treatment if the cancer shows clinically meaningful progression [5,6,8,10].
A patient must also be willing and able to complete long-term monitoring. Active surveillance may be unsafe when follow-up is irregular, magnetic resonance imaging or repeat biopsy cannot be obtained, or the patient is unlikely to act on evidence of progression. Anxiety that substantially affects daily life may also justify discussing definitive radiotherapy or surgery even when surveillance remains medically reasonable.
Long-term randomised evidence shows that prostate-cancer-specific mortality can remain low with monitoring, surgery or radiotherapy in appropriately selected localised disease. However, the ProtecT trial also found more clinical progression and metastatic disease in the monitoring group, demonstrating why surveillance must include reliable testing and predefined triggers for treatment rather than passive observation [2].
Carefully Selected Men With Favourable Intermediate-Risk Disease
Some men with favourable intermediate-risk prostate cancer may be considered for active surveillance, although eligibility is narrower than for Grade Group 1 disease. The most suitable candidates generally have Grade Group 2 cancer, a small quantity of Gleason pattern 4, limited tumour involvement in biopsy cores, disease confined to the prostate and reassuring magnetic resonance imaging findings [5,8,10].
European guidance describes selected Grade Group 2 candidates as men who may have less than 10% Gleason pattern 4, PSA below 10 ng/mL, clinical stage no higher than T2a, low disease extent on imaging, no more than three Grade Group 2-positive biopsy cores and no more than 50% cancer involvement in an individual core. These are selection examples rather than universal rules, and different multidisciplinary teams may apply somewhat different thresholds [10].
The distinction between Gleason 3+4 and 4+3 is clinically important. Gleason 3+4 corresponds to Grade Group 2 and may contain only a limited component of pattern 4, whereas Gleason 4+3 corresponds to Grade Group 3 and has a greater proportion of the more aggressive pattern. Routine surveillance is substantially less suitable when pattern 4 is extensive, Grade Group 3 or higher is present, or imaging suggests disease beyond the prostate [5,10].
Cribriform architecture and intraductal carcinoma are adverse pathological findings that can materially change eligibility. A patient whose report does not mention these features may benefit from specialist genitourinary pathology review before choosing surveillance, particularly when Grade Group 2 disease is being considered for conservative management [10].
In the UK, many men with Cambridge Prognostic Group 1 or 2 localised cancer may be considered for active surveillance. Selected Cambridge Prognostic Group 3 patients may also discuss surveillance when they wish to delay immediate radical treatment, but the greater progression risk must be clearly understood. Cambridge Prognostic Group 4 or 5 disease generally requires an active treatment discussion rather than routine surveillance [5,9].
Men Seeking Curative Treatment Without Prostate Removal
A man may be eligible for curative nonsurgical treatment even when active surveillance is unsuitable. External-beam radiotherapy, stereotactic body radiotherapy and brachytherapy can treat localised prostate cancer without removing the prostate. These options should be discussed with a radiation oncologist before a patient concludes that radical prostatectomy is the only potentially curative treatment [4–9].
External-beam radiotherapy may be used for low-, intermediate- or high-risk localised disease and for selected locally advanced cancers. Treatment planning considers the prostate, seminal vesicles, possible lymph-node risk, previous pelvic treatment, bowel anatomy, hip movement, urinary function and whether hormone treatment should be added. The recommended radiation schedule and treatment field depend on the patient’s risk group rather than a preference for the shortest course alone [4,5,8–10].
Stereotactic body radiotherapy delivers a higher radiation dose per treatment over fewer sessions. The PACE-B randomised trial found that five-fraction stereotactic radiotherapy was noninferior to longer radiotherapy schedules for biochemical or clinical failure in selected men with localised low- to intermediate-risk cancer. Eligibility still requires specialist assessment because baseline urinary symptoms, prostate anatomy, previous procedures and expected toxicity can affect suitability [3].
Brachytherapy places radioactive sources within or close to the prostate. It avoids prostate removal but remains an invasive procedure requiring anaesthesia and careful treatment planning. Men with substantial urinary obstruction, a very large prostate, previous extensive transurethral prostate surgery, significant bleeding risk or anatomy that prevents accurate implantation may require another treatment approach. In higher-risk disease, brachytherapy may sometimes be combined with external-beam radiotherapy and hormone treatment rather than used alone [4,5,8,10].
High-intensity focused ultrasound, cryotherapy and other focal ablation techniques may be considered for selected men with a clearly localised and targetable lesion. Appropriate assessment generally requires high-quality magnetic resonance imaging, targeted and systematic biopsy information, confirmation that clinically significant disease is not present elsewhere in the gland and access to long-term follow-up. Because prostate cancer is frequently multifocal and long-term comparative evidence remains less mature than for surgery or radiotherapy, focal treatment should not be presented as a routine substitute for established whole-gland treatment [4,7,9,10].
Patients Whose Health Makes Surgery Less Suitable
Nonsurgical treatment may be particularly relevant when radical prostatectomy carries an increased anaesthetic, cardiovascular, respiratory, bleeding or recovery risk. Important considerations include significant heart or lung disease, previous stroke, frailty, severe mobility limitation, poorly controlled diabetes, anticoagulant use, substantial obesity, previous complex abdominal or pelvic surgery and other illnesses that may impair postoperative recovery [4,5,8,10].
Chronological age should not be used as the sole reason to recommend or exclude surgery. A physically independent older man with a substantial life expectancy and aggressive localised cancer may still benefit from curative treatment. Conversely, a younger patient with serious comorbidity may obtain more net benefit from radiotherapy, surveillance or symptom-directed management. Functional status, competing health risks and estimated life expectancy are more informative than age alone [4,5,8,10].
Radiotherapy is not automatically safe merely because it avoids an operation. Severe baseline urinary obstruction, inflammatory bowel disease, previous pelvic radiation, inability to remain in the treatment position or limited access to repeated appointments may affect feasibility. The patient’s operative risk and radiation risk should therefore be compared rather than assuming that one option is inherently suitable.
Men with substantial frailty or a life expectancy unlikely to be affected by slow-growing prostate cancer may be considered for watchful waiting. Unlike active surveillance, which preserves the intention to introduce curative treatment if the cancer changes, watchful waiting usually prioritises symptom control and avoidance of burdensome intervention. Hormone treatment, palliative radiotherapy or procedures to relieve urinary obstruction may be introduced if symptoms develop [4,8–10].
Men With High-Risk or Locally Advanced Prostate Cancer

High-risk or locally advanced prostate cancer can often be treated without prostatectomy, but it usually requires active multimodal treatment rather than surveillance. External-beam radiotherapy combined with androgen-deprivation therapy is an established approach for many men whose cancer has a high Grade Group, PSA above the low-risk range, extracapsular extension, seminal-vesicle involvement or other adverse features [4,5,9,10].
Avoiding surgery in this setting does not mean choosing a gentler or less serious treatment. Radiotherapy may include the prostate, seminal vesicles and selected pelvic lymph nodes, while hormone treatment may continue for a prolonged period. Some patients may also require treatment intensification based on stage, nodal risk, disease burden, fitness and contemporary oncology guidance [4,5,10].
Before treatment begins, men should be assessed for cardiovascular disease, diabetes, metabolic risk, bone density, fracture risk, muscle loss, sexual health and baseline fatigue because androgen-deprivation therapy can influence each of these areas. Exercise, adequate nutrition, bone-health management and monitoring of blood pressure, glucose and lipids should form part of the treatment plan rather than being addressed only after complications appear.
A patient with Grade Group 4 or 5 disease, clinical T3 or T4 cancer, regional lymph-node involvement or rapidly progressive findings should not delay specialist treatment while pursuing a surveillance-only strategy. Radiotherapy and systemic treatment may still provide a nonsurgical pathway, but the treatment intent, expected duration and realistic outcome should be defined before therapy starts [4,5,9,10].
Men With Recurrent Prostate Cancer
A man whose PSA rises after radical prostatectomy may be eligible for salvage radiotherapy to the prostate bed, sometimes with treatment of the pelvic lymph nodes and temporary hormone therapy. Eligibility depends on the postoperative pathology, surgical margins, original Grade Group, PSA level and rate of rise, interval since surgery and findings on contemporary imaging. Salvage treatment is generally more likely to control disease when recurrence is identified and treated before the PSA becomes substantially elevated [4,6,10].
A negative PSMA PET/CT scan does not always exclude microscopic local recurrence when PSA is low. The radiation oncologist may still recommend early salvage radiotherapy based on the PSA pattern and surgical pathology. Conversely, clear distant metastases on imaging may shift the treatment priority toward systemic therapy, metastasis-directed radiation or a combined approach.
Local recurrence after previous radiotherapy requires a different assessment. Selected patients may be considered for salvage brachytherapy, cryotherapy, high-intensity focused ultrasound, repeat external-beam treatment or, less commonly, salvage surgery. These treatments can cause substantial urinary, rectal and sexual toxicity, so recurrent cancer should be confirmed where appropriate and its location mapped before another local procedure is selected [4,9,10].
Men with a small number of metastatic lesions may occasionally be assessed for stereotactic radiation directed at individual sites. This approach may delay progression or the need for a change in systemic treatment in selected circumstances, but it does not make widespread metastatic disease equivalent to localised cancer. PSA response, imaging response and the appearance of new lesions remain essential measures of outcome.
Men With Metastatic Prostate Cancer
For metastatic prostate cancer, prostate removal is not usually the principal treatment. Most patients require androgen-deprivation therapy combined, when appropriate, with an androgen-receptor pathway inhibitor, chemotherapy or another systemic treatment. The recommended combination depends on whether the cancer is newly diagnosed or recurrent, hormone-sensitive or castration-resistant, symptomatic or asymptomatic, and low-volume or high-volume [4,10].
Radiotherapy to the prostate may be considered in selected men with newly diagnosed low-volume metastatic disease, while palliative radiotherapy can relieve pain, reduce the risk of complications from bone lesions or treat local symptoms. Patients with more extensive disease generally require systemic control rather than treatment directed only at the prostate.
Molecular testing may identify selected patients who could benefit from targeted treatment. Tumour testing and, where appropriate, inherited genetic testing can assess alterations in DNA-repair pathways and other clinically relevant biomarkers. Results may influence treatment choices, inform clinical-trial eligibility and identify possible implications for close relatives.
New back pain, leg weakness, numbness, difficulty walking, loss of bladder or bowel control, inability to pass urine, severe bone pain or rapidly worsening general health requires urgent medical assessment. These symptoms may indicate spinal cord compression, urinary obstruction, fracture or another complication that cannot safely wait for a routine consultation.
Patients Who Are Usually Unsuitable for Routine Active Surveillance

Routine active surveillance is generally inappropriate when the biopsy shows Grade Group 3, 4 or 5 cancer, extensive Gleason pattern 4, any pattern 5, intraductal carcinoma, cribriform architecture or extensive tumour involvement. It is also less suitable when imaging suggests extracapsular extension, seminal-vesicle invasion, lymph-node disease or distant metastasis [5,10].
A rapidly changing PSA may raise concern, but PSA kinetics should not be interpreted without reviewing prostate volume, infection, testosterone, laboratory variation and imaging. A PSA increase should usually trigger clinical reassessment and further investigation rather than an automatic declaration of treatment failure or an immediate treatment change based on the blood result alone.
Progression during surveillance may be indicated by pathological upgrading, increasing tumour volume on repeat biopsy, magnetic resonance imaging progression, development of disease outside the prostate or new cancer-related symptoms. These findings should prompt reconsideration of curative radiotherapy, surgery or another appropriate treatment while the disease remains controllable.
Being unsuitable for active surveillance does not mean that prostatectomy is mandatory. A patient may still be eligible for definitive radiotherapy, radiotherapy combined with hormone treatment, brachytherapy, systemic treatment or another nonsurgical strategy. The clinically important distinction is between surveillance and active nonsurgical treatment, not simply between surgery and no surgery.
Clinical Information Required Before Eligibility Can Be Decided
The complete prostate-biopsy report is essential. It should identify the Gleason score, Grade Group, number of positive cores, percentage or length of cancer in each core, location of involved samples, proportion of Gleason pattern 4 and any cribriform, intraductal or other adverse features. When treatment decisions depend on subtle pathological distinctions, review by an experienced genitourinary pathologist may alter risk classification.
The PSA record should include dated results rather than only the latest value. Prostate volume, PSA density, recent infection, urinary retention, catheterisation, biopsy timing and exposure to finasteride, dutasteride or hormone therapy are needed for correct interpretation. Testosterone should also be reviewed in men receiving or recovering from androgen-deprivation therapy because PSA cannot be interpreted in the same way when testosterone remains suppressed.
Multiparametric magnetic resonance imaging should be reviewed for lesion size, PI-RADS category, location, proximity to the urethra or neurovascular structures, possible extracapsular extension, seminal-vesicle involvement and evidence of multifocal disease. The images themselves may provide information not fully conveyed in the written report, particularly when focal treatment or surveillance is being considered.
PSMA PET/CT, computed tomography, bone scanning or other staging tests may be required according to the patient’s risk and previous treatment. These investigations help distinguish disease confined to the prostate from regional or distant spread. They should be ordered and interpreted according to the clinical setting because not every low-risk patient requires extensive staging.
Baseline urinary, bowel and sexual function can materially influence the treatment choice. Urinary frequency, urgency, nocturia, weak stream, incomplete emptying, urinary retention, incontinence, previous transurethral prostate procedures, rectal disease and erectile function should be documented before treatment. Without this baseline, later symptoms may be incorrectly attributed entirely to treatment.
The medical assessment should include cardiovascular and respiratory health, diabetes, kidney and liver function, bone health, mobility, frailty, current medicines, anticoagulants, antiplatelet drugs and supplements. These factors can affect anaesthesia, radiotherapy planning, hormone-treatment tolerance, bleeding risk and potential herb–drug interactions.
Patient preference becomes clinically meaningful only after the realistic alternatives are understood. Men should be told the intended goal of each option, probability of needing later treatment, follow-up burden and potential effects on urinary continence, sexual function, bowel function, fertility, energy, metabolic health and quality of life. Declining surgery does not establish eligibility for surveillance, just as accepting radiotherapy does not remove the need for accurate staging.
Eligibility Pathways in the USA, UK, Canada, Singapore and Australia
In the USA, patients are commonly counselled using low-, favourable intermediate-, unfavourable intermediate- and high-risk categories. Men considering treatment without surgery should obtain a radiation-oncology opinion in addition to a urological opinion, particularly when external-beam radiation therapy, stereotactic body radiation therapy or brachytherapy could provide curative treatment. Insurance-network access, treatment-centre experience and availability of advanced imaging can affect the practical pathway, but they should not replace risk-based clinical selection [4].
In the UK, Cambridge Prognostic Group classification is commonly used alongside Grade Group, PSA and clinical stage. Active surveillance is generally considered for Cambridge Prognostic Group 1 and 2 disease and may be discussed in selected Cambridge Prognostic Group 3 cases. Men with Cambridge Prognostic Group 4 or 5 disease are more likely to require radical radiotherapy with hormone treatment, surgery or another active pathway [5,9].
In Canada, localised prostate cancer may be managed with active surveillance, surgery or radiation therapy, while locally advanced disease is frequently treated with radiation and hormone therapy. Patients considering nonsurgical treatment should review access to radiation oncology, brachytherapy, magnetic resonance imaging, repeat biopsy and long-term PSA monitoring within their provincial healthcare pathway [6].
In Singapore, suitability for surveillance, radiation therapy or selected ablation procedures is usually determined through specialist evaluation of pathology, imaging and general health. Focal treatments may be available in selected centres, but a patient should ask whether the proposed procedure is intended to treat the whole gland or only an identified lesion, how untreated areas will be monitored and what salvage options remain if cancer recurs [7].
In Australia, men with localised or locally advanced prostate cancer should ideally discuss their case with both a urologist and radiation oncologist before choosing treatment. Active surveillance is widely recognised for appropriate low-risk disease, while external-beam radiotherapy and brachytherapy provide nonsurgical definitive options. Geographic access, travel burden and the availability of experienced treatment centres should be considered when choosing a schedule that still provides guideline-consistent care [8].
International patients seeking a remote review should provide original pathology, dated PSA results, magnetic resonance imaging, available PSMA PET/CT or other staging studies, treatment history, current prescriptions and recent laboratory tests. A records-based review can clarify the apparent risk category and identify missing investigations, but it cannot replace urgent local assessment, physical examination, biopsy, emergency treatment or procedures that must be performed in the patient’s country.
Who May Be Considered for an Individualised Ayurvedic Nonsurgical Plan?
An individualised Ayurvedic plan may be considered after the cancer diagnosis, Grade Group, stage, PSA history, imaging and current oncology recommendation have been established. The clinical context differs substantially between a man with low-volume Grade Group 1 cancer under active surveillance, a patient receiving curative radiotherapy, a man taking long-term hormone treatment and someone with metastatic disease. The same formulation, dose and treatment objective should not be applied across these groups.
Men under active surveillance may be considered for an Ayurvedic programme only when they remain enrolled in objective oncological monitoring. Treatment assessment should include serial PSA interpreted with prostate volume and testosterone where relevant, magnetic resonance imaging, repeat biopsy when clinically indicated, urinary function and laboratory safety results. Improvement in urinary frequency, flow, sleep, appetite or energy can be valuable, but symptom improvement alone does not establish cancer regression.
Patients receiving radiotherapy require review for possible effects on bowel function, urinary irritation, hydration, nutrition, blood counts and medicine interactions. Herbal or herbo-mineral medicines should not be started, stopped or intensified around radiotherapy without coordination because the safety of individual combinations cannot be assumed from traditional use alone.
Men receiving androgen-deprivation therapy require particular attention to fatigue, muscle loss, bone density, glucose, lipids, cardiovascular risk, sleep and sexual wellbeing. Ayurvedic care may be individualised around these concerns, but it should not include indiscriminate use of products intended to increase testosterone because androgen stimulation may conflict with the oncological purpose of hormone treatment.
The broader guide, Ayurvedic Treatment for Prostate Cancer, explains the physician-designed Varuna–Kanchanara Rasayana Avaleha, in which Rasayana denotes a classical restorative approach and Avaleha denotes a semisolid oral preparation. Eligibility for such a formulation should depend on pathology, stage, urinary findings, digestive tolerance, liver and kidney function, current medicines and the ability to complete objective follow-up rather than on the diagnosis of prostate cancer alone.
The pillar guide also examines a peer-reviewed case report involving a 45-year-old man with biopsy-confirmed Gleason 3+3, Grade Group 1, clinical T1 prostate adenocarcinoma and a very small right mid-prostate lesion. The report described regression on post-treatment biopsy after nine months of exclusive Ayurvedic treatment and long-term cancer-free follow-up reported by the authors [1]. This is a documented individual outcome, but the patient’s low-volume, low-risk disease and the single-case design mean that it cannot establish a general response rate or predict the outcome of intermediate-, high-risk or metastatic prostate cancer.
A patient seeking a disease-directed Ayurvedic nonsurgical plan should therefore submit the full biopsy report, pathology slides when review is needed, dated PSA history, prostate volume, magnetic resonance imaging, staging scans, current treatment plan, complete medicine and supplement list, urinary history and recent blood tests. Eligibility should be reconsidered whenever there is pathological upgrading, radiological progression, a clinically significant PSA change, new lymph-node or bone disease, urinary obstruction, unexplained weight loss, increasing pain or another finding that changes the balance between surveillance and active oncology treatment [1,4,5,10].
Ayurvedic Nonsurgical Treatment for Prostate Cancer

A published case of nonsurgical treatment for prostate cancer provides clinically documented evidence that an individualised Ayurvedic approach may warrant consideration in carefully selected patients. The report involved biopsy-confirmed, clinically localised prostate adenocarcinoma and assessed outcome through PSA monitoring, repeat biopsy and long-term follow-up rather than relying only on changes in urinary symptoms or general wellbeing [1].
Baseline Diagnosis and Clinical Risk
The patient was a 45-year-old Indian man living in the United States who had a PSA level of 11.2 ng/mL. Prostate biopsy confirmed adenocarcinoma with a Gleason score of 3+3, corresponding to Grade Group 1. The cancer was reported as clinical T1 disease, with a small malignant focus in the right mid-prostate [1].
These findings indicated low-grade, clinically localised disease, but the PSA above 10 ng/mL required careful interpretation. A Gleason 3+3 tumour generally behaves less aggressively than cancers containing Gleason patterns 4 or 5, yet Grade Group alone cannot determine whether surveillance or another nonsurgical pathway is appropriate. PSA density, prostate volume, biopsy extent, magnetic resonance imaging findings, clinical stage and the presence of adverse pathological features must also be considered [4,10].
The patient’s age was clinically important because a younger man may live long enough for untreated or inadequately monitored prostate cancer to progress. A nonsurgical approach in this setting therefore required objective follow-up capable of detecting persistent disease, pathological upgrading or progression while curative treatment options remained available.
Individualised Ayurvedic Treatment
The case report described exclusive Ayurvedic treatment delivered under physician supervision rather than the unsupervised use of commercially available herbal products. The treatment was individualised according to the patient’s diagnosis, constitutional assessment, digestive function, urinary findings and overall clinical condition [1].
The therapeutic approach incorporated Rasayana, a classical Ayurvedic strategy intended to support tissue resilience, recovery and long-term physiological stability. Rasayana should not be interpreted as equivalent to chemotherapy, immunotherapy or any single modern pharmacological category. Its clinical application depends on the selected medicines, preparation methods, dosage, treatment duration and the patient’s capacity to tolerate and metabolise the formulation.
An individual case cannot establish that the same medicines or doses are appropriate for every patient with prostate cancer. A man with Grade Group 1 localised disease has a fundamentally different clinical requirement from a patient with Grade Group 4 cancer, lymph-node involvement, bone metastases, urinary obstruction or progression during hormone treatment. Ayurvedic prescriptions must therefore remain stage-specific, risk-specific and compatible with the patient’s current oncology plan.
Objective Findings After Treatment
A repeat prostate biopsy performed after approximately nine months of treatment reportedly did not identify the previously documented malignant focus. This finding provided stronger evidence of local disease regression than symptom improvement or a PSA change alone because the original diagnosis and subsequent response were both evaluated histologically [1].
The authors also reported long-term follow-up of approximately 12 years without documented recurrence. Long follow-up is particularly important in low-grade prostate cancer because short periods of stability may reflect the naturally slower behaviour of the tumour rather than a treatment effect. Durable absence of clinically detectable disease carries greater evidentiary value than an isolated early response, although it still cannot establish general effectiveness from a single patient [1].
The reported outcome should be interpreted together with the limitations of case-report evidence. There was no comparison group, randomisation or independent replication, and the patient had a small, low-grade, clinically localised tumour. The outcome therefore cannot be extrapolated to men with extensive Grade Group 2 disease, Grade Group 3–5 cancer, extracapsular extension, seminal-vesicle invasion, lymph-node involvement or metastatic spread.
Relevance to Patient Selection
The case supports further evaluation of individualised Ayurvedic treatment in patients whose disease characteristics allow close monitoring without an unacceptable delay in standard definitive care. The most clinically relevant candidates for consideration are men with confirmed localised disease, limited tumour burden, complete pathology and imaging records, reliable access to PSA testing and specialist follow-up, and a clear willingness to change treatment if objective progression occurs.
Eligibility should not be based on a patient’s desire to avoid surgery alone. Before treatment begins, the biopsy should be reviewed for Grade Group, tumour volume, percentage of pattern 4, cribriform architecture, intraductal carcinoma and perineural invasion where reported. Multiparametric magnetic resonance imaging should be assessed for lesion size, multifocality, extracapsular extension and seminal-vesicle involvement. Appropriate staging investigations should exclude regional or distant spread when the clinical risk warrants them [4,10].
During treatment, urinary improvement should be documented separately from cancer response. Reduced nocturia, improved urinary flow, better appetite, weight stability, sleep and energy may indicate functional benefit, but they do not prove tumour regression. Cancer control should be evaluated through dated PSA results, PSA density where appropriate, testosterone in men receiving hormone treatment, repeat imaging and biopsy when clinically indicated.
A rising PSA does not always represent treatment failure because infection, inflammation, urinary retention, instrumentation and changes in testosterone can alter the result. Persistent PSA elevation, pathological upgrading, enlargement of an MRI-visible lesion, new extracapsular disease or development of lymph-node or bone metastases requires prompt reassessment rather than continuation of an unchanged treatment plan.
The complete clinical chronology, formulation rationale, objective response assessment and long-term monitoring framework are examined in Ayurvedic Treatment for Prostate Cancer. The case is most valuable as evidence that carefully documented Ayurvedic treatment can be assessed through modern oncological endpoints, while recognising that treatment suitability and expected outcomes must be determined individually [1].
Varuna–Kanchanara Avaleha for Nonsurgical Prostate Cancer Treatment

Varuna–Kanchanara Rasayana Avaleha is a physician-designed medicine used within an individualised nonsurgical treatment for prostate cancer after the biopsy, Grade Group, PSA pattern, imaging, urinary function, current oncology treatment and organ function have been reviewed. It is not a classical fixed formula, a commercial one-size-fits-all product or a medicine that should be selected from the diagnosis alone.
Classical Basis and Clinical Purpose
The formulation draws on Rasayana principles described in Charaka Samhita, Chikitsa Sthana, Chapter 1 and the pharmaceutical principles of Avaleha preparation described in Sharangadhara Samhita, Madhyama Khanda, Chapter 8 [11,12]. Its semisolid form allows multiple decoctions, fine powders, lipid components and selected adjuvants to be combined in a measured oral dose.
Sushruta Samhita, Nidana Sthana, Chapter 11 describes Granthi and Arbuda as distinct classical categories of abnormal swellings and masses [13]. These descriptions can inform Ayurvedic assessment of tissue proliferation, firmness, fixation and local obstruction, but Granthi or Arbuda should not be treated as direct synonyms for biopsy-confirmed prostate adenocarcinoma. Modern diagnosis, grading and staging remain necessary for determining the biological risk of the cancer.
The therapeutic objective extends beyond temporary relief of urinary symptoms. In an appropriately selected patient, the plan is directed towards measurable disease control while preserving urinary function, digestion, strength, body weight, sleep and treatment tolerance. PSA stabilisation or reduction may be clinically encouraging, but imaging, repeat biopsy when indicated and the duration of response are needed to determine whether the cancer itself has remained stable or regressed.
Varuna and Kanchanara
Varuna, botanically identified as Crataeva nurvala, is selected when the clinical picture includes poor urinary flow, incomplete emptying, frequency, discomfort or a tendency towards urinary obstruction. Its inclusion does not mean that an obstructed patient can safely avoid urological assessment. Acute retention, hydronephrosis, recurrent urinary infection or deteriorating kidney function requires prompt investigation and may require catheterisation, endoscopic treatment or another procedure.
Kanchanara, Bauhinia variegata, is used within the Ayurvedic reasoning applied to firm glandular enlargement and Granthi-type tissue changes. Its role is considered in relation to the location, extent and behaviour of the disease rather than on prostate size alone. Benign enlargement, inflammation and prostate cancer can coexist, and a reduction in urinary symptoms or gland volume does not independently establish regression of malignant tissue.
The proportion of Varuna and Kanchanara is adjusted according to the dominant clinical problem. A patient with a small localised tumour and minimal urinary symptoms may require a different balance from a patient with marked benign enlargement, residual urine or treatment-related urinary irritation. The formulation is also modified when the patient has undergone prostate surgery, radiotherapy, catheterisation or previous treatment for urethral obstruction.
Urinary and Supportive Ingredients
Punarnava, Boerhavia diffusa, may be selected when urinary difficulty is accompanied by fluid retention, heaviness or swelling. Kidney function, blood pressure, hydration, sodium and potassium balance must be considered when it is used in a patient taking prescribed diuretics, antihypertensive medicines or treatment for heart or kidney disease.
Gokshura, Tribulus terrestris, may be included when urinary frequency, discomfort, weak stream or incomplete emptying is prominent. It should not be prescribed merely because it is widely marketed for male health. Products promoted for increasing testosterone or sexual performance may be inappropriate in hormone-sensitive prostate cancer, particularly when androgen-deprivation therapy has been prescribed.
Pashanabheda, Bergenia ligulata, is considered when urinary sediment, stone history or painful urinary symptoms coexist with the prostate disorder. Its inclusion is based on the complete urinary assessment and does not replace urine culture, renal imaging or evaluation for obstruction when infection, haematuria, flank pain or recurrent stone formation is present.
Amalaki, Phyllanthus emblica, Haritaki, Terminalia chebula, and Bibhitaki, Terminalia bellirica, may be used together as Triphala when bowel regularity, appetite and digestive tolerance require support. This can be clinically important during hormone treatment, radiotherapy or reduced physical activity, but excessive dosing may cause diarrhoea, dehydration or altered absorption of other medicines.
Guggulu, derived from Commiphora wightii, may be combined with Kanchanara in selected patients when firm tissue enlargement and Kapha-dominant features are present. It is not compulsory and may be omitted when the patient has gastrointestinal intolerance, a complex medicine schedule, thyroid disease, bleeding risk or a potential interaction with prescribed treatment.
Haridra, Curcuma longa, and Shallaki, Boswellia serrata, may be selected when inflammatory symptoms, pelvic discomfort or treatment-related tissue irritation contribute to the presentation. Their inclusion should be based on the standardised extract, total daily exposure, anticoagulant use, liver function and timing relative to radiotherapy or systemic cancer treatment.
A randomised study of curcumin in men receiving intermittent androgen-deprivation therapy found suppression of PSA elevation during the administration period but no significant extension of the overall period without hormone treatment [14]. The result supports further investigation but does not establish curcumin as a substitute for surveillance, radiotherapy, hormone treatment or another oncological intervention.
Boswellic-acid studies have demonstrated apoptosis, inhibition of angiogenesis and reduced growth in prostate-cancer laboratory models [15,16]. These findings remain preclinical and cannot be used to predict the effect of Shallaki in an individual patient. The botanical extract, boswellic-acid concentration and dose used in a laboratory study may differ substantially from those present in a personalised Avaleha.
Guduchi Requires Hormonal Caution
Guduchi, Tinospora cordifolia, is not included automatically in prostate cancer formulations. Although it is traditionally used in Rasayana practice, an in-vitro study using androgen-sensitive LNCaP prostate-cancer cells reported androgenic activity and increased PSA secretion following exposure to an ethanolic Guduchi extract [17].
A cell study cannot determine the clinical effect of every Guduchi preparation, and aqueous, ethanolic and compound formulations may behave differently. Nevertheless, the finding is relevant when treating hormone-sensitive prostate cancer or a patient receiving androgen-deprivation therapy. Guduchi may therefore be omitted, restricted or replaced when the therapeutic aim depends on suppressing androgen-receptor signalling.
The same principle applies to herbs or supplements marketed for improving testosterone, male vitality or sexual performance. A product that raises testosterone or stimulates androgen signalling could conflict with abiraterone, enzalutamide, apalutamide, darolutamide, medical castration or other hormone-directed treatment. Every such product should be reviewed before it is combined with the Avaleha.
Shilajit and Herbo-Mineral Medicines
Shuddha Shilajit refers to purified and processed Shilajit. It may be considered when weakness, poor recovery or reduced treatment tolerance is clinically prominent, but it is not an essential ingredient for every patient. Its use requires verified identity, contaminant testing and review of kidney function, liver function and the patient’s complete supplement exposure.
Swarna Bhasma, Heeraka Bhasma, Abhraka Bhasma, Yashada Bhasma, Vanga Bhasma or Swarna Makshika Bhasma are not routine components of every Varuna–Kanchanara Avaleha. Bhasma denotes a specially processed calcined mineral or metal preparation. Any such medicine must be selected separately according to the patient’s disease stage, constitution, blood counts, organ function, concurrent treatment and capacity for close monitoring.
No universal bhasma combination or dose is appropriate for prostate cancer. A patient with localised Grade Group 1 disease, normal organ function and no systemic treatment has a different risk profile from a patient receiving chemotherapy, radioligand treatment, long-term hormone therapy or medicines that affect the kidneys, liver or bone marrow.
Batch-specific testing is essential for botanical identity, microbial contamination, pesticides and concentrations of lead, mercury, arsenic and cadmium. A study of Ayurvedic products purchased online detected lead, mercury or arsenic in approximately one-fifth of the sampled products, demonstrating why an unverified internet preparation should not be treated as equivalent to a physician-dispensed, analytically tested medicine [18].
Mineral-containing preparations require additional review of the chemical form, intended daily exposure, duration of use and laboratory findings. The terms purified, traditional or natural do not by themselves establish safety. Unexpected abdominal pain, persistent vomiting, jaundice, dark urine, altered sensation, unusual weakness, confusion, anaemia or declining kidney function requires immediate discontinuation and medical assessment.
Avaleha Base and Dose Selection
The Avaleha base is selected according to digestive tolerance, body weight, bowel function, metabolic health and the stability of the incorporated ingredients. Classical preparation requires controlled heating and assessment of the final consistency according to the Avaleha Paka principles described in Sharangadhara Samhita, Madhyama Khanda, Chapter 8 [12].
Traditional Avaleha preparations may contain sugar, jaggery, honey or Ghrita. A standard sweetened base may be unsuitable for a patient with uncontrolled diabetes, obesity, fatty liver disease, steroid-related hyperglycaemia or metabolic effects from androgen-deprivation therapy. In such cases, the quantity must be restricted or another pharmaceutical form should be selected rather than ignoring the carbohydrate exposure.
Honey should not be exposed to inappropriate high-temperature processing, and it should be added only at a suitable stage when included. Ghrita may improve palatability and delivery of lipid-soluble constituents, but the amount requires modification in patients with nausea, poor fat tolerance, pancreatic disease or substantial metabolic risk.
The dose is determined from the concentration of the finished preparation rather than from the volume of Avaleha alone. Two preparations with the same medicine name may contain very different amounts of decoction solids, powders, extracts and adjuvants. A spoon-based dose without documented concentration and batch composition is therefore insufficient for reliable prescribing.
Modification During Active Cancer Treatment
During active surveillance, the formulation is designed so that changes in PSA, urinary symptoms and imaging remain interpretable. New ingredients should not be added repeatedly in response to every small PSA fluctuation because frequent changes make it difficult to identify benefit, adverse effects or natural biological variation.
During radiotherapy, the prescription may require reduction or temporary withdrawal of ingredients that aggravate bowel frequency, urinary burning, dehydration or mucosal irritation. New concentrated extracts should not be introduced during acute radiation toxicity without coordination with the treating team.
During androgen-deprivation therapy, ingredients with possible androgenic or testosterone-enhancing effects are avoided. Monitoring should also address glucose, lipids, blood pressure, muscle loss, fatigue and bone health because improvement in urinary symptoms alone does not address the systemic effects of prolonged hormone suppression [4,10].
During chemotherapy, targeted therapy or radioligand treatment, the Avaleha must be reviewed against the oncology schedule, blood counts, liver enzymes, kidney function, nausea, diarrhoea and infection risk. Treatment should be withheld or modified when neutropenia, thrombocytopenia, significant vomiting, acute liver injury or renal deterioration develops.
Response and Safety Monitoring
Before treatment, the patient should have recent PSA results, complete blood count, liver and kidney function, glucose assessment and a documented list of medicines and supplements. Testosterone is required when the patient is receiving, has recently stopped or may not be responding adequately to androgen-deprivation therapy.
Laboratory safety testing should be repeated after initiation and after clinically significant dose changes, with the interval determined by the formulation, disease stage, comorbidities and concurrent cancer treatment. Patients receiving a purely herbal preparation generally require a different monitoring intensity from those receiving selected herbo-mineral medicines or systemic oncology treatment.
The Avaleha should be continued, modified or stopped according to objective findings. A sustained PSA rise, pathological upgrading, enlargement of an MRI-visible lesion, new extracapsular extension, lymph-node involvement, bone disease, urinary retention or unexplained weight loss requires reassessment of the entire treatment strategy rather than simply increasing the Ayurvedic dose.
Measuring Nonsurgical Treatment for Prostate Cancer
Success with nonsurgical treatment for prostate cancer must be measured through objective cancer-control findings, functional recovery and treatment safety. A lower PSA or improved urination may be encouraging, but neither result alone proves that malignant tissue has regressed. The monitoring plan must reflect whether the patient is receiving active surveillance, radiotherapy, focal treatment, hormone therapy, systemic treatment or an individualised Ayurvedic protocol [4,5,10].
Cancer Control Must Be Separated From Symptom Relief
Cancer control refers to stability, regression or disappearance of objectively documented disease. Depending on the clinical setting, this may be assessed through serial PSA results, PSA density, testosterone, multiparametric magnetic resonance imaging, PSMA PET/CT, conventional imaging, repeat biopsy and the absence of new lymph-node, bone or organ involvement [4,10].
Functional recovery includes improved urinary flow, reduced nocturia, less urgency, better bladder emptying, improved bowel comfort, preservation of sexual function, stable weight, greater strength and better quality of life. These outcomes matter to patients, but they must be recorded separately from oncological response because urinary symptoms can improve even when prostate cancer remains present.
A man may experience better urination because inflammation, benign prostate enlargement or pelvic irritation has improved without any change in the malignant tissue. Conversely, a patient may have stable cancer while urinary symptoms worsen because of benign enlargement, infection, bladder dysfunction, urethral narrowing or treatment-related irritation. Symptoms and cancer behaviour must therefore be investigated as related but distinct clinical outcomes.
Interpreting PSA Correctly
PSA is central to follow-up, but its meaning differs according to the treatment received. One unexpected result should usually be confirmed and interpreted with the preceding trend, clinical findings and possible temporary influences rather than being labelled immediately as progression or treatment failure [4,5,10].
During active surveillance, PSA is generally measured at regular intervals, often at least every six months, although the exact schedule varies according to national guidance, disease risk and previous results. PSA density and the pattern of change over time can help identify patients who need further investigation. A rising PSA should normally prompt clinical review, repeat magnetic resonance imaging or biopsy rather than an automatic change to definitive treatment based on PSA alone [5,10].
PSA doubling time can help identify a concerning pattern, but it does not independently prove pathological progression. A rapid rise is more clinically significant when it is accompanied by increasing PSA density, an enlarging MRI-visible lesion, a higher Grade Group on biopsy or new evidence of disease outside the prostate. Stable imaging and pathology may support continued surveillance despite modest PSA variation, while pathological upgrading can require treatment even when the PSA change is small [10].
After radiotherapy, the prostate remains in the body and continues to produce some PSA. The level commonly falls gradually and may take three years or longer to reach its lowest point, known as the PSA nadir. Patients should therefore not expect the PSA to become undetectable as quickly as it would after complete surgical removal of the prostate [10].
A temporary PSA bounce can occur after external-beam radiotherapy or brachytherapy. This short-lived increase may subsequently fall without additional cancer treatment and should be distinguished from a sustained biochemical recurrence. The timing, magnitude and subsequent pattern of the rise must be reviewed before conclusions are drawn.
Biochemical recurrence after radiotherapy is commonly defined as a confirmed PSA increase of 2 ng/mL or more above the post-treatment nadir. This definition can also be applied when radiotherapy was combined with androgen-deprivation therapy. A smaller PSA rise may still require follow-up, particularly when it is persistent or accompanied by symptoms, but it does not automatically establish radiotherapy failure [10].
Hormone treatment can suppress PSA by reducing androgen stimulation of prostate-cancer cells. A falling PSA during androgen-deprivation therapy may indicate treatment response, but it must be interpreted with serum testosterone. A low PSA achieved while testosterone is suppressed is not equivalent to an untreated remission, and PSA may rise as testosterone recovers after temporary hormone therapy.
When PSA increases during ongoing androgen-deprivation therapy, testosterone should be measured to confirm whether castrate suppression has been achieved and maintained. Progression despite a testosterone level below the accepted castrate threshold raises concern for castration-resistant disease and requires specialist reassessment. Failure to measure testosterone can lead to incorrect classification of treatment resistance [4,10].
After focal treatment, including high-intensity focused ultrasound or cryotherapy, untreated prostate tissue may continue producing PSA. No single PSA threshold can reliably confirm eradication of all clinically significant disease after every focal procedure. PSA trend, magnetic resonance imaging, targeted biopsy and systematic assessment of untreated regions may therefore be needed to determine whether the treated lesion has resolved and whether cancer remains elsewhere in the gland [4,10].
During an individualised Ayurvedic protocol, PSA should be interpreted using the same oncological principles. A temporary fall is insufficient to establish regression, particularly when the patient is also taking finasteride, dutasteride, hormone therapy or another medicine that can lower PSA. A sustained response becomes more meaningful when it is supported by stable or improving imaging, favourable pathology and an absence of clinical progression.
MRI and Repeat Biopsy
Multiparametric magnetic resonance imaging can evaluate changes in lesion size, appearance, extracapsular extension, seminal-vesicle involvement and the development of additional suspicious areas. Comparison should ideally be made with the baseline images rather than relying only on separate written reports, because small changes may be difficult to interpret without direct radiological comparison [5,10].
Stable magnetic resonance imaging reduces concern for progression but does not eliminate the possibility of pathological upgrading. Some clinically significant changes can be missed if follow-up depends on imaging alone. Repeat biopsy therefore remains part of many active-surveillance protocols, particularly when PSA density increases, PSA doubling time shortens, the initial biopsy was limited or the patient has favourable intermediate-risk disease [10].
MRI progression should generally lead to histological reassessment before a patient is moved from surveillance to definitive treatment. An enlarging lesion may reflect increasing cancer volume, but inflammation, technical variation and differences in radiological interpretation can also affect serial imaging. Targeted biopsy of the suspicious area, often combined with systematic sampling, provides stronger evidence of a true Grade Group change [10].
Repeat biopsy evaluates whether the Grade Group has increased, the amount of cancer has expanded or adverse features such as cribriform architecture or intraductal carcinoma have appeared. Reclassification to Grade Group 3 or higher, increasing systematic-core involvement or detection of an adverse growth pattern can materially change eligibility for continued surveillance [10].
A negative repeat biopsy is reassuring but does not prove that every malignant cell has disappeared. Prostate biopsy samples only selected areas of the gland, and a small lesion may be missed. A negative result is most persuasive when it is consistent with a sustained favourable PSA pattern, stable or improved magnetic resonance imaging and subsequent long-term follow-up.
In the published Ayurvedic prostate-cancer case, the reported post-treatment biopsy did not identify the previously documented malignant focus, and the authors reported long-term follow-up without documented recurrence. The repeat pathology and extended observation provide greater evidentiary value than symptom improvement alone, while the single-patient design and possibility of sampling limitations prevent the result from establishing a general treatment response rate [1].
PSMA PET/CT is not routinely required for every patient with stable low-risk localised disease. It is more useful when biochemical recurrence, higher-risk disease or metastatic spread is suspected and when the result is likely to alter treatment. Very small-volume disease can remain below the detection threshold, particularly at low PSA levels, so a negative scan does not always exclude microscopic cancer [4,10].
Monitoring Hormone and Systemic Treatment
Patients receiving androgen-deprivation therapy require assessment of both disease response and treatment toxicity. PSA, testosterone, symptoms and imaging must be interpreted together. A PSA response without adequate testosterone suppression may not represent the intended biological effect, while radiographic or symptomatic progression can occur even when PSA changes are modest [4,10].
Clinical review is commonly performed every three to six months during established hormone treatment, with more frequent assessment when a new androgen-receptor pathway inhibitor or another potent systemic medicine is initiated. Monitoring may include blood counts, kidney function, liver function, glucose, glycated haemoglobin, lipids, blood pressure, body weight and cardiovascular symptoms according to the medicines used [10].
Bone health requires specific attention because prolonged androgen suppression accelerates bone loss and increases fracture risk. Baseline fracture assessment, vitamin D status and bone-density testing may be required, followed by repeat evaluation according to treatment duration and individual risk. New focal bone pain should not be assumed to represent treatment-related weakness; it may require imaging to exclude metastasis or fracture [10].
In metastatic disease, response cannot be judged from PSA alone. Imaging findings, pain, mobility, analgesic requirements, urinary obstruction, weight, performance status, blood counts, alkaline phosphatase where relevant and evidence of new skeletal or organ disease provide additional information. A treatment change should be based on the complete pattern of biochemical, radiological and clinical progression rather than one laboratory result [4,10].
Patients receiving chemotherapy, targeted therapy or radioligand treatment also require medicine-specific safety monitoring. A favourable PSA response does not justify continuing an otherwise effective treatment without modification when severe marrow suppression, liver injury, kidney impairment, infection, neuropathy or another clinically significant toxicity develops.
Urinary, Bowel and Sexual Outcomes
Urinary function should be documented before treatment and followed with the same questions or validated scoring system. Frequency, urgency, nocturia, weak stream, straining, incomplete emptying, leakage, painful urination, haematuria and episodes of retention provide a clearer picture than a general statement that urination is better or worse.
A reduced symptom score can demonstrate meaningful functional improvement, but bladder emptying may still be inadequate. Post-void residual urine, urinary-flow measurement, kidney function and imaging may be required when weak stream, recurrent infection, retention or hydronephrosis is suspected. Persistent obstruction can damage the urinary tract even when pain is minimal.
Bowel monitoring is particularly important during and after pelvic radiotherapy. Increased frequency, urgency, diarrhoea, rectal discomfort, mucus, bleeding and loss of bowel control should be recorded and treated. Rectal bleeding should not automatically be attributed to radiation because haemorrhoids, inflammatory disease, polyps and colorectal cancer may produce similar symptoms.
Sexual outcomes include erectile function, libido, ejaculation, orgasm, penile changes and the effect of treatment on intimacy. Radiotherapy, hormone treatment, focal therapy, age, cardiovascular disease, diabetes and psychological distress may all contribute. Recording the baseline condition prevents pre-existing dysfunction from being attributed entirely to the cancer treatment.
General recovery should include body weight, appetite, muscle strength, fatigue, sleep, activity level, mood and ability to perform normal work and household responsibilities. These measures are particularly important during prolonged hormone treatment because metabolic change, sarcopenia, depression and reduced physical capacity can develop gradually despite stable cancer markers [10].
Defining Response, Remission and Cure
Stable disease means that available measurements show no clinically meaningful progression during the defined observation period. In active surveillance, this generally requires no concerning pathological upgrading, no significant increase in tumour extent and no evidence that the cancer has spread beyond its previously documented boundaries.
A partial response indicates measurable improvement without complete disappearance of all detectable disease. Depending on the treatment setting, this may include reduction in lesion size, reduced metastatic burden, substantial PSA decline or improvement in cancer-related symptoms. A PSA reduction alone should not be described as a complete response when residual disease has not been reassessed.
Complete response or no evidence of disease requires the absence of detectable cancer on the investigations appropriate to that clinical situation. For localised prostate cancer, this may involve a sustained favourable PSA pattern, imaging without a suspicious residual lesion and negative pathology when repeat biopsy is clinically indicated. The required evidence differs after radiotherapy, focal treatment, hormone treatment and an exclusively medical or Ayurvedic approach.
Remission describes a period during which the cancer is no longer detectable or remains under effective control. The term should include the duration of follow-up because a finding obtained several months after treatment carries less certainty than a response maintained over many years. Continued monitoring remains necessary even after a favourable early result.
Cure should be reserved for durable freedom from clinically significant disease supported by appropriate pathology, imaging, PSA behaviour and long-term follow-up. After radiotherapy, cure does not require an undetectable PSA because functioning prostate tissue remains. During continuing hormone treatment, a low PSA cannot independently establish cure because the marker is being pharmacologically suppressed.
The ProtecT trial demonstrated that prostate-cancer-specific mortality remained low at 15 years among men assigned to monitoring, prostatectomy or radiotherapy, but progression and metastasis were more frequent with monitoring. Long-term survival data therefore support careful treatment selection while also showing why early stability should not be mistaken for permanent cure [2].
When the Treatment Plan Must Change
Continued nonsurgical management should be reconsidered when repeat biopsy shows clinically important Grade Group progression, adverse cribriform or intraductal features, increasing cancer volume or another pathological change that alters the risk category. The availability of radiotherapy, surgery or systemic treatment should be reviewed before the disease advances beyond a potentially curable stage [5,10].
Radiological progression includes a clearly enlarging prostate lesion, extracapsular extension, seminal-vesicle invasion, new lymph-node disease, bone metastasis or spread to another organ. The significance of any imaging change depends on the modality, comparison quality and whether confirmation would alter treatment, but a suspected new metastatic site should not be managed solely by increasing the dose of the existing therapy.
Persistent PSA progression requires reassessment even when the patient feels well. The evaluation may include repeat PSA, testosterone, urine testing, magnetic resonance imaging, PSMA PET/CT, repeat biopsy or other staging investigations according to the previous treatment and disease risk. The objective is to distinguish laboratory variation or a benign cause from local recurrence, pathological progression or systemic spread.
New urinary retention, visible haematuria, progressive pelvic pain, unexplained weight loss, increasing fatigue, new bone pain, leg weakness, numbness, difficulty walking or loss of bladder or bowel control requires prompt medical evaluation. These findings may indicate obstruction, bleeding, fracture, spinal cord compression or advancing disease and should not wait for the next routine follow-up appointment [4,10].
Evidence for Nonsurgical Treatment for Prostate Cancer

Evidence for nonsurgical treatment for prostate cancer differs according to the patient’s risk group, treatment objective and selected therapy. Active surveillance has long-term evidence for carefully selected localised disease, radiotherapy has curative evidence across several risk groups, hormone and systemic treatments are central to advanced disease, and focal or Ayurvedic approaches require more selective interpretation because their evidence bases are less mature or more limited [1–5,10].
Active Surveillance Versus Immediate Treatment
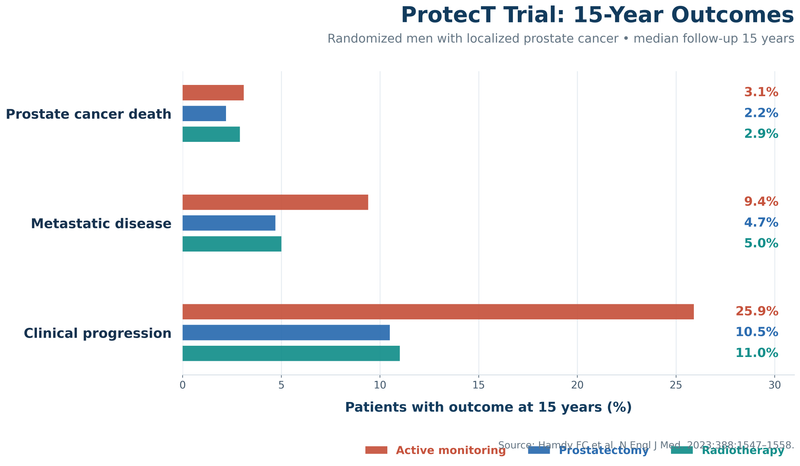
The ProtecT randomised trial provides important long-term evidence for men considering monitoring instead of immediate surgery or radiotherapy. After a median follow-up of 15 years, prostate-cancer-specific mortality was low in all three groups. Death from prostate cancer occurred in 3.1% of men assigned to active monitoring, 2.2% assigned to prostatectomy and 2.9% assigned to radiotherapy, with no statistically significant difference in prostate-cancer mortality among the groups [2].
The same trial showed that low mortality does not mean that every outcome was equivalent. Metastatic disease developed in 9.4% of men assigned to active monitoring, compared with 4.7% after prostatectomy and 5.0% after radiotherapy. Clinical progression occurred in 25.9%, 10.5% and 11.0%, respectively. Long-term androgen-deprivation therapy was also used more often after active monitoring [2].
These results help patients understand the central trade-off. Monitoring may allow some men to avoid or postpone urinary, sexual and bowel effects associated with radical treatment, but it carries a greater probability of later progression or treatment. At 15 years, approximately one-quarter of the men initially assigned to active monitoring were alive without having received prostate-cancer treatment [2].
The monitoring protocol used in ProtecT relied more heavily on serial PSA testing than contemporary active-surveillance programmes. Modern pathways commonly incorporate multiparametric magnetic resonance imaging, targeted biopsy, PSA density and structured pathological reassessment. The trial therefore supports informed treatment deferral in selected patients but should not be interpreted as proving that monitoring is equally suitable for every localised cancer [2,10].
Men with Grade Group 1 disease, reassuring imaging and limited tumour volume are the clearest candidates for surveillance. Selected men with favourable Grade Group 2 cancer may also be considered when pattern 4 is minimal, disease extent is low and cribriform or intraductal carcinoma is absent. The evidence becomes less reassuring as Grade Group, tumour volume, PSA density or evidence of local extension increases [5,10].
The decision is not simply between immediate treatment and doing nothing. A well-run surveillance programme creates scheduled opportunities to detect pathological upgrading or radiological progression while curative treatment remains feasible. The benefit depends on adherence to PSA testing, imaging, repeat biopsy and timely treatment when objective progression is confirmed [5,10].
Curative Radiotherapy Without Prostate Removal
Radiotherapy is an established curative nonsurgical treatment for many men with cancer confined to the prostate or immediately surrounding tissues. External-beam radiotherapy can be used for low-, intermediate- and high-risk localised disease, while brachytherapy may be used alone or combined with external-beam treatment in selected patients [4,5,10].
For a man choosing between surgery and radiotherapy, the evidence does not support assuming that prostate removal is always required for cure. The ProtecT trial found similarly low prostate-cancer mortality after prostatectomy and radiotherapy at 15 years, with closely comparable rates of metastatic disease and clinical progression between those two treatment groups [2].
The expected adverse-effect profiles differ. Surgery carries greater immediate risks related to anaesthesia, bleeding, urinary continence and erectile function. Radiotherapy avoids an operation but can produce urinary irritation, bowel symptoms, erectile dysfunction and delayed tissue effects. The most suitable option depends on baseline urinary, bowel and sexual function, prostate size, previous pelvic procedures, other illnesses and the patient’s priorities [4,5,10].
Radiotherapy does not prevent later treatment if cancer recurs, but salvage options after radiation can be more technically complex than treatment of an untreated prostate. Before choosing radiotherapy, patients should understand how recurrence would be detected and which salvage procedures are available at the treating centre.
Evidence for Five-Fraction SBRT
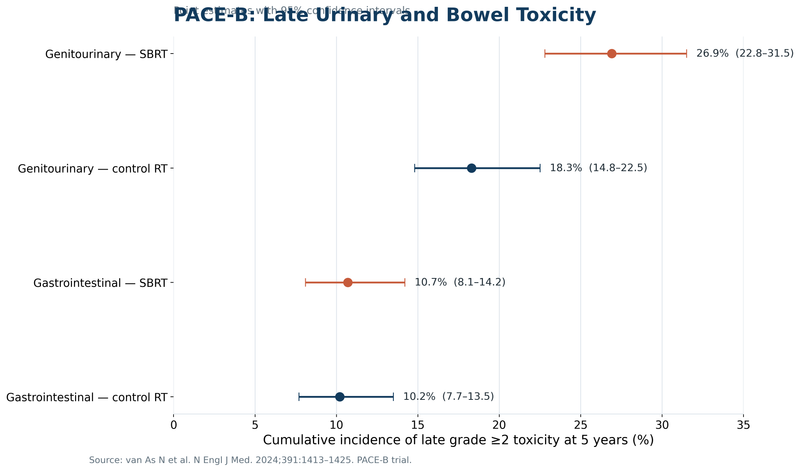
Stereotactic body radiotherapy can deliver definitive prostate treatment in five high-dose sessions. In the PACE-B phase 3 trial, five-fraction stereotactic radiotherapy was noninferior to conventional or moderately hypofractionated radiotherapy for biochemical or clinical failure in selected men with localised low- or intermediate-risk prostate cancer [3].
The trial supports SBRT as a shorter curative option for appropriately selected patients. It does not establish five-fraction treatment as suitable for every prostate cancer. The participants predominantly had low-risk or intermediate-risk disease, and the findings should not be automatically extended to men with extensive high-risk cancer, pelvic lymph-node involvement or metastatic disease [3].
Convenience should not be the only reason to select SBRT. Baseline urinary obstruction, prostate anatomy, previous transurethral surgery, inflammatory bowel disease, hip mobility and the centre’s experience with image guidance and treatment planning can affect safety. A five-session schedule still requires careful simulation, organ-motion management and long-term follow-up.
Patients should also consider that treatment schedules differ among the USA, UK, Canada, Singapore and Australia according to local protocols, equipment and reimbursement. A longer radiotherapy schedule is not necessarily inferior, and a shorter schedule is not automatically safer. Both must deliver an adequate cancer dose while protecting the bladder, rectum, urethra and surrounding tissues [3–8,10].
Radiotherapy With Hormone Treatment
For unfavourable intermediate-risk, high-risk or locally advanced prostate cancer, radiotherapy is often combined with androgen-deprivation therapy because treating the prostate alone may be insufficient. The duration and intensity of hormone treatment depend on Grade Group, PSA, tumour stage, lymph-node risk, comorbidities and the estimated benefit of combined treatment [4,5,10].
Hormone treatment can improve cancer control in appropriately selected higher-risk disease, but it introduces systemic effects that do not occur with prostate-directed radiotherapy alone. These may include hot flushes, reduced libido, erectile dysfunction, fatigue, loss of muscle, increased body fat, insulin resistance, altered lipids, reduced bone density and cardiovascular concerns [4,10].
A patient who wishes to avoid surgery must therefore compare the complete treatment burden rather than only the absence of an operation. Several months or years of hormone treatment may have greater day-to-day consequences than the radiotherapy sessions themselves. Baseline cardiovascular, metabolic and bone-health assessment is particularly important before prolonged androgen suppression [4,10].
Hormone treatment alone is generally not equivalent to curative local treatment for a fit man with localised disease. It may control PSA and reduce tumour activity while treatment continues, but it usually does not eradicate all localised cancer when used as the sole treatment. Patients should ask whether hormone therapy is being used temporarily with radiotherapy, continuously for metastatic disease or primarily for symptom control [4,10].
Evidence for Focal Treatment
Focal treatment aims to destroy a selected cancer focus while preserving more untreated prostate tissue than whole-gland surgery or radiotherapy. High-intensity focused ultrasound and cryotherapy are the most established focal techniques, while irreversible electroporation and other forms of ablation are available in selected centres.
The potential advantage is reduced urinary and sexual morbidity in carefully selected patients. The principal limitation is that prostate cancer is often multifocal, and clinically significant disease may remain outside the treated area. A technically successful ablation of one MRI-visible lesion does not guarantee that the remainder of the prostate is cancer-free [10].
Current evidence includes prospective registries and nonrandomised comparisons, but long-term standardised data remain less mature than for prostatectomy or radiotherapy. Retreatment is not uncommon, and different studies use different definitions of treatment failure. Some allow repeat focal treatment without classifying it as failure, making direct comparison with surgery or radiotherapy difficult [10].
Appropriate selection requires high-quality multiparametric magnetic resonance imaging, targeted biopsy and systematic or template-based sampling to assess both the visible lesion and the rest of the gland. Follow-up commonly requires continued PSA testing, repeat imaging and further biopsy because PSA alone cannot confirm that all clinically significant cancer has been eliminated [10].
Focal therapy should therefore be considered only after a patient understands the possibility of untreated disease, repeat ablation and later salvage surgery or radiotherapy. International guidance remains cautious, with focal HIFU or cryotherapy generally recommended within experienced programmes that collect prospective outcome data [10].
Evidence for Systemic Nonsurgical Treatment
For metastatic prostate cancer, the strongest evidence supports systemic treatment rather than prostate removal as the principal method of disease control. Androgen-deprivation therapy is commonly combined with an androgen-receptor pathway inhibitor, chemotherapy or another treatment according to disease volume, symptoms, previous therapy, fitness and molecular findings [4,10].
The purpose of systemic treatment is to control cancer throughout the body rather than only within the prostate. PSA reduction can be substantial, but response must also be assessed through symptoms, imaging, testosterone, blood counts, organ function and the development of new metastatic sites.
Selected men with newly diagnosed low-volume metastatic disease may also benefit from radiotherapy to the prostate. This does not convert metastatic cancer into localised disease, but treating the primary tumour may improve outcomes in a defined subgroup when combined with systemic therapy [4,10].
Molecular testing may identify patients with inherited or tumour-acquired DNA-repair alterations who could benefit from targeted medicines. PSMA-targeted radioligand treatment may be considered in selected advanced cases after appropriate imaging and previous therapies. Eligibility varies with disease state and regulatory approval in each country, so treatment sequencing requires specialist review [4,10].
Evidence for Individualised Ayurvedic Treatment
The published Ayurvedic evidence relevant to prostate cancer includes a detailed case report of a 45-year-old man with biopsy-confirmed Gleason 3+3, Grade Group 1, clinical T1 adenocarcinoma and a small right mid-prostate lesion. He received an individualised Ayurvedic protocol without surgery, radiotherapy or conventional systemic cancer treatment [1].
The report described absence of the previously identified malignant focus on repeat biopsy after approximately nine months of treatment. The authors also reported long-term follow-up of approximately 12 years without documented recurrence. The combination of baseline pathology, repeat biopsy and extended follow-up gives the case greater clinical value than a report based only on PSA or symptom improvement [1].
The evidence remains limited to one patient. A case report cannot establish a response rate, determine which ingredient produced the outcome or predict results in men with Grade Group 2–5 disease, extracapsular extension, lymph-node involvement or metastases. The favourable natural history of some low-volume Grade Group 1 cancers and the possibility of biopsy sampling variation must also be considered [1].
The case is most relevant as proof that an Ayurvedic treatment pathway can be documented through modern oncological endpoints. It supports further investigation of individualised treatment in carefully selected and closely monitored patients, but it does not justify delaying necessary radiotherapy, surgery or systemic treatment when the clinical risk indicates that immediate intervention is required.
For patients receiving Varuna–Kanchanara Rasayana Avaleha or another physician-designed Ayurvedic formulation, treatment response must be evaluated using the same diagnostic standards applied to other nonsurgical pathways. Serial PSA, prostate volume, PSA density, magnetic resonance imaging, repeat biopsy when indicated and staging investigations should guide continuation or modification [1,4,10].
Ayurvedic treatment may also be used alongside surveillance, radiotherapy or hormone treatment when the formulation has been reviewed for clinical relevance, organ function and medicine interactions. Concurrent use requires particular caution with herbs marketed as testosterone-enhancing, concentrated extracts that may alter drug metabolism and mineral preparations lacking batch-specific safety testing.
Applying the Evidence to an Individual Patient
Evidence from a trial or guideline does not determine eligibility without reference to the individual patient. ProtecT is most informative for men with localised disease considering monitoring, surgery or radiotherapy. PACE-B applies to selected low- and intermediate-risk patients considering SBRT. Neither trial establishes that surveillance or five-fraction radiotherapy is appropriate for aggressive, node-positive or metastatic cancer [2,3].
The most important starting variables are Grade Group, proportion of Gleason pattern 4, cribriform or intraductal histology, tumour volume, PSA density, clinical stage and imaging. Life expectancy, cardiovascular health, urinary function, bowel disease, sexual priorities, previous treatment and willingness to undergo follow-up determine whether a clinically available option is also suitable for that patient [4,5,10].
Patients in the USA, UK, Canada, Singapore and Australia may receive different treatment recommendations because healthcare systems, access to brachytherapy, focal therapy, PSMA PET/CT and specialist centres vary. The underlying clinical principles remain consistent: low-risk disease may qualify for surveillance, localised cancer may be cured with radiotherapy without prostate removal, and advanced disease usually requires systemic treatment [4–10].
A second opinion is particularly valuable when recommendations differ, the biopsy contains favourable Grade Group 2 disease, focal treatment is proposed, substantial hormone therapy is planned or the patient has been told that surgery is the only curative option. The review should include the original pathology, magnetic resonance images and full PSA history rather than relying only on a brief report.
A treatment decision should specify the intended outcome, the evidence supporting that option, the expected adverse effects, the monitoring schedule and the findings that would trigger a change. This allows a patient to distinguish a structured nonsurgical cancer-control plan from treatment delay without adequate surveillance.
Questions Before Nonsurgical Treatment for Prostate Cancer

Before choosing nonsurgical treatment for prostate cancer, patients should understand the exact cancer risk, the purpose of the proposed treatment, the monitoring burden and the circumstances in which the plan would need to change. These questions are particularly important when considering active surveillance, radiotherapy, focal ablation, hormone treatment or an individualised Ayurvedic programme [4,5,10].
1. What Is My Exact Gleason Score and Grade Group?
The pathology report should state both the Gleason score and Grade Group. Gleason 3+3 corresponds to Grade Group 1, Gleason 3+4 to Grade Group 2, Gleason 4+3 to Grade Group 3, Gleason 8 to Grade Group 4 and Gleason 9–10 to Grade Group 5. The order of the Gleason patterns matters because Gleason 4+3 generally indicates a greater proportion of aggressive pattern 4 than Gleason 3+4 [4,5,10].
Patients should ask whether the biopsy was reviewed by a pathologist experienced in genitourinary cancer, particularly when active surveillance or focal treatment is being considered. A change from Grade Group 1 to Grade Group 2, or from limited to extensive pattern 4, can materially alter eligibility for continued surveillance.
The report should also identify whether cribriform architecture or intraductal carcinoma is present. These adverse features are associated with a less favourable prognosis and generally make conservative monitoring less appropriate, even when other findings initially appear favourable [10].
2. Is the Cancer Confined to the Prostate?
Clinical stage helps determine whether treatment can remain focused on the prostate or must also address surrounding tissues, lymph nodes or distant disease. Localised disease is confined to the gland, while locally advanced disease may extend through the prostate capsule or involve the seminal vesicles. Metastatic disease has spread to distant lymph nodes, bones or other organs [4,5,10].
Multiparametric magnetic resonance imaging can assess the relationship between the tumour, prostate capsule, seminal vesicles, urethra and neurovascular structures. Higher-risk patients may also require PSMA PET/CT, computed tomography or bone imaging according to the Grade Group, PSA, symptoms and proposed treatment [4,10].
A patient should ask whether the stage is based on examination alone or supported by imaging. A statement that the cancer is “early” should be clarified with the clinical TNM stage, Grade Group and imaging findings before treatment is deferred.
3. How Much Cancer Was Found in the Biopsy?
The number of positive biopsy cores, percentage or length of cancer within each core, laterality and location provide information beyond the Gleason score. A small focus of Grade Group 1 disease in one or two cores carries a different risk from Grade Group 1 cancer occupying numerous bilateral cores [5,10].
For Grade Group 2 disease, the proportion of Gleason pattern 4 should be documented. A patient with minimal pattern 4 and limited cancer volume may be considered for surveillance by some specialist teams, while extensive pattern 4, numerous positive cores or substantial core involvement usually favours active treatment [10].
Patients considering focal treatment should ask whether systematic samples outside the MRI-visible lesion were negative. Treating one dominant lesion without adequately assessing the remainder of the prostate can leave clinically significant cancer untreated.
4. Does the Pathology Show Cribriform or Intraductal Cancer?
Cribriform architecture describes a specific pattern of malignant gland formation, while intraductal carcinoma refers to malignant cells expanding pre-existing prostate ducts and glands. These findings are not interchangeable with ordinary low-volume Gleason pattern 4 and can indicate biologically less favourable disease [10].
Their presence may influence whether active surveillance, focal ablation or limited treatment remains appropriate. Patients whose reports do not mention these findings should ask whether they were assessed, especially when Grade Group 2 disease is being considered for surveillance.
The absence of cribriform or intraductal disease does not by itself establish low risk. It must be interpreted with Grade Group, cancer volume, PSA density, magnetic resonance imaging and clinical stage.
5. What Does the Prostate MRI Show?
The MRI report should identify the size, location and PI-RADS category of each suspicious lesion. It should also describe whether the lesion approaches or extends beyond the prostate capsule, involves the seminal vesicles, affects the urethral region or appears in more than one part of the gland [5,10].
Patients should ask whether the MRI findings agree with the biopsy. A high-suspicion lesion with only a limited low-grade biopsy result may require targeted resampling, while an MRI that shows no suspicious lesion does not completely exclude clinically significant cancer.
When active surveillance is proposed, the baseline MRI becomes an important comparison for future scans. When focal treatment is proposed, the lesion must be sufficiently well defined for accurate targeting, and the untreated prostate must still undergo continued surveillance.
6. Which Nonsurgical Options Am I Actually Eligible For?
Eligibility should be discussed separately for active surveillance, external-beam radiotherapy, stereotactic body radiotherapy, brachytherapy, hormone treatment and focal ablation. These approaches have different indications and should not be grouped together as equivalent alternatives to surgery [4,5,10].
Active surveillance is most appropriate for carefully selected localised cancers with favourable pathology and reliable follow-up. Radiotherapy can provide curative treatment for many low-, intermediate- and high-risk localised cancers, with hormone treatment added when the risk warrants it. Brachytherapy requires suitable prostate anatomy and urinary function, while focal treatment generally requires a well-localised target and detailed biopsy mapping [4,5,10].
A patient should request consultation with a radiation oncologist before accepting the conclusion that prostatectomy is the only curative option. Men considering focal therapy should ask whether the procedure is recommended within an established programme and how residual or recurrent disease will be detected.
7. What Is the Risk of Progression if Treatment Is Deferred?
The risk of progression depends on Grade Group, cancer volume, PSA density, magnetic resonance imaging, clinical stage, age, general health and the reliability of follow-up. A patient with low-volume Grade Group 1 disease usually has a different progression risk from someone with extensive Grade Group 2 disease or any Grade Group 3–5 cancer [5,10].
The ProtecT trial found low prostate-cancer-specific mortality after monitoring, surgery or radiotherapy at 15 years, but metastases and clinical progression occurred more often in the monitoring group. Patients should therefore understand that surveillance may safely delay treatment for many men while still carrying a greater likelihood of later progression or intervention [2].
The clinician should explain the estimated absolute risk rather than using vague descriptions such as “slow growing.” Patients should also ask how age and competing illnesses affect the expected benefit of immediate treatment.
8. Which Finding Would Trigger Active Treatment?
A surveillance plan should define the circumstances that would lead to radiotherapy, surgery or another definitive treatment. Possible triggers include pathological upgrading, increasing cancer volume, development of cribriform or intraductal features, MRI progression, evidence of extension outside the prostate or a concerning PSA pattern supported by further investigation [5,10].
A PSA increase alone should not automatically trigger treatment without considering infection, prostate volume, urinary retention, laboratory variation and testosterone. Persistent or rapid PSA progression generally warrants repeat testing, clinical review, imaging and possible biopsy rather than continuation of an unchanged plan [10].
Patients should ask how quickly treatment can begin if progression is confirmed. Surveillance is safest when there is a clear route to definitive treatment before the disease becomes substantially more difficult to control.
9. How Could Each Option Affect Urinary, Bowel and Sexual Function?
Prostatectomy, radiotherapy, brachytherapy, focal ablation and hormone treatment have different functional effects. Surgery is more strongly associated with early urinary incontinence and erectile dysfunction, while radiotherapy may produce urinary irritation, bowel symptoms and gradual sexual dysfunction. Hormone treatment can affect libido, erections, energy, muscle, bone and metabolic health [4,5,10].
Baseline urinary flow, continence, bowel health and sexual function should be documented before treatment. A man with substantial obstruction may not be an ideal candidate for some forms of brachytherapy, while previous pelvic radiotherapy or active inflammatory bowel disease may affect the suitability of external-beam treatment.
Patients should ask about both short-term and long-term effects, the probability of recovery, available rehabilitation and whether the proposed treatment may limit future salvage options.
10. How Will Ayurvedic Treatment Be Coordinated With Oncology Care?
An individualised Ayurvedic plan should begin only after the pathology, stage, PSA history, imaging and current oncology recommendation have been reviewed. The treatment objective should be defined according to whether the patient is under active surveillance, receiving radiotherapy, taking hormone treatment or being treated for recurrent or metastatic disease.
Every prescribed herb, extract, Avaleha, bhasma and supplement should be reviewed against the patient’s medicines, liver and kidney function, blood counts, glucose, bleeding risk and hormone-sensitive treatment. Products promoted for increasing testosterone or male vitality require particular caution when androgen suppression is part of the oncology plan.
Patients should ask which measurements will be used to judge response. Urinary improvement, better appetite, increased strength and reduced fatigue are clinically meaningful, but cancer control requires serial PSA interpretation, appropriate imaging, repeat biopsy when indicated and continued specialist follow-up. The treatment plan should also state which laboratory, pathological or radiological findings would require modification or discontinuation of the Ayurvedic medicines [1,4,10].
Nonsurgical Treatment for Prostate Cancer Review

A nonsurgical treatment for prostate cancer review is appropriate when a patient wants to determine whether active surveillance, radiotherapy, brachytherapy, focal treatment, hormone therapy, systemic treatment or an individualised Ayurvedic programme may be considered instead of, before or after prostate surgery. The purpose is not simply to confirm that an operation can be avoided, but to identify a clinically appropriate pathway that matches the cancer’s Grade Group, stage, tumour volume, biological behaviour and treatment objective [4,5,10].
When a Review Is Most Valuable
A review is particularly valuable soon after diagnosis, before a permanent treatment decision has been made. Men who have been advised to undergo radical prostatectomy may benefit from an independent assessment of whether their records also support active surveillance or curative radiotherapy. A radiation-oncology opinion is important because many localised prostate cancers can be treated definitively without removing the prostate [2,4,5,10].
Men with Grade Group 1 disease may request a review to determine whether active surveillance is sufficiently safe and whether the proposed monitoring schedule includes appropriate PSA testing, magnetic resonance imaging and repeat biopsy. The assessment should distinguish genuinely low-volume disease from cancer that appears low grade but has substantial bilateral involvement, high PSA density, suspicious imaging or incomplete biopsy sampling [5,10].
Selected men with Grade Group 2 disease may require a more detailed second opinion because eligibility for surveillance depends on the proportion of Gleason pattern 4, number of involved cores, percentage of cancer in each core, magnetic resonance imaging findings and absence of cribriform or intraductal carcinoma. A recommendation based only on the label “Gleason 3+4” is insufficient for deciding whether treatment can safely be deferred [5,10].
A review may also be useful when specialists have provided different recommendations. One clinician may favour surgery, another may recommend radiotherapy, and a third may consider surveillance. These differences do not necessarily indicate that one opinion is incorrect. They may reflect uncertainty at the boundary between risk groups, differences in treatment expertise or different interpretations of the patient’s life expectancy, baseline function and priorities.
Men with a rising PSA after prostatectomy may request assessment of whether the pattern is consistent with biochemical recurrence and whether early salvage radiotherapy should be discussed. Patients with suspected recurrence after previous radiotherapy may require evaluation for repeat imaging, biopsy confirmation, salvage focal treatment, systemic treatment or another specialised approach [4,10].
Patients already receiving androgen-deprivation therapy, chemotherapy, androgen-receptor pathway inhibitors or radioligand treatment may request review before adding Ayurvedic medicines. In this setting, the main questions include whether the proposed formulation is compatible with the oncology regimen, whether liver, kidney or bone-marrow function permits its use and whether any ingredient may interfere with the therapeutic purpose of androgen suppression.
Preparing the Clinical Record
The review should begin with the original prostate-biopsy report rather than a summary written from memory. The report must show the Gleason score, Grade Group, number and location of positive cores, percentage or length of cancer in each core and any reported cribriform, intraductal, perineural or other significant pathological findings. Pathology slides or digital images may be required when expert re-evaluation could alter the treatment decision.
Every PSA result should be submitted with its date. The record should also state whether the patient had a urinary infection, catheterisation, urinary retention, prostate biopsy or another procedure near the time of testing. Use of finasteride, dutasteride, testosterone therapy, androgen-deprivation therapy or other hormone-directed medicines must be disclosed because these treatments can substantially alter PSA interpretation.
Prostate volume and PSA density should be included when available. A PSA result that initially appears concerning may carry a different implication in a markedly enlarged prostate than in a small gland. PSA density cannot replace pathology or imaging, but it can strengthen or weaken the case for continued surveillance when interpreted with the other findings [5,10].
The multiparametric magnetic resonance imaging report should identify each lesion’s size, location and PI-RADS category and should comment on extracapsular extension, seminal-vesicle involvement and suspicious lymph nodes. Original images are preferable when the written report is brief, when the MRI and biopsy findings do not agree or when focal treatment is being considered.
Available PSMA PET/CT, computed tomography, bone-scan or other staging results should be included without assuming that a negative scan excludes microscopic disease. Imaging sensitivity depends on lesion size, location, PSA and previous treatment. A negative PSMA PET/CT at a low PSA may still be compatible with microscopic local or regional recurrence [4,10].
Previous treatment records should state the type and date of surgery, radiation dose and field, hormone injections, oral cancer medicines, chemotherapy, focal treatment and any serious adverse effects. A patient who has already received radiotherapy or prostatectomy requires a different eligibility assessment from someone with an untreated prostate.
Recent laboratory tests should include complete blood count, kidney function, liver function and glucose assessment. Testosterone is essential when the patient is receiving or recovering from androgen-deprivation therapy. Additional metabolic, cardiovascular and bone-health investigations may be needed when long-term hormone treatment is being used [4,10].
The complete medicine list should include prescribed drugs, non-prescription medicines, vitamins, protein or bodybuilding products, herbal supplements and medicines obtained from another Ayurvedic practitioner. Products marketed for testosterone enhancement, male vitality or sexual performance require particular scrutiny in hormone-sensitive prostate cancer.
Determining the Treatment Objective
The first clinical decision is whether the intended pathway is surveillance, curative treatment, salvage treatment, systemic disease control or symptom relief. These objectives are not interchangeable. A patient with favourable localised disease may reasonably seek to avoid unnecessary treatment, while a patient with high-risk or metastatic cancer may require prompt active treatment even when surgery is not part of the plan [4,5,10].
For active surveillance, the review should determine whether the pathology and imaging are sufficiently favourable and whether the patient can complete the required follow-up. Continued surveillance may be reasonable when cancer volume remains limited and there is no pathological or radiological evidence of significant progression. Surveillance becomes unsafe when monitoring is incomplete or when adverse disease features are ignored.
For curative radiotherapy, the assessment should determine whether the cancer remains within a treatable local or locally advanced field and whether external-beam radiotherapy, stereotactic body radiotherapy or brachytherapy warrants specialist discussion. Baseline urinary obstruction, previous pelvic treatment, bowel disease, prostate anatomy and the possible need for hormone treatment affect the choice of radiation technique [3–5,10].
For postoperative recurrence, the review should determine whether the PSA pattern, surgical pathology and imaging support timely salvage radiotherapy. Waiting for a visible tumour to appear on imaging may not always be appropriate because microscopic recurrence can exist below the detection threshold of contemporary scans [4,10].
For metastatic disease, the review should establish whether treatment is directed at hormone-sensitive or castration-resistant cancer and whether current systemic therapy adequately addresses the disease burden. A nonsurgical pathway in this setting may be intensive and can include several systemic medicines, prostate-directed radiotherapy in selected circumstances and treatment of symptomatic metastatic sites [4,10].
Assessing Ayurvedic Suitability
An Ayurvedic treatment plan should be considered only after the modern diagnosis and treatment objective are clear. The patient’s pathology, imaging and current oncology recommendation determine whether the Ayurvedic programme is being considered during active surveillance, alongside curative radiotherapy, during hormone treatment or as part of care for recurrent or advanced disease.
The published Ayurvedic prostate-cancer case provides evidence of a documented favourable outcome in one carefully described patient with small-volume, Grade Group 1, clinical T1 disease. It does not establish that a similar approach is appropriate for a man with extensive Grade Group 2 cancer, Grade Group 3–5 disease, lymph-node involvement or metastases [1].
Varuna–Kanchanara Rasayana Avaleha is not automatically prescribed to every patient requesting nonsurgical treatment. Its suitability depends on urinary findings, digestive tolerance, metabolic health, blood counts, liver and kidney function, current medicines and the ability to complete objective cancer monitoring. The proportions and accompanying ingredients may require substantial modification according to the clinical context.
A patient receiving androgen-deprivation therapy requires exclusion of ingredients or supplements with possible androgenic or testosterone-enhancing activity. A patient receiving radiotherapy may require changes to avoid worsening diarrhoea, urinary irritation, dehydration or mucosal symptoms. Chemotherapy, targeted treatment and radioligand therapy require additional attention to blood counts, infection risk, liver function, kidney function and treatment timing.
Selected herbo-mineral preparations should be considered only when there is a defined clinical rationale, verified manufacturing quality and capacity for laboratory monitoring. Normal baseline organ function does not remove the need for follow-up testing, particularly when treatment is prolonged or combined with prescribed oncology medicines.
The Ayurvedic plan should contain predefined measures of benefit. These may include urinary function, body weight, appetite, strength and quality of life, but cancer response must continue to be assessed separately through PSA, testosterone where relevant, imaging and repeat biopsy when clinically indicated. A treatment should not be continued unchanged solely because the patient feels better.
Clinical Findings That May Change the Recommendation
The review may determine that additional information is required before any treatment recommendation can be made. This can occur when the biopsy did not adequately sample an MRI-visible lesion, the pathology report lacks Grade Group or pattern 4 details, imaging quality is inadequate or the clinical findings conflict with one another. Repeat imaging, pathology review or another biopsy may be safer than making a treatment decision from incomplete evidence.
The review may also determine that active oncology treatment should not be delayed. Grade Group 3–5 disease, extensive pattern 4, intraductal or cribriform carcinoma, extracapsular extension, seminal-vesicle invasion, lymph-node involvement or distant metastases generally require discussion of definitive or systemic treatment rather than a surveillance-only pathway [4,5,10].
Progression during an existing nonsurgical programme may require a change in strategy. Pathological upgrading, increasing tumour volume, a growing MRI lesion, new extracapsular disease, biochemical recurrence supported by further assessment or development of metastatic lesions should prompt reconsideration of radiotherapy, surgery, systemic therapy or another appropriate intervention [4,5,10].
An abnormal PSA should be investigated rather than interpreted in isolation. Infection, urinary retention, recent procedures, testosterone recovery and treatment effects can alter PSA, while genuine progression can occasionally occur without a dramatic PSA rise. The decision should be based on the complete biochemical, pathological, radiological and clinical pattern.
When Local Medical Care Takes Priority
A remote review must not delay urgent treatment. Inability to pass urine, fever with urinary symptoms, heavy haematuria, severe or rapidly increasing bone pain, new leg weakness, numbness, difficulty walking or loss of bladder or bowel control requires immediate local medical assessment. These symptoms may indicate urinary obstruction, severe infection, bleeding, fracture or spinal cord compression [4,10].
Patients with rapidly worsening kidney function, jaundice, persistent vomiting, severe dehydration, confusion, chest pain or shortness of breath also require local evaluation before continuing or changing an Ayurvedic medicine. Treatment-related toxicity can become serious even when the cancer markers appear stable.
International patients should maintain access to a local urologist, radiation oncologist or medical oncologist according to the disease stage. Biopsy, radiation planning, hormone injections, systemic treatment, emergency procedures and management of acute complications must remain available in the patient’s home country.
FAQs
Nonsurgical treatment for prostate cancer may include active surveillance, external-beam radiotherapy, stereotactic radiotherapy, brachytherapy, focal ablation, hormone therapy, systemic medicines and individualised Ayurvedic care. Eligibility depends on the biopsy Grade Group, stage, cancer volume, PSA pattern, imaging, general health and treatment goal.
Can Prostate Cancer Be Cured Without Surgery?
Yes. Many localised prostate cancers can be treated with curative intent using external-beam radiotherapy, stereotactic radiotherapy or brachytherapy. Carefully selected low-risk cancers may also be monitored safely for long periods through active surveillance, although surveillance is not the same as confirmed cure.
Who Is Eligible for Active Surveillance?
Active surveillance is most suitable for men with low-volume, low-grade cancer confined to the prostate, reassuring MRI findings, favourable PSA density and no aggressive pathological features. The patient must also be willing to complete regular PSA testing, repeat imaging and further biopsy when clinically required.
Can Gleason 3+4 Prostate Cancer Be Managed Without Surgery?
Yes. Gleason 3+4 prostate cancer can often be treated with curative radiotherapy instead of prostatectomy. Some carefully selected patients with minimal pattern 4, low tumour volume, favourable MRI findings and no cribriform or intraductal carcinoma may also be considered for active surveillance.
Is Gleason 4+3 Suitable for Active Surveillance?
Gleason 4+3 disease is generally less suitable for active surveillance because the more aggressive pattern 4 is dominant. Patients may still avoid surgery through curative radiotherapy, often combined with hormone treatment according to the stage, PSA, tumour volume and other risk factors.
Is Radiotherapy as Effective as Prostate Surgery?
For many men with localised prostate cancer, radiotherapy and prostatectomy are both potentially curative. The better option depends on cancer risk, urinary function, bowel health, sexual priorities, prostate anatomy, general fitness and the possible need for hormone treatment.
Can a High PSA Be Treated Without Removing the Prostate?
Yes. A high PSA does not automatically require prostate removal. Treatment depends on the biopsy Grade Group, prostate volume, PSA density, MRI findings, disease stage and possible benign causes such as infection, inflammation or urinary retention. Curative radiotherapy may remain an option even when PSA is elevated.
What Is the Difference Between Active Surveillance and Watchful Waiting?
Active surveillance aims to preserve the possibility of curative treatment if the cancer progresses. Watchful waiting usually focuses on controlling symptoms in men whose frailty, other illnesses or limited life expectancy make radical treatment less beneficial.
Is SBRT Suitable for Every Prostate Cancer Patient?
No. Stereotactic body radiotherapy is suitable for selected patients with localised prostate cancer. Significant urinary obstruction, previous prostate procedures, difficult anatomy, inflammatory bowel disease, pelvic lymph-node involvement or extensive high-risk disease may require another radiation schedule or treatment approach.
Who May Qualify for Brachytherapy?
Brachytherapy may suit men with localised prostate cancer, manageable prostate size, acceptable urinary function and anatomy that permits accurate placement of radioactive sources. Severe obstruction, extensive previous prostate surgery, major bleeding risk or unsuitable pelvic anatomy may reduce eligibility.
Who May Qualify for Focal Therapy?
Focal therapy may be considered when clinically significant cancer appears confined to a clearly defined area of the prostate and detailed biopsy assessment shows no important disease elsewhere. Continued PSA testing, MRI and repeat biopsy remain necessary because untreated prostate tissue can still contain or later develop cancer.
Can Surgery Still Be Performed After Active Surveillance?
Yes. Surgery or radiotherapy can usually be introduced if surveillance identifies pathological upgrading, increasing cancer volume, MRI progression or extension beyond the prostate. The purpose of surveillance is to delay unnecessary treatment without losing the opportunity for cure.
What Happens if PSA Rises During Active Surveillance?
A rising PSA should be confirmed and interpreted with prostate volume, PSA density, infection status, urinary retention, recent procedures and MRI findings. Persistent or rapid change may lead to repeat imaging and biopsy, but PSA alone should not automatically determine treatment failure.
What Happens if PSA Rises After Radiotherapy?
A temporary PSA rise can occur after radiotherapy and may later fall without further treatment. Persistent elevation must be interpreted against the lowest post-treatment PSA, the time since treatment, testosterone level, symptoms and imaging findings before recurrence is diagnosed.
Can Ayurveda Be Used During Active Surveillance?
Individualised Ayurvedic treatment may be considered during active surveillance when the complete pathology, PSA history, MRI findings and monitoring schedule have been reviewed. Urinary improvement, better sleep or increased strength may be valuable, but cancer response must still be assessed through PSA, imaging and biopsy when indicated.
Can Ayurvedic Treatment Be Combined With Radiotherapy?
It may be considered after the complete formulation has been reviewed for interactions, bowel effects, urinary irritation, bleeding risk and liver or kidney function. Persistent diarrhoea, rectal bleeding, urinary retention, infection or dehydration requires medical assessment and treatment modification.
Can Ayurvedic Treatment Be Combined With Hormone Therapy?
It may be combined only after each ingredient has been assessed against the purpose of androgen-deprivation therapy. Products promoted for increasing testosterone, male vitality or sexual performance may conflict with treatment intended to suppress androgen signalling.
Can Ayurvedic Treatment Replace Oncology Monitoring?
No. Ayurvedic treatment should not replace PSA testing, imaging, pathology review, testosterone assessment or specialist follow-up. Symptom relief alone cannot confirm cancer regression, remission or cure.
What Nonsurgical Treatment Is Available After Prostate Surgery?
A rising PSA after prostatectomy may be treated with salvage radiotherapy, sometimes combined with pelvic-node radiation or temporary hormone therapy. Eligibility depends on the original pathology, surgical margins, PSA pattern, Grade Group and current imaging findings.
What Nonsurgical Treatment Is Available After Previous Radiotherapy?
Selected patients with confirmed local recurrence may be considered for salvage brachytherapy, cryotherapy, high-intensity focused ultrasound, repeat radiation or systemic treatment. The choice depends on the location of recurrence, previous radiation exposure, urinary function, bowel health and whether the cancer has spread.
Can Metastatic Prostate Cancer Be Treated Without Surgery?
Yes. Surgery is not usually the main treatment for metastatic prostate cancer. Most patients require hormone therapy combined, when appropriate, with androgen-receptor medicines, chemotherapy, targeted treatment, radiopharmaceutical therapy or radiotherapy.
Can International Patients Be Assessed Without Travelling?
An initial assessment can often be completed from the biopsy report, PSA history, prostate MRI, staging scans, previous treatment records, current medicines and recent blood tests. Remote review cannot replace physical examination, biopsy, radiation planning, emergency care or procedures that must be performed locally.
When Is Urgent Medical Care Required?
Urgent assessment is required for inability to pass urine, heavy bleeding, fever with urinary symptoms, severe new bone or back pain, leg weakness, numbness, difficulty walking or loss of bladder or bowel control. These symptoms may indicate obstruction, infection, fracture, spinal cord compression or advancing disease.
References
1. Anand, S., Anjana, C. S., Mythri, H. S., & Galib, R. (2026). Complete tumor regression with exclusive Ayurvedic treatment in adenocarcinoma of prostate: A case report. Journal of Medical Case Reports, 20, Article 207.
Brief: This case report describes a 45-year-old man with a small, biopsy-confirmed Gleason 3+3, clinical T1 prostate adenocarcinoma. The authors reported absence of the previously identified malignant focus on biopsy after nine months of Ayurvedic treatment and approximately 12 years without documented recurrence. As a single case without a control group, it cannot establish a general treatment response rate.
2. Hamdy, F. C., Donovan, J. L., Lane, J. A., Metcalfe, C., Davis, M., Turner, E. L., Martin, R. M., Young, G. J., Walsh, E. I., Bryant, R. J., Bollina, P., Doble, A., Doherty, A., Gillatt, D., Gnanapragasam, V., Hughes, O., Kockelbergh, R., Kynaston, H., Paul, A., … Neal, D. E. (2023). Fifteen-year outcomes after monitoring, surgery, or radiotherapy for prostate cancer. The New England Journal of Medicine, 388(17), 1547–1558.
Brief: The ProtecT trial found low prostate-cancer-specific mortality after active monitoring, prostatectomy or radiotherapy at 15 years. However, metastases and clinical progression occurred more frequently with monitoring, demonstrating the importance of careful selection and structured follow-up.
3. van As, N., Griffin, C., Tree, A., Patel, J., Ostler, P., van der Voet, H., Loblaw, A., Chu, W., Ford, D., Tolan, S., Jain, S., Camilleri, P., Kancherla, K., Frew, J., Chan, A., Naismith, O., Armstrong, J., Staffurth, J., Martin, A., … Hall, E. (2024). Phase 3 trial of stereotactic body radiotherapy in localized prostate cancer. The New England Journal of Medicine, 391(15), 1413–1425.
Brief: The PACE-B trial found five-fraction stereotactic body radiotherapy noninferior to longer radiotherapy schedules for biochemical or clinical failure in selected low- and intermediate-risk localised prostate cancer. Late grade 2 or higher genitourinary toxicity was more frequent with SBRT, so convenience must be balanced against urinary risk.
4. PDQ Adult Treatment Editorial Board. (2025, May 14). Prostate cancer treatment (PDQ®)–Health professional version. National Cancer Institute.
Brief: This regularly reviewed, peer-reviewed clinical summary covers stage-specific management, including active surveillance, radiotherapy, brachytherapy, hormone therapy, recurrent disease and metastatic prostate cancer. The NCI specifies that PDQ is an evidence summary rather than a formal clinical-practice guideline.
5. National Institute for Health and Care Excellence. (2021, December 15). Prostate cancer: Diagnosis and management (NICE Guideline NG131).
Brief: This UK guideline provides recommendations on diagnostic assessment, risk classification, active surveillance, radical radiotherapy, prostatectomy, hormone treatment and follow-up. It supports shared decision-making according to cancer risk, general health and treatment-related effects.
6. Canadian Cancer Society. (n.d.). Treatments for localized prostate cancer. Retrieved October 25, 2026.
Brief: This Canadian patient resource explains active surveillance, watchful waiting, surgery, radiation therapy and hormone therapy for localised prostate cancer. It supports the country-specific discussion of nonsurgical treatment pathways in Canada.
7. National University Cancer Institute, Singapore. (2024, September 24). Prostate cancer.
Brief: This Singapore-based clinical resource describes risk-adapted management, including active surveillance for selected localised disease, radiation therapy, systemic treatment and selected energy-ablation procedures. It emphasises multidisciplinary and individualised treatment selection.
8. Cancer Council Australia. (2026). Understanding prostate cancer: A guide for people with cancer, their families and friends.
Brief: This Australian guide covers active surveillance, watchful waiting, surgery, radiation therapy, androgen-deprivation therapy and treatment for advanced disease. It notes that active surveillance is usually considered for Grade Group 1 disease and may also be offered to selected Grade Group 2 patients.
9. National Health Service. (2025, July 31). Treatment for prostate cancer.
Brief: This UK patient resource explains monitoring, surgery, radiotherapy, hormone therapy, chemotherapy and selected focal approaches. It supports clear patient-facing distinctions between surveillance, active treatment and symptom-directed care.
10. European Association of Urology. (2026). EAU guidelines on prostate cancer. EAU Guidelines Office.
Brief: The 2026 EAU guideline provides current European recommendations for diagnosis, Grade Group and risk classification, active surveillance, definitive local treatment, recurrence, metastatic disease and follow-up. It is a principal source for the article’s eligibility and monitoring criteria.
11. Caraka. (1988). Agniveśa’s Caraka Saṃhitā: Text with English translation and critical exposition based on Cakrapāṇi Datta’s Āyurveda Dīpikā (R. K. Sharma & B. Dash, Trans.; Vol. 3, Cikitsā Sthāna). Chowkhamba Sanskrit Series Office.
Brief: Cikitsā Sthāna, Chapter 1, is the principal classical source cited for Rasāyana principles. It provides the traditional therapeutic framework but does not describe or establish a modern prostate-cancer treatment protocol.
12. Śārṅgadhara. (1984). Śārṅgadhara-saṃhitā: A treatise of Āyurveda (K. R. Srikantha Murthy, Trans.; 1st ed.). Chaukhambha Orientalia.
Brief: Madhyama Khaṇḍa, Chapter 8, describes Avaleha Kalpanā, including preparation principles, sweetening substances, signs of proper completion, dosage and adjuvants. It provides the pharmaceutical basis for an Avaleha dosage form, not evidence that a specific physician-designed formulation treats prostate cancer.
13. Suśruta. (1911). An English translation of the Sushruta Samhita (K. L. Bhishagratna, Trans. & Ed.; Vol. 2). Kunjalal Bhishagratna.
Brief: Nidāna Sthāna, Chapter 11, contains classical descriptions of Granthi, Apacī, Arbuda and Galagaṇḍa. These categories can inform traditional Ayurvedic reasoning about swellings and tissue growths, but they should not be presented as direct equivalents of biopsy-confirmed prostate adenocarcinoma.
14. Choi, Y. H., Han, D. H., Kim, S.-W., Kim, M.-J., Sung, H. H., Jeon, H. G., Jeong, B. C., Seo, S. I., Jeon, S. S., Lee, H. M., & Choi, H. Y. (2019). A randomized, double-blind, placebo-controlled trial to evaluate the role of curcumin in prostate cancer patients with intermittent androgen deprivation. The Prostate, 79(6), 614–621.
Brief: In this randomised trial, 1,440 mg of oral curcumin daily for six months reduced the proportion of patients with PSA progression during the administration period. It did not significantly prolong the overall off-treatment interval or significantly change PSA, testosterone or quality-of-life scores at six months.
15. Lu, M., Xia, L., Hua, H., & Jing, Y. (2008). Acetyl-keto-β-boswellic acid induces apoptosis through a death receptor 5-mediated pathway in prostate cancer cells. Cancer Research, 68(4), 1180–1186.
Brief: This laboratory study found that acetyl-keto-β-boswellic acid induced apoptosis in prostate-cancer cell lines through death-receptor and caspase-related pathways. It is preclinical evidence and does not demonstrate clinical effectiveness of Shallaki in patients.
16. Pang, X., Yi, Z., Zhang, X., Sung, B., Qu, W., Lian, X., Aggarwal, B. B., & Liu, M. (2009). Acetyl-11-keto-β-boswellic acid inhibits prostate tumor growth by suppressing vascular endothelial growth factor receptor 2-mediated angiogenesis. Cancer Research, 69(14), 5893–5900.
Brief: This preclinical study reported inhibition of VEGFR2-mediated angiogenesis and reduced prostate-tumour growth in experimental models. The findings support mechanistic research but cannot establish the effect, dose or safety of Boswellia preparations in prostate-cancer patients.
17. Kapur, P., Pereira, B. M. J., Wuttke, W., & Jarry, H. (2009). Androgenic action of Tinospora cordifolia ethanolic extract in prostate cancer cell line LNCaP. Phytomedicine, 16(6–7), 679–682.
Brief: In androgen-sensitive LNCaP cells, an ethanolic Tinospora cordifolia extract stimulated cellular proliferation and PSA secretion, while the antiandrogen flutamide reversed the PSA response. This in-vitro finding supports caution with Guduchi extracts in hormone-sensitive prostate cancer and during androgen-deprivation therapy, but it does not establish the effect of every preparation in humans.
18. Saper, R. B., Phillips, R. S., Sehgal, A., Khouri, N., Davis, R. B., Paquin, J., Thuppil, V., & Kales, S. N. (2008). Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA, 300(8), 915–923.
Brief: Detectable lead, mercury or arsenic was found in 20.7% of 193 Ayurvedic products purchased through the internet. The result applies to the sampled products rather than all Ayurvedic medicines, but it strongly supports verified sourcing, batch-specific contaminant testing and clinical monitoring for mineral-containing preparations.