HSV-1 vs HSV-2: The Differences That Matter Most
HSV-1 vs HSV-2 describes the two closely related types of herpes simplex virus that can affect the mouth, face, genital area, anal region, eyes, skin and, less commonly, the nervous system. HSV-1 is more often associated with oral herpes, while HSV-2 is more often associated with genital herpes. However, either virus can infect either location, so the viral type should never be assumed from the appearance or position of a blister alone [1,2].
For patients, the most important differences are not simply where each virus usually appears. The viral type can influence how the infection was probably acquired, how often genital symptoms may recur, how frequently asymptomatic shedding may occur and what counselling may be needed for a partner. The anatomical site remains equally important because oral HSV-1, genital HSV-1 and genital HSV-2 do not always behave in the same way [1,4].
What Are HSV-1 and HSV-2?
HSV-1 and HSV-2 belong to the same herpesvirus family and share many biological characteristics. Both can enter through microscopic breaks in the skin or through the moist lining of the mouth, genital tract, rectum or eyes. After initial replication near the site of entry, the virus can travel through sensory nerves and establish latency within a sensory nerve ganglion [1].
Latency means that the virus remains biologically present within nerve tissue even when no blister, ulcer, itching or burning is visible. At a later time, the virus may reactivate, travel back along the nerve and reach the skin or mucosal surface. Reactivation can produce a recognizable outbreak, a subtle symptom such as tingling or a skin fissure, or asymptomatic shedding without any noticeable change [1,6].
This shared ability to become latent explains why both HSV-1 and HSV-2 may produce long symptom-free intervals. It also explains why the absence of visible lesions does not always mean that transmission is impossible. A person may feel completely well while the virus is intermittently present at the oral or genital surface [1].
The two viruses are genetically distinct, but they are sufficiently similar that their lesions may look identical. Both may cause grouped fluid-filled blisters, shallow ulcers, redness, itching, burning, tenderness, pain during urination or local nerve discomfort. Symptoms alone cannot reliably establish whether an outbreak is caused by HSV-1 or HSV-2 [1,6].
The Main Difference Between HSV-1 and HSV-2
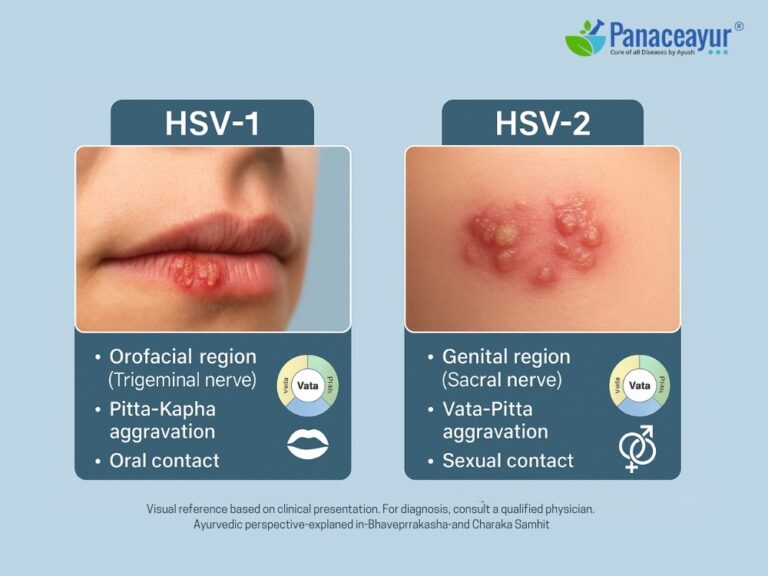
HSV-1 has a stronger epidemiological association with infection around the lips and mouth. It is commonly acquired through oral contact, often during childhood, and many people never remember having an obvious first outbreak. A person may therefore have HSV-1 antibodies without knowing when the infection occurred or whether it has ever produced symptoms [1,2].
HSV-2 has a stronger association with genital and anal infection and is predominantly transmitted through sexual skin-to-skin contact. Unlike oral HSV-1, HSV-2 infection generally indicates sexually acquired anogenital exposure, although the timing and source of infection cannot always be determined from a blood test or from the first recognized outbreak [1].
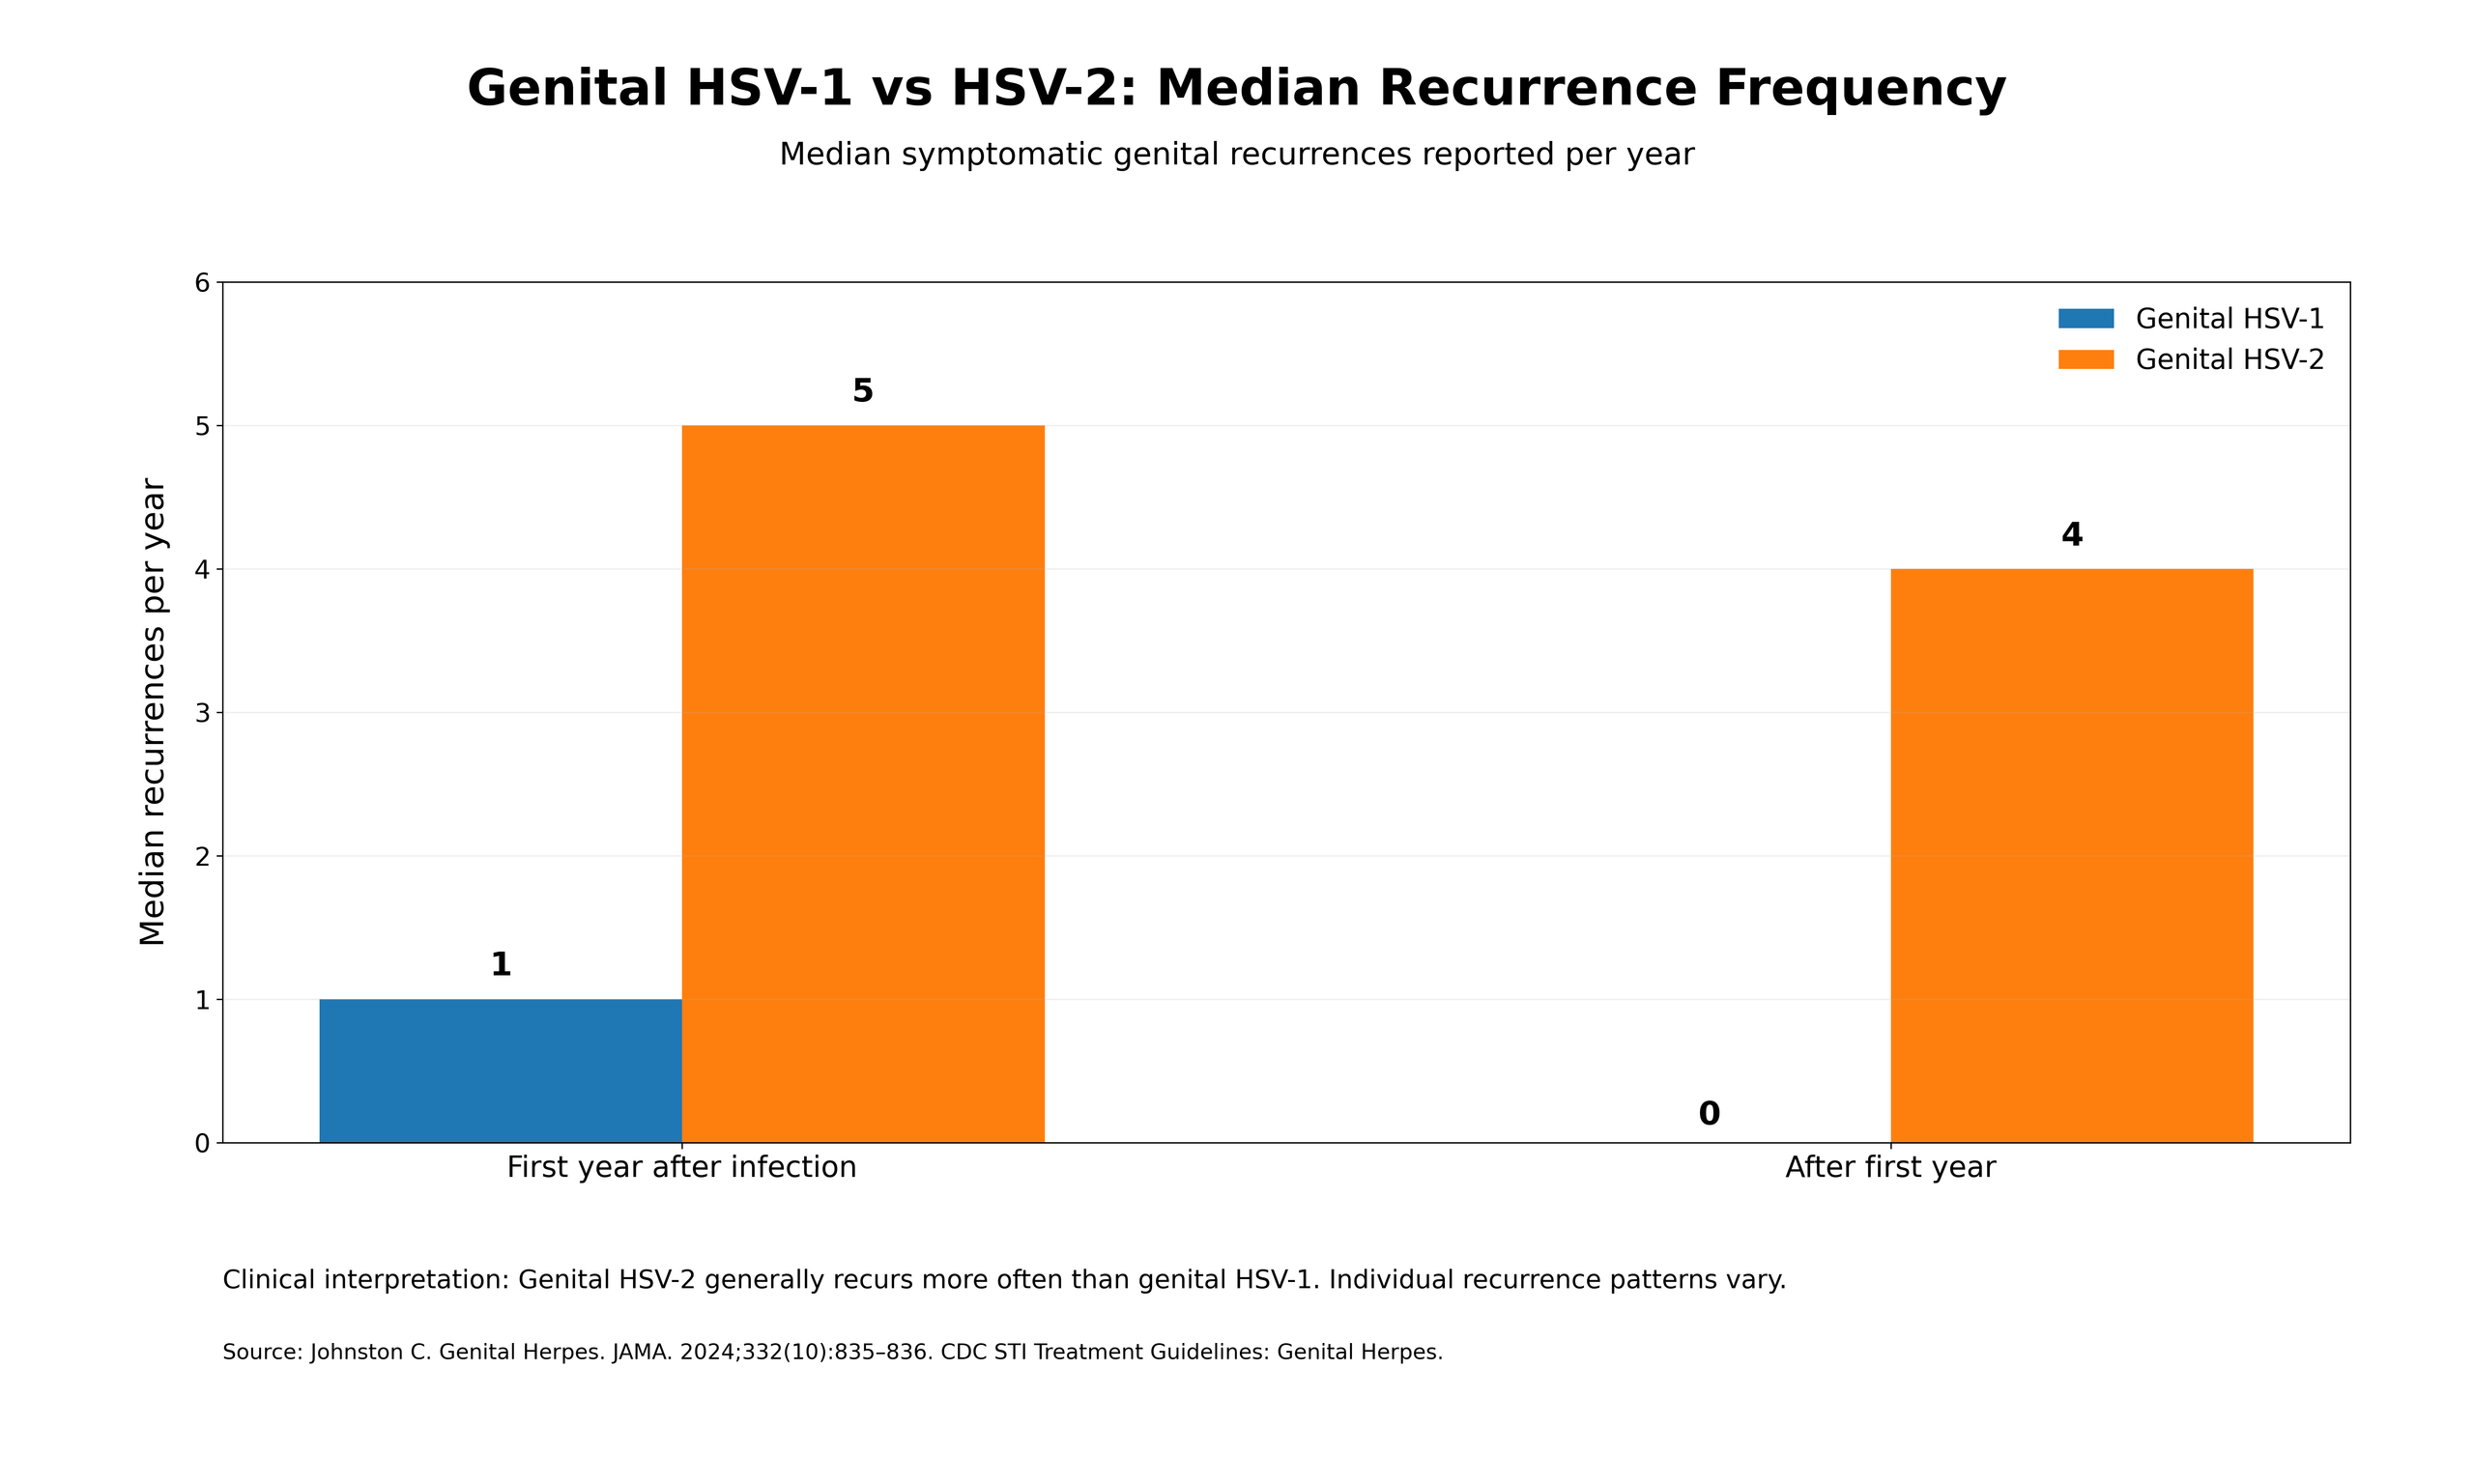
The greatest practical difference becomes apparent when the infection is located in the genital area. Genital HSV-2 generally causes more frequent recurrences and more persistent asymptomatic genital shedding than genital HSV-1. This does not mean that every patient with HSV-2 will have frequent outbreaks or that every genital HSV-1 infection will remain mild. It means that, at a population level, genital HSV-2 has a greater tendency to reactivate repeatedly in the genital region [1,4].

A clinical review reported a median of approximately five recurrences during the first year after symptomatic genital HSV-2 infection, compared with approximately one recurrence after genital HSV-1 infection. After the first year, the reported median was approximately four recurrences annually for HSV-2 and zero for genital HSV-1, although individual experiences can differ considerably [4].
Some patients with HSV-2 have no recognized outbreaks, while others experience recurrent genital ulcers, fissures, itching, sacral discomfort or painful urination. Similarly, a first episode of genital HSV-1 can be painful and extensive even though later genital recurrences are usually less frequent. The severity of the initial episode does not always predict the patient’s long-term recurrence pattern [1,4].
| Clinical Feature | HSV-1 | HSV-2 |
|---|---|---|
| Most common pattern | Most commonly oral/facial infection, but it can also cause genital herpes | Predominantly genital or anogenital infection |
| Usual transmission | Often acquired through oral contact; genital HSV-1 commonly follows oral-genital contact | Predominantly acquired through sexual skin-to-skin contact |
| Can infect the genital area? | Yes. HSV-1 is an important cause of genital herpes | Yes. This is the most typical clinical location for HSV-2 |
| Can infect the mouth? | Yes. Oral infection is the most common pattern | Yes, but oral HSV-2 is uncommon |
| Genital recurrence pattern | Usually less frequent after the first episode | Usually more frequent than genital HSV-1 |
| Median genital recurrences during the first year | Approximately 1 | Approximately 5 |
| Median genital recurrences after the first year | Approximately 0 per year | Approximately 4 per year |
| Asymptomatic genital shedding | Can occur, but generally declines substantially over time after genital HSV-1 infection | More frequent and may continue even when no blisters or ulcers are visible |
| Can HSV type be identified by appearance alone? | No. HSV-1 lesions cannot be reliably distinguished visually from HSV-2 lesions | No. HSV-2 lesions cannot be reliably distinguished visually from HSV-1 lesions |
| Preferred test when a fresh lesion is present | Type-specific lesion NAAT/PCR | Type-specific lesion NAAT/PCR |
| Meaning of a positive blood IgG result | Indicates previous HSV-1 exposure, but usually cannot determine whether infection is oral or genital | Usually supports previous HSV-2 infection; low-positive results may require confirmation |
| Does a positive IgG show when infection occurred? | No | No |
| Does a positive IgG identify who transmitted the infection? | No | No |
| Typical long-term counselling emphasis | Site of infection, recurrence history, oral-genital transmission and individual shedding risk | Recurrence, asymptomatic shedding, partner protection and transmission risk |
| Pregnancy relevance | Genital HSV-1 can cause neonatal herpes, particularly if newly acquired late in pregnancy | Genital HSV-2 is also important in pregnancy, especially when first acquired late in pregnancy |
| Potential complications | Keratitis, encephalitis, eczema herpeticum, neonatal herpes and severe disease in immunocompromised patients | Recurrent genital disease, aseptic meningitis, proctitis, sacral radiculitis, urinary retention and neonatal herpes |
| Overall clinical interpretation | Genital HSV-1 generally has a lower long-term recurrence and shedding burden than genital HSV-2 | Genital HSV-2 generally has the greater recurrence and asymptomatic shedding burden |
Why the Site of Infection Matters as Much as the Viral Type
The statement that HSV-1 is oral and HSV-2 is genital is an oversimplification. A more accurate assessment identifies both the viral type and the infected anatomical site.
Oral HSV-1 is the most familiar pattern and may cause cold sores around the lips, inflammation inside the mouth or subtle recurrent burning near the same facial area. Some patients experience warning symptoms such as tingling, tightness or sensitivity before a visible lesion appears.
Genital HSV-1 is commonly acquired when a partner with oral HSV-1 performs oral sex. Transmission can occur during an active cold sore, but it may also occur during asymptomatic oral shedding. Once HSV-1 establishes infection in the genital region, the first episode may resemble genital HSV-2, making laboratory typing important [1].
Genital HSV-2 is usually acquired through genital-genital or genital-anal contact. It has a stronger tendency than genital HSV-1 to reactivate repeatedly in the genital region. This greater recurrence and shedding burden affects partner counselling, decisions about suppressive treatment and the patient’s understanding of transmission risk [1,4].
Oral HSV-2 is biologically possible but is considerably less common than genital HSV-2 or oral HSV-1. When HSV-2 infects the oral region, it generally recurs less frequently there than it does in the genital region. This further demonstrates that viral behaviour depends on the interaction between the HSV type and the anatomical site.
The site also influences the sensory nerve ganglion in which latency is established. Oral and facial infections usually involve sensory pathways serving the face, while genital and anal infections usually involve sacral sensory pathways. It is therefore inaccurate to state that HSV-1 always remains in one particular ganglion or that HSV-2 always remains in another. The location of the original infection is clinically important.
How Common Are HSV-1 and HSV-2?
HSV-1 is one of the most widespread lifelong viral infections. Approximately 3.8 billion people under 50 years of age, representing about 64% of the global population in that age group, are estimated to have HSV-1 infection [2].
Most HSV-1 infections are acquired orally, frequently during childhood or adolescence, through direct contact with oral secretions or infected skin. Because the first infection is often mild or unrecognized, many adults discover HSV-1 antibodies only when blood testing is performed for another reason.
A positive HSV-1 antibody result does not automatically mean that a person has genital herpes or that the infection was sexually acquired. The result may reflect an oral infection acquired many years earlier. Without a positive type-specific sample from a genital lesion, a blood test usually cannot determine whether HSV-1 is oral or genital [1].
Approximately 520 million people aged 15–49, representing about 13% of that population, are estimated to have HSV-2 infection [2]. HSV-2 prevalence differs across countries, age groups, sexes and populations, so an individual’s likelihood of infection cannot be judged from global estimates alone.
The global number of people with genital herpes is higher than the HSV-2 figure because genital herpes can be caused by either HSV-1 or HSV-2. Genital HSV-1 has become an important cause of first-episode genital herpes, particularly in populations where fewer people acquire oral HSV-1 during childhood and oral-genital sexual contact is common [2].
These prevalence figures should reduce stigma rather than create fear. HSV infection is common, and many people are unaware that they carry it. However, its high prevalence does not make accurate diagnosis, partner counselling, pregnancy planning or the assessment of recurrent symptoms less important.
Can HSV-1 Cause Genital Herpes?
HSV-1 can cause genital herpes, most commonly after oral-genital contact. A partner may transmit oral HSV-1 from the mouth to the genital area even when a visible cold sore is absent because viral shedding can occur between outbreaks [1].
The first episode of genital HSV-1 may cause painful blisters or ulcers, swollen lymph nodes, fever, body aches, painful urination and considerable genital tenderness. In some patients, however, the presentation is limited to a small fissure, local redness, itching or unexplained burning.
After the first episode, genital HSV-1 usually recurs less frequently than genital HSV-2. Asymptomatic genital shedding also tends to decline over time. This generally gives genital HSV-1 a more favourable long-term recurrence pattern, although transmission remains possible and individual outcomes vary [1,4].
A positive HSV-1 blood antibody result alone cannot prove that recurrent genital symptoms are caused by HSV-1. When a fresh genital blister, ulcer or erosion is present, a sample should be collected directly from the lesion for a type-specific nucleic acid amplification test whenever clinically appropriate [1].
Can HSV-2 Cause Oral Herpes?
HSV-2 can infect the mouth or throat, but this pattern is uncommon. Oral HSV-2 may be acquired through oral-genital exposure to a partner with genital HSV-2. Because HSV-2 is less biologically adapted to the oral region, repeated oral outbreaks are generally less common than recurrent genital HSV-2.
An oral lesion should not be labelled HSV-1 or HSV-2 solely from its appearance. Aphthous ulcers, angular cheilitis, traumatic ulcers, bacterial infections, allergic reactions and other dermatological conditions may resemble oral herpes. Laboratory confirmation is particularly valuable when the appearance is atypical, severe or recurrent.
Similarly, a genital lesion cannot be assumed to be HSV-2. Genital HSV-1, syphilis, friction injury, candidiasis, fixed drug eruption, inflammatory dermatoses and several other conditions may produce genital pain, erosion or ulceration. Clinical appearance alone can lead to both overdiagnosis and missed diagnosis [6].
Is HSV-2 Always More Severe Than HSV-1?
HSV-2 is not universally more severe. Its greater clinical significance in genital infection is mainly related to its higher average frequency of recurrence and shedding. The pain and extent of an individual outbreak can vary with either type.
HSV-1 can occasionally cause serious complications, including corneal infection, encephalitis, extensive infection in people with eczema and severe disease in immunocompromised patients. Genital HSV-1 can also produce a difficult first episode despite having a lower average rate of later recurrence [1].
HSV-2 may cause recurrent genital ulceration, proctitis, aseptic meningitis, sacral nerve inflammation or urinary retention. It is also associated with an increased risk of acquiring HIV because genital inflammation and mucosal disruption may facilitate HIV transmission [1].
For either viral type, the clinical risk becomes more important during pregnancy, in newborns, in people receiving chemotherapy or immunosuppressive treatment, and in patients with advanced immune deficiency. Eye pain, light sensitivity, visual changes, severe headache, neck stiffness, confusion, inability to urinate or rapidly spreading lesions require prompt medical assessment.
The phrase “which type is worse?” therefore has no single answer for every patient. Genital HSV-2 generally carries the greater long-term recurrence and transmission burden, while HSV-1 can still cause significant oral, ocular, neurological or first-episode genital disease.
Why an Ayurvedic Assessment Looks Beyond the HSV Type
From an Ayurvedic perspective, identifying HSV-1 or HSV-2 is clinically useful, but the laboratory label does not fully describe the patient’s illness pattern. Assessment also considers Prakriti, the individual’s constitutional pattern; Vikriti, the current imbalance; and Agni, the functional capacity responsible for digestion and metabolism.
Two patients with the same HSV type may have very different clinical presentations. One may experience heat, redness, burning and inflammatory lesions, while another may mainly report dryness, fissuring, nerve pain, fatigue, poor sleep or digestive disturbance. A third patient may remain asymptomatic despite a positive laboratory result.
Ayurvedic assessment may therefore examine the frequency and location of recurrence, bowel regularity, appetite, sleep, emotional stress, menstrual associations, skin and mucosal sensitivity, associated metabolic disorders and the patient’s tolerance of foods and medicines. This individualized approach should complement accurate viral diagnosis rather than replace appropriate testing.
Classical Ayurvedic descriptions of communicable disease, genital ulceration and spreading inflammatory disorders may offer useful clinical principles. They should not, however, be presented as exact ancient names for HSV-1 or HSV-2 because modern viral typing was not available when those texts were composed.
The distinction between HSV-1 and HSV-2 remains important because it helps estimate recurrence and shedding behaviour. The broader patient assessment remains equally important because the viral type alone cannot explain why one person has frequent symptoms while another remains clinically stable for years.
HSV-1 vs HSV-2 Symptoms

HSV-1 vs HSV-2 symptoms may appear identical when the viruses affect the same anatomical site. Both types can cause tingling, itching, burning, tenderness, grouped blisters, shallow ulcers, fissures and localized nerve discomfort. The appearance of a lesion cannot reliably determine whether it is HSV-1 or HSV-2, making type-specific testing important whenever a fresh lesion is available for sampling [1,6].
The symptom pattern is influenced by the viral type, the infected location, whether the episode is the first recognized outbreak or a recurrence, and the patient’s immune status. Genital HSV-2 generally produces more frequent recurrences than genital HSV-1, but either type can cause a painful first genital episode [1,4].
First Recognized Episode
A first recognized oral or genital episode may begin with tingling, burning, itching, tightness or unusual sensitivity before a visible lesion develops. This early warning period is commonly called the prodrome. Some patients recognize the same sensation in the same area before each recurrence, while others develop lesions without any warning.
A symptomatic first genital episode can cause multiple painful blisters or ulcers involving the vulva, vagina, cervix, penis, scrotum, buttocks, thighs, perineum or anal region. Nearby lymph nodes may become tender, and urination may be painful when urine passes over inflamed skin. Fever, fatigue, headache, muscle aches and a general feeling of illness may accompany a more extensive episode [1,6].
Internal genital lesions may not be visible without examination. For example, a woman may experience vaginal pain, discharge or burning during urination without seeing an external blister. A man may notice urethral discomfort or burning even when the visible skin changes are minimal. Perianal or rectal infection may produce pain during bowel movements, mucus discharge, rectal pressure or a persistent sensation of needing to pass stool [1,6].
The first recognized outbreak does not always represent a newly acquired infection. Some people develop mild or unrecognized symptoms during the initial infection and notice their first obvious episode months or years later. The timing of a visible outbreak therefore cannot reliably establish when the infection was acquired or identify the transmitting partner [1].
Genital HSV-1 and genital HSV-2 may be clinically indistinguishable during the first episode. A severe genital outbreak does not automatically mean that HSV-2 is present, and a mild episode does not prove HSV-1. A swab collected directly from a fresh blister, ulcer or erosion for type-specific NAAT/PCR provides more reliable information than appearance alone [1,6].
Recurrent and Atypical Symptoms
Recurrent episodes are usually shorter and less extensive than the first symptomatic episode. A patient may develop only one or two small lesions, localized itching, a brief burning sensation or tenderness that resolves before a typical blister becomes obvious. This can lead patients to mistake recurrent herpes for friction, shaving irritation, candidiasis, contact dermatitis, an ingrown hair or a minor skin injury [1,6].
Some recurrent lesions appear as narrow fissures rather than grouped blisters. For example, a patient may repeatedly notice a small painful crack at the vaginal opening, beneath the foreskin, near the anus or between the buttocks. When such a lesion repeatedly develops in the same location, particularly with preceding tingling or burning, HSV should be considered even when the appearance is not typical [6].
Other patients experience redness, swelling, rawness or a superficial erosion without a fluid-filled blister. Vulval sensitivity, penile burning, urethral discomfort, pain during intercourse or unexplained genital tenderness may also occur. These symptoms have several possible causes, so laboratory confirmation and examination are important before attributing them to HSV [1,6].
Oral HSV-1 most often causes recurrent cold sores around the lips or nearby facial skin. Symptoms may begin with tingling or tightness before small blisters develop and form a crust. Lesions inside the mouth, especially isolated ulcers on non-keratinized surfaces, may have other causes and should not automatically be labelled as herpes.

HSV-2 can affect the oral region, but recurrent oral HSV-2 is uncommon. An oral ulcer should therefore be assessed according to its location, recurrence pattern, exposure history and laboratory findings rather than being assigned a viral type solely from appearance.
Genital HSV-2 generally produces a greater long-term recurrence burden than genital HSV-1. Median recurrence estimates suggest approximately five genital HSV-2 recurrences during the first year compared with approximately one after genital HSV-1. Individual patterns remain highly variable: some patients with HSV-2 experience frequent symptoms, while others have few or no recognized recurrences [4].
Genital HSV-1 usually becomes less active after the first episode, although recurrence and asymptomatic shedding remain possible. A patient who has no further visible outbreak may still require counselling about transmission, especially during the months following a newly acquired genital infection [1,5].
Symptoms can also occur without visible blisters. Recurrent tingling, burning or sensitivity may reflect prodromal or mild reactivation, but similar sensations can arise from pelvic-floor dysfunction, vulvodynia, prostatitis, urinary disorders, neuropathy, dermatological disease or local irritation. Persistent symptoms without confirmed lesions require a broader differential diagnosis rather than repeated treatment based only on assumption.
In Ayurvedic assessment, the symptom pattern helps individualize treatment by documenting features such as burning, heat, redness, moisture, dryness, fissuring, nerve discomfort, digestive disturbance, sleep disruption and recurrence triggers. These clinical observations do not identify the HSV type and should be interpreted alongside appropriate virological testing.
Symptoms Requiring Urgent Assessment
Eye pain, redness, light sensitivity, excessive tearing or blurred vision requires urgent ophthalmic evaluation because ocular HSV can threaten the cornea and vision. A patient with a history of oral herpes should avoid touching the eyes after contacting a lesion and should wash the hands thoroughly [1].
Severe headache, neck stiffness, confusion, marked light sensitivity, weakness, altered consciousness or seizures require immediate medical assessment. Although uncommon, HSV can involve the meninges or brain and should not be managed as a routine skin outbreak when neurological symptoms are present [1].
Difficulty starting urination, inability to empty the bladder or complete urinary retention may occur when sacral nerve inflammation accompanies genital herpes. This requires prompt evaluation because bladder decompression and neurological assessment may be necessary.
Extensive, rapidly spreading or unusually persistent lesions require urgent review, particularly in patients receiving chemotherapy, corticosteroids, biological medicines or transplant-related immunosuppression. The same applies to patients with advanced immune deficiency or widespread eczema, in whom HSV may become more severe [1].
Any genital lesions, burning or suspected first outbreak during pregnancy should be reported promptly to the obstetric team. The clinical implications depend on whether the infection is newly acquired, the stage of pregnancy and whether lesions or prodromal symptoms are present near delivery [1].
Blisters, fever, poor feeding, unusual sleepiness, irritability, breathing difficulty or seizures in a newborn require emergency medical evaluation. Neonatal HSV may initially resemble other common illnesses and can progress rapidly without early treatment [1].
The absence of visible lesions should not be used as the only measure of recovery. Outbreak frequency, symptom intensity, symptom-free duration, asymptomatic periods, associated clinical changes and appropriately selected follow-up investigations should be considered together when evaluating long-term progress.
HSV-1 vs HSV-2 Recurrence and Shedding
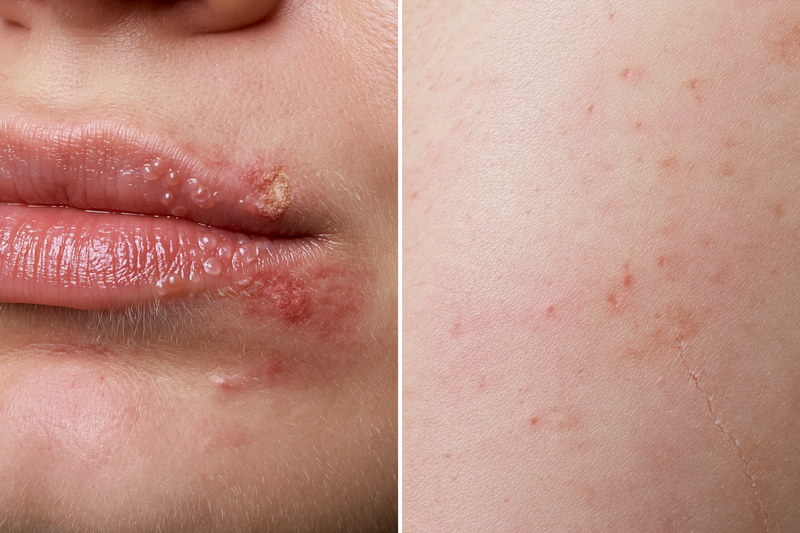
HSV-1 vs HSV-2 recurrence and shedding differ most clearly when the infection is genital. Genital HSV-2 usually reactivates and sheds more frequently than genital HSV-1, whereas genital HSV-1 activity commonly declines during the first year after infection. These are population-level patterns rather than fixed outcomes for every patient [1,4,5].
Recurrence describes the return of clinical symptoms after a symptom-free interval. Viral shedding describes the presence of virus on the skin or mucosal surface, with or without symptoms. A patient may therefore have a visible recurrence, experience only tingling or burning, or shed the virus without noticing any physical change [1,6].
How HSV Reactivation Appears
Reactivation does not always produce a complete sequence of tingling, blisters, ulcers and crusting. Some episodes cause only a small fissure, localized redness, mild itching or brief sensitivity at a familiar site. Other episodes remain entirely asymptomatic despite detectable virus at the genital, anal or oral surface [1,6].
Recurrent lesions often return within the same general nerve distribution. For example, a patient may repeatedly develop a small erosion on one side of the vulva, beneath the foreskin, near the anus or on a particular area of the buttock. The exact position can vary slightly, but the tendency to recur within a familiar region reflects reactivation through the affected sensory pathway [6].
The first recognized recurrence may appear months or years after acquisition. This means that a new outbreak does not necessarily indicate a recent infection, recent infidelity or transmission from the patient’s current partner. Laboratory results and symptoms generally cannot identify the exact date or source of an established infection [1,6].
Recurrence frequency often decreases with time, but the pattern is highly individual. One patient may experience several episodes during the first year and then remain symptom-free for long periods. Another may continue to have frequent mild symptoms. A third may have no recognized outbreak but may still experience intermittent asymptomatic shedding [1,6].
Genital HSV-1 Recurrence and Shedding
Genital HSV-1 generally produces fewer recurrent outbreaks than genital HSV-2. Some patients experience only the initial episode, while others develop occasional recurrent tingling, fissures, erosions or blisters. The lower average recurrence rate does not mean that every genital HSV-1 infection is symptom-free after the first episode [1,4].
A prospective study followed 82 people after a first episode of genital HSV-1. Genital HSV-1 was detected on 12.1% of sampled days approximately two months after the initial episode. At approximately eleven months, detection had declined to 7.1% of sampled days. Most shedding occurred without recognized genital symptoms [5].
The same study found that early genital shedding was more frequent among participants with a primary HSV-1 infection than among those who already had HSV-1 antibodies before the genital episode. This indicates that newly acquired genital HSV-1 may be more active during the early months, even when visible lesions have stopped [5].
For example, a patient may have one obvious genital HSV-1 outbreak followed by several months without blisters. This is a favourable clinical change, but early asymptomatic shedding may still occur. Partner counselling and risk-reduction measures therefore remain relevant, particularly during the first year [1,5].
The decline in genital HSV-1 shedding over time is clinically reassuring, but it cannot predict the exact risk on a specific day for an individual patient. Shedding is intermittent, and the absence of tingling, burning or lesions cannot guarantee that virus is not present at the genital surface [1,5].
Genital HSV-2 Recurrence and Shedding
Genital HSV-2 has a stronger tendency to produce recurrent anogenital symptoms. After a symptomatic first episode, the median recurrence rate has been reported at approximately four episodes per year, although some patients experience no recognized recurrence and others experience considerably more [4,6].
Recurrences may become shorter and less severe with time. A patient whose first episode involved multiple painful ulcers, fever and swollen lymph nodes may later experience only one small lesion or one day of tingling. A mild recurrence can still represent viral reactivation even when it does not resemble the first episode [1,6].
Asymptomatic HSV-2 shedding may occur from the external genital skin, cervix, urethra or anorectal region. In some patients, the number of asymptomatic shedding days exceeds the number of days with visible lesions. This helps explain why HSV-2 can be transmitted by someone who has no active blister and believes the infection is inactive [1,6].
HSV-2 shedding is generally most frequent during the first twelve months after acquisition, although intermittent shedding can continue later. A person with longstanding clinically silent HSV-2 may therefore have periods of viral activity without developing recognizable symptoms [1].
A patient with no history of obvious outbreaks may begin recognizing mild symptoms after learning that herpes can appear as a fissure, localized itching or brief burning. This does not necessarily mean that the infection has suddenly worsened. It may mean that previously overlooked manifestations are now being identified more accurately [6].
The recurrence pattern should be recorded before drawing conclusions about progression. Useful clinical details include the location, duration and intensity of each episode; whether lesions were present; whether a prodrome occurred; how long the symptom-free interval lasted; and whether the episode was confirmed with a lesion-based test.
Recognizing Individual Reactivation Patterns
Patients often associate episodes with periods of physical illness, sleep disruption, psychological strain, menstruation, prolonged friction or local irritation. Oral HSV-1 may also appear after intense ultraviolet exposure. These associations vary between individuals and should not be treated as universal causes.
A symptom diary can help distinguish repeated patterns from isolated coincidences. For example, if genital burning repeatedly appears after prolonged cycling, intercourse or inadequate sleep, those factors can be examined alongside lesion findings and laboratory results. One episode occurring after a particular food or stressful day is not enough to establish a reliable trigger.
Dietary advice should not be based on the assumption that every patient reacts to the same foods. A food tolerated without difficulty by one person may aggravate digestive or inflammatory symptoms in another. Ayurvedic dietary planning considers Prakriti, Vikriti, Agni, bowel function, current symptoms and the observed relationship between food intake and recurrence rather than applying one restrictive list to every patient.
Frequent symptoms also require assessment for conditions that may resemble or coexist with herpes. Recurrent candidiasis, bacterial infection, contact dermatitis, lichen sclerosus, fissuring, vulvodynia, pelvic-floor dysfunction, prostatitis and urinary disorders can produce overlapping discomfort. Persistent burning should not automatically be counted as an HSV recurrence without suitable examination or lesion testing [6].
Clinical Meaning of Asymptomatic Shedding
Asymptomatic shedding means that viral activity can occur without visible skin changes. It does not mean that transmission occurs during every contact, but it creates a potential route of transmission when no outbreak is apparent [1].
The likelihood of shedding is influenced by the viral type, anatomical site, time since acquisition and individual biological variation. Genital HSV-2 generally sheds more frequently than genital HSV-1, while genital HSV-1 shedding commonly declines more rapidly during the first year [1,5].
Symptoms cannot identify every shedding episode. A person may have tingling without detectable shedding, and another may shed HSV without tingling. Daily symptoms therefore cannot be used as an exact biological test of whether viral activity is present on a particular day.
The absence of visible blisters remains clinically meaningful because it may reflect reduced symptomatic activity and improved quality of life. However, visible lesions are only one component of long-term evaluation. Recurrence frequency, symptom intensity, symptom-free duration, dependence on episodic medication, associated health changes and correctly selected investigations should be assessed together.
Ayurvedic Assessment of Recurrence
Ayurvedic assessment examines the complete pattern surrounding recurrence rather than using HSV-1 or HSV-2 typing as the sole basis for treatment. The evaluation may include the dominant symptoms, digestion, bowel function, sleep, emotional strain, menstrual associations, skin sensitivity, urinary symptoms and the time required for tissue healing.
For example, one patient may experience pronounced burning, redness and moist erosions, while another develops dryness, fissuring and nerve-like pain. These differences do not determine the viral type, but they can influence the individualized Ayurvedic treatment strategy.
The interval between episodes is also clinically important. A gradual reduction in outbreak frequency, shorter symptom duration and longer stable periods may indicate meaningful improvement. Repeated mild symptoms, digestive disturbance or continuing mucosal sensitivity may show that further assessment is required even when large blisters no longer occur.
Long-term recovery should therefore be evaluated through sustained clinical stability rather than one symptom-free week or the temporary disappearance of a lesion. The recurrence pattern, asymptomatic periods, associated health findings and appropriately interpreted laboratory investigations together provide a more complete basis for assessing progress.
HSV-1 vs HSV-2 Testing
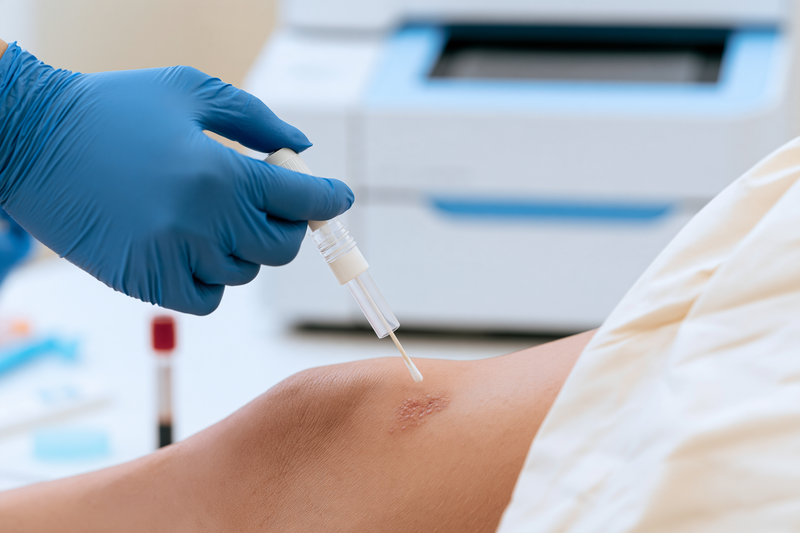
HSV-1 vs HSV-2 testing should identify the viral type, clarify whether a current lesion contains HSV and establish a reliable baseline for future clinical assessment. The correct test depends on whether a fresh lesion is present, how recently exposure may have occurred, whether the patient has symptoms and what previous laboratory results are available. A blood antibody test and a lesion PCR answer different clinical questions and should not be treated as interchangeable [1,6].
Testing a Fresh Blister or Ulcer
When a fresh blister, erosion, fissure or ulcer is present, a sample taken directly from the lesion for a type-specific nucleic acid amplification test, commonly reported as PCR, provides the most useful diagnostic evidence. It can detect HSV genetic material and usually distinguish HSV-1 from HSV-2 [1,6].
The sample should preferably be collected from a newly developed lesion before crusting or substantial healing has occurred. Viral detection becomes less reliable as the lesion ages because the amount of virus available at the surface may decline. A negative result from a nearly healed ulcer therefore does not always exclude HSV [1,6].
For example, a patient who develops a fresh cluster of genital blisters on Monday is more likely to obtain a diagnostically useful result if the lesion is sampled promptly rather than after several days of drying, washing and topical treatment. Early sampling also reduces the risk of losing the opportunity to identify the viral type.
Small fissures can also be sampled when they are fresh and clinically suspicious. A patient does not need to wait for a large blister if recurrent symptoms repeatedly appear as a painful crack, raw area or localized erosion. The clinician should sample the base of the active lesion using an appropriate collection technique [6].
A positive type-specific lesion PCR confirms that HSV was present in the sampled lesion. It also establishes whether the outbreak was caused by HSV-1 or HSV-2, which helps predict the usual recurrence and shedding pattern more accurately than symptoms alone [1].
A negative lesion PCR must be interpreted according to the lesion’s age, sample quality and clinical appearance. It may mean that HSV was not present, but it may also occur when the lesion was already healing, viral shedding had stopped or an inadequate specimen was collected. Repeatedly negative tests from correctly sampled fresh lesions make alternative diagnoses more important to investigate [1,6].
Viral culture may still be used in some settings, but its sensitivity is generally lower than NAAT/PCR, particularly for recurrent or healing lesions. A negative culture from an old lesion should therefore not be given the same weight as a properly collected negative molecular test from a fresh lesion [1,6].
Type-Specific HSV IgG
Type-specific HSV IgG blood testing looks for antibodies formed after exposure to HSV-1 or HSV-2. It may be useful when lesions are absent, when a previous clinical diagnosis was never laboratory-confirmed or when recurrent genital symptoms continue despite negative lesion testing [1].
A positive HSV-1 IgG result indicates previous exposure to HSV-1, but it usually cannot determine whether the infection is oral or genital. It cannot establish when the infection occurred, who transmitted it or whether current genital symptoms are caused by HSV-1 [1].
For example, a patient with a positive HSV-1 IgG result and new genital burning may have an oral HSV-1 infection acquired during childhood and an unrelated genital condition. Without a positive sample from a genital lesion, the antibody result alone cannot confirm genital HSV-1.
A positive HSV-2 IgG result is more strongly associated with anogenital infection because HSV-2 is predominantly sexually acquired. However, the result still cannot determine the date of infection or identify the transmitting partner. A person may first recognize symptoms years after the original exposure [1,6].
Antibodies require time to develop after a newly acquired infection. Testing too early may produce a negative result even when infection has occurred. When recent exposure is suspected, repeat type-specific testing may be required after an appropriate interval [1].
The laboratory report should include the test method, numerical index value, reference range and whether confirmatory testing was performed. A report that states only “positive” or “reactive” without the index value may not provide enough information for accurate interpretation.
Low-Positive HSV-2 Results
Some commercial HSV-2 IgG assays can produce false-reactive results, particularly when the reported index value is only slightly above the laboratory cutoff. A low-positive result should not automatically be treated as definitive evidence of infection without considering the numerical value, clinical history and need for confirmation [1,8].
For example, an HSV-2 IgG index value just above the positive threshold may require confirmation using a different validated method. A strongly positive result in a patient with a previously confirmed HSV-2 lesion carries a different level of evidence from a borderline result in a person who has never had symptoms.
Confirmatory testing may include a validated inhibition assay, a different type-specific test, Biokit or Western blot where available. The available method depends on the country, laboratory and clinical setting [1,8].
A low-positive result can create substantial emotional distress, relationship conflict and fear of transmission. Confirming the diagnosis before making long-term decisions is therefore clinically important. The result should not be used to accuse a current partner of recent transmission because serology cannot determine when infection occurred.
When an initial low-positive HSV-2 result is followed by a negative confirmatory test, the complete laboratory pattern should be reviewed rather than choosing the most alarming result. Test performance, timing, assay differences and the presence or absence of compatible symptoms all contribute to the final interpretation [1,8].
Conflicting IgG Results
HSV IgG values may differ between laboratories because assays, antigens, calibration systems and reporting ranges are not identical. A change in the numerical value does not always indicate a proportional biological increase or decrease in viral activity.
For example, an HSV-1 IgG value reported as 28 by one laboratory cannot be directly compared with a value of 4.2 from another laboratory unless the same assay system, units and reference range were used. Both values may simply represent a positive antibody result measured by different platforms.
When serial testing is used to assess long-term change, the original laboratory report should be retained. The patient should record the assay name, index value, units and reference range rather than relying only on the words positive or negative.
If a previously positive result later becomes negative or falls below the laboratory cutoff, the finding should be confirmed and interpreted together with the original test strength, confirmatory results, clinical history and laboratory method. A single unexpected result should not be accepted or rejected without reviewing the complete testing sequence.
Serial findings become more clinically meaningful when they are supported by sustained symptom resolution, longer recurrence-free intervals, improved associated health findings and consistency across appropriately selected laboratory investigations. One isolated blood result should not replace a complete long-term assessment.

Why HSV IgM Is Not Recommended
HSV IgM is not recommended for diagnosing recent HSV-1 or HSV-2 infection because it is not reliably type-specific. It may cross-react between HSV types and can become detectable during recurrent episodes as well as during an initial infection [1].
A positive IgM result therefore cannot reliably prove that an infection was acquired recently. It also cannot accurately distinguish HSV-1 from HSV-2 or identify the anatomical site.
For example, a patient with longstanding oral HSV-1 may receive a positive combined HSV IgM result during a period of immune activation. The result should not automatically be interpreted as newly acquired genital HSV-2.
Patients are sometimes given an IgM result without an index value or without type-specific confirmation and are told that the infection is recent. This interpretation can be misleading. Type-specific IgG and direct testing of a fresh lesion provide more clinically useful information [1].
Blood HSV DNA PCR
HSV DNA PCR performed on blood is different from PCR performed on a lesion. Blood PCR is mainly used when disseminated, neonatal, visceral or other severe systemic HSV infection is suspected. It is not the routine diagnostic test for an uncomplicated localized oral or genital outbreak [1].
A person with localized genital HSV may have a negative blood PCR because the infection is not circulating in the bloodstream at the time of testing. A negative blood result should therefore not be treated as equivalent to a negative sample taken from an active genital lesion.
For example, a patient with a fresh genital ulcer may have HSV detected from the lesion while the blood PCR remains negative. These results are not contradictory because the two specimens assess different biological compartments.
Blood PCR becomes more relevant when a patient has severe systemic illness, hepatitis, neonatal infection, widespread disease or significant immune suppression. The decision to order it should be based on the clinical presentation rather than using it as a universal screening test [1].
Cerebrospinal fluid PCR is used when HSV infection of the central nervous system is suspected. Eye disease requires ophthalmic assessment and appropriately selected ocular testing. The specimen must always match the organ or tissue being investigated.
Interpreting a Negative Result
A negative test does not have the same meaning in every situation. A negative lesion PCR from a well-sampled fresh ulcer is more informative than a negative culture from a healed lesion. A negative IgG result obtained soon after exposure is less reliable than one obtained after sufficient time for antibodies to develop [1,6].
A patient with recurrent genital symptoms and repeatedly negative fresh-lesion testing should be evaluated for other causes. Candidiasis, bacterial infection, contact dermatitis, lichen sclerosus, vulvodynia, friction injury, pelvic-floor dysfunction, urinary disease and neuropathic pain may produce overlapping symptoms [6].
A negative result should not lead to repeated empirical treatment when the symptom pattern and laboratory findings do not support HSV. At the same time, one poorly timed negative test should not be used to dismiss a strongly suggestive recurrent lesion without further assessment.
When no lesion is available, photographs taken at the beginning of an episode may help document the pattern, but images cannot replace virological confirmation. The patient should seek testing as early as possible during the next fresh episode.
Testing People Without Symptoms
Routine population screening for genital HSV using blood tests is not recommended for every asymptomatic adult because false-positive results, unclear infection sites and limited clinical benefit can create unnecessary harm [7].
Testing may be considered when a patient has recurrent or atypical genital symptoms, a partner with genital herpes, a previous unconfirmed diagnosis or specific pregnancy-related concerns. The expected value of testing should be discussed before the sample is collected [1,7].
An asymptomatic person with a positive HSV-1 IgG result should not automatically be labelled as having genital herpes. The result more commonly reflects oral infection, although the anatomical site cannot be established through serology alone.
An asymptomatic person with a confirmed HSV-2 IgG result should receive counselling about possible anogenital infection, asymptomatic shedding, partner communication and recognition of subtle symptoms. The result should still be reviewed carefully when the initial index value was low [1,8].
Establishing a Long-Term Baseline
Long-term assessment begins with accurate baseline documentation. The patient’s initial lesion test, HSV type, IgG values, assay details, outbreak frequency, symptom duration, anatomical location, associated symptoms and previous treatment should be recorded before interpreting later changes.
For example, a patient who initially experienced six genital outbreaks per year, persistent burning and repeated positive lesion tests has a different baseline from a patient with one remote positive IgG result and no confirmed lesion. The same follow-up criteria should not be applied to both without considering these differences.
Clinical improvement may include fewer outbreaks, shorter episodes, reduced pain, longer symptom-free intervals, improved mucosal healing and reduced dependence on episodic medication. Laboratory changes should be interpreted alongside these clinical findings rather than in isolation.
A permanent recovery assessment requires sustained clinical stability and serial laboratory evaluation selected according to the patient’s original diagnostic evidence. The interpretation should consider whether the same validated assay was used, whether unexpected results were confirmed and whether viral DNA testing was performed on an appropriate specimen.
Ayurvedic assessment adds the patient’s Prakriti, current imbalance, Agni, bowel function, sleep, stress response, tissue healing and associated health conditions to this baseline. These factors guide individualized treatment while laboratory testing documents the viral and immunological findings relevant to long-term follow-up.
The most reliable assessment therefore combines accurate initial diagnosis, correctly timed repeat testing, sustained absence of clinical recurrence, restoration of associated health parameters and consistent serial findings rather than depending on one symptom, one antibody value or one isolated PCR result.
HSV-1 vs HSV-2 in Pregnancy

HSV-1 vs HSV-2 in pregnancy requires careful assessment because either viral type can cause genital infection and, in uncommon cases, may be transmitted to the baby during birth. The risk is influenced less by the viral label alone and more by whether the genital infection is newly acquired or recurrent, when it occurred during pregnancy, whether lesions or prodromal symptoms are present near delivery and whether maternal antibodies have had time to develop [1,9].
A woman with longstanding recurrent genital herpes usually has a substantially lower neonatal transmission risk than a woman who acquires genital HSV for the first time during late pregnancy. Previous infection allows the mother to develop type-specific antibodies that can cross the placenta and provide partial protection to the baby. When genital infection is acquired close to delivery, there may be insufficient time for this protective antibody response to develop [1,9].
HSV-1, HSV-2 and Fertility
HSV-1 and HSV-2 are not generally considered direct causes of infertility in most women or men. A positive HSV IgG result alone does not explain difficulty conceiving, repeated implantation failure, reduced ovarian reserve, blocked fallopian tubes or abnormal semen parameters.
For example, a woman with positive HSV-1 IgG and irregular ovulation may have acquired oral HSV-1 during childhood, while her fertility difficulty may be related to polycystic ovary syndrome, thyroid dysfunction, hyperprolactinaemia, endometriosis or another reproductive condition. The antibody result should not be assumed to be the cause without appropriate evaluation.
Similarly, a man with HSV-2 and reduced sperm concentration requires a complete fertility assessment. Hormonal imbalance, varicocele, infection, medication effects, metabolic disease, heat exposure and lifestyle factors may contribute independently of HSV.
Active genital lesions can temporarily interfere with sexual activity because of pain, burning, fear of transmission or discomfort during intercourse. Recurrent outbreaks may also affect emotional wellbeing and relationship intimacy. These indirect effects can reduce the frequency of intercourse during the fertile window, but they are different from proven biological infertility.
Persistent pelvic pain, vaginal discharge, urethral symptoms or recurrent genital inflammation should not automatically be attributed to herpes. Chlamydia, gonorrhoea, pelvic inflammatory disease, endometriosis, candidiasis, bacterial vaginosis, prostatitis and other conditions can coexist with HSV and may have a more direct effect on reproductive health.
Preconception evaluation should therefore include accurate HSV typing, recurrence history, partner status, obstetric history, other sexually transmitted infection screening and assessment of the usual causes of infertility when conception has not occurred within the expected period.
New Infection During Pregnancy
A first genital HSV infection during pregnancy requires prompt medical assessment. The clinical team must determine whether the episode represents a true primary infection, a first recognized episode of a previously acquired infection or a recurrence.
A primary infection occurs when a woman acquires HSV-1 or HSV-2 without having pre-existing antibodies to either type. A non-primary first episode occurs when she acquires one HSV type while already having antibodies to the other. A first recognized episode may also represent an older infection that had previously produced no noticeable symptoms.
These distinctions matter because the immune response and neonatal risk differ. A woman who develops her first recognized genital lesion during pregnancy may not necessarily have been infected recently. Lesion PCR, type-specific IgG, previous reports, symptom history and the timing of antibody development should be interpreted together [1,9].
New genital infection during the first or second trimester can still require antiviral treatment and obstetric follow-up, but there is generally more time for maternal antibodies to develop before delivery. Infection acquired during the third trimester, particularly close to labour, creates greater concern because viral shedding may persist and protective antibodies may be incomplete [1,9].
For example, a woman who develops painful genital ulcers at 37 weeks and has a positive lesion PCR with initially negative type-specific IgG may have a recently acquired infection. Her situation is different from that of a woman with a ten-year history of genital HSV-2 who has no lesions or prodromal symptoms near delivery.
A pregnant woman should not rely on the absence of blisters to exclude infection. A first episode may appear as a small fissure, vulval burning, painful urination, vaginal discomfort or localized tenderness. Fresh lesions should be tested promptly because delayed sampling may reduce diagnostic sensitivity.
Recurrent Herpes During Pregnancy
Women with established recurrent genital HSV usually experience a lower risk of neonatal transmission than women with newly acquired late-pregnancy infection. Maternal antibodies, shorter viral shedding episodes and partial immune control contribute to this difference [1,9].
Recurrences during pregnancy may still cause pain, anxiety and concern about delivery. The number of outbreaks may increase, decrease or remain unchanged. Hormonal changes, sleep disruption, emotional strain, local friction and other individual factors may influence recurrence patterns.
A recurrent lesion should be documented according to its location, duration and severity. When the diagnosis has never been laboratory-confirmed, type-specific lesion testing can establish whether HSV-1 or HSV-2 is present.
Genital HSV-2 generally carries a greater recurrence and shedding burden than genital HSV-1. However, either type can be shed at delivery, and the obstetric decision should be based on the woman’s current symptoms, examination findings, infection history and timing rather than assuming that HSV-1 is always low risk [1,9].
Suppressive antiviral therapy is commonly considered during the final weeks of pregnancy for women with recurrent genital herpes. Its purpose is to reduce clinical recurrences and viral shedding near delivery and decrease the likelihood that active disease will necessitate caesarean delivery. It does not replace examination and obstetric assessment at the onset of labour [1,9].
Labour and Delivery
At the onset of labour, the obstetric team should ask about genital pain, burning, tingling or other prodromal sensations and examine for active lesions. Prodromal symptoms may indicate reactivation before a blister becomes visible.
Women with no genital lesions or prodromal symptoms at labour may often proceed with vaginal delivery under obstetric guidance. A history of recurrent herpes alone does not automatically require caesarean delivery [1,9].
Caesarean delivery is generally recommended when active genital herpetic lesions or compatible prodromal symptoms are present at the onset of labour because it reduces the baby’s exposure to infected genital secretions and skin. It does not eliminate neonatal transmission risk completely, particularly if the membranes have been ruptured for a prolonged period [1,9].
A first genital episode during the third trimester requires individualized delivery planning. Caesarean delivery may be offered because viral shedding can be prolonged and maternal antibody protection may be incomplete [9].
Invasive procedures that can disrupt the baby’s skin, such as fetal scalp electrodes, should be avoided when active maternal genital HSV is suspected unless their clinical benefit clearly outweighs the risk. Prolonged rupture of membranes may increase the duration of fetal exposure to genital secretions.
For example, a woman with recurrent HSV-2 who has no lesions or prodrome when labour begins may be managed differently from a woman with a painful genital ulcer and burning that started the previous day. The viral history is important, but the condition at delivery directly influences immediate management.
Neonatal Herpes
Neonatal herpes is uncommon but potentially severe. Infection may involve the skin, eyes and mouth, the central nervous system or multiple internal organs. Early symptoms can be subtle and may resemble bacterial sepsis or other newborn illnesses [1].
A newborn may develop clusters of vesicles, eye redness, poor feeding, unusual sleepiness, irritability, fever, low temperature, breathing difficulty, jaundice, seizures or reduced responsiveness. Some affected newborns do not initially develop visible skin lesions.
Any newborn with possible exposure during delivery and compatible symptoms requires urgent paediatric assessment. Early antiviral treatment is important because neonatal HSV can progress rapidly.
The risk to the baby is highest when the mother acquires genital HSV near delivery. The risk is much lower in women with established recurrent infection, but it is not zero. Obstetric and neonatal teams should therefore receive a complete history of maternal HSV type, timing, symptoms, treatment and findings at labour [1,9].
Family members with active cold sores should avoid kissing the newborn. They should wash their hands before handling the baby and keep oral lesions covered where practical. This precaution is important because neonatal infection can also be acquired after birth through direct contact with oral HSV-1.
Breastfeeding With HSV
Breastfeeding is generally possible when the mother has oral or genital herpes, provided there are no active lesions on the breast and lesions elsewhere are completely covered [1].
An active herpetic lesion on the nipple, areola or breast creates a risk of direct viral exposure. The baby should not feed from the affected breast until the lesion has fully healed and medical guidance confirms that feeding can resume.
Expressed milk from the affected breast may also require temporary avoidance if the pumping equipment or milk could have contacted the lesion. Milk from an unaffected breast may usually be given when careful hygiene is maintained.
A mother with a cold sore should avoid kissing the baby, wash her hands before feeding and avoid touching the lesion during infant care. A clean covering may be used over the lesion when practical.
Genital lesions do not require breastfeeding to stop when they are covered and the mother follows careful hand hygiene. The treatment plan should also consider the safety of any oral, topical or Ayurvedic medicines used during lactation.
Ayurvedic Care Before and During Pregnancy
Ayurvedic management before conception can evaluate recurrence frequency, digestion, bowel function, sleep, menstrual health, stress response, associated conditions and the time required for complete lesion healing. The objective is to establish the most stable possible maternal health before pregnancy begins.
Panchakarma should not be started during pregnancy unless a qualified Ayurvedic obstetric practitioner determines that a specific mild procedure is appropriate. Strong purification, emesis, purgation, intensive enemas and unverified herbo-mineral combinations may be unsuitable during pregnancy.
Rasayana treatment, herbal medicines and Rasaushadhi require individual review before conception, during pregnancy and while breastfeeding. A formulation used safely in a non-pregnant adult cannot automatically be continued after conception because ingredients, dose, processing method and gestational stage affect safety.
Garbhini Paricharya refers to individualized Ayurvedic care of the pregnant woman. In a patient with HSV, it should support nutrition, digestion, bowel regularity, sleep, emotional stability and maternal tissue health without replacing lesion testing, antiviral treatment or obstetric precautions.
For example, a woman preparing for pregnancy after recurrent genital outbreaks may require several months of preconception assessment to document symptom stability, improve associated digestive or metabolic disturbances and review all medicines. Once pregnancy is confirmed, the treatment plan should be reassessed rather than continued unchanged.
The permanent recovery assessment should consider sustained absence of outbreaks, longer symptom-free intervals, stable mucosal health, associated clinical improvement and serial laboratory findings interpreted according to the original diagnostic evidence. During pregnancy, these long-term criteria must remain integrated with obstetric monitoring because the safety of the mother and baby takes priority at every stage.
HSV-1 vs HSV-2 Complications
HSV-1 vs HSV-2 complications can extend beyond recurrent cold sores or genital blisters. Although many infections remain mild or unrecognized, either viral type can occasionally affect the eyes, nervous system, urinary function, anorectal tissues, damaged skin or internal organs. The likelihood and severity depend on the infected site, immune status, age, pregnancy status, extent of the first episode and the speed with which treatment is started [1,2,6].
HSV-1 is more strongly associated with ocular herpes and herpes simplex encephalitis, while genital HSV-2 is more frequently associated with recurrent genital disease, aseptic meningitis, sacral nerve involvement and urinary retention. These patterns are not absolute because both types can produce severe disease when the clinical circumstances permit [1,2].
Eye Complications
HSV keratitis occurs when herpes affects the cornea, the transparent front surface of the eye. It is most often associated with HSV-1 and may develop through reactivation of a previous infection. Repeated inflammation can damage the cornea, produce scarring and reduce vision if the condition is not treated promptly [2].
Symptoms may include eye pain, redness, excessive tearing, blurred vision, sensitivity to light or the sensation that something is trapped in the eye. The symptoms usually affect one eye, although bilateral disease can occur, particularly in patients with immune suppression.
For example, a patient with a history of recurrent cold sores who develops one-sided eye redness, light sensitivity and blurred vision should not assume that the symptoms are ordinary conjunctivitis. Immediate ophthalmic examination is required because inappropriate treatment, particularly unsupervised corticosteroid eye drops, can worsen certain forms of herpetic corneal disease.
Herpes may affect different layers of the cornea. Superficial epithelial disease can produce characteristic branching corneal lesions, while deeper stromal inflammation can cause more significant scarring, swelling and visual impairment. Repeated episodes can progressively affect corneal clarity even when each individual episode appears to settle.
The presence of an active cold sore does not mean that every episode of eye redness is caused by HSV. Bacterial conjunctivitis, allergic inflammation, corneal abrasion, contact-lens injury, uveitis and other eye diseases can produce overlapping symptoms. Direct examination by an eye specialist is necessary because the treatment differs according to the affected ocular structure.
Patients with active oral or genital lesions should wash their hands after touching the affected area and avoid rubbing the eyes. Contact lenses should be removed when eye pain, redness or visual disturbance develops, and they should not be restarted until an eye specialist confirms that it is safe.
Neurological Complications
HSV can affect the meninges, brain or sensory and autonomic nerves. Neurological complications are uncommon compared with ordinary oral or genital outbreaks, but they require rapid recognition because delayed treatment can lead to prolonged illness or permanent disability [1,2].
HSV-2 meningitis may occur during a first genital episode or, less commonly, as a recurrent neurological condition. Symptoms can include severe headache, fever, neck stiffness, light sensitivity, nausea and pain when attempting to bend the neck. Genital lesions may be present, subtle or absent when neurological symptoms begin [1].
For example, a patient who develops genital ulcers followed by a severe headache, fever and marked light sensitivity should not manage the episode as a routine recurrence at home. Cerebrospinal fluid testing and hospital-based antiviral treatment may be required.
HSV encephalitis involves inflammation of brain tissue and is most commonly associated with HSV-1 in adults. It may cause confusion, personality or behavioural change, memory disturbance, speech difficulty, seizures, weakness or reduced consciousness. Fever and headache may occur before neurological changes become obvious [2].
A patient who appears unusually confused, cannot recognize familiar people, develops a new seizure or has difficulty speaking requires emergency evaluation. The absence of a visible cold sore does not exclude HSV encephalitis because neurological reactivation may occur without an active oral lesion.
Sacral nerve involvement may accompany genital herpes. Inflammation affecting the sensory and autonomic nerves can cause severe pain radiating through the buttocks or legs, altered genital sensation, constipation, difficulty initiating urination or an inability to empty the bladder [6].
Urinary retention can occur even when the visible genital lesions are limited. A patient may feel bladder fullness and urgency but be unable to pass urine because the nerves controlling bladder function are temporarily impaired. Hospital assessment and temporary catheterisation may be required until normal function returns [6].
Localized tingling or brief nerve discomfort during a recurrence does not necessarily indicate meningitis or encephalitis. Concern increases when neurological symptoms are severe, progressive, associated with fever or accompanied by bladder dysfunction, weakness, confusion or altered consciousness.
Genital and Anorectal Complications
A severe first genital episode can produce extensive ulceration, swelling, pain and difficulty walking, sitting or urinating. Lesions may merge into larger raw areas, particularly when treatment is delayed or immune function is impaired [1,6].
Painful urination may occur because urine contacts inflamed external tissue rather than because the bladder itself is infected. Some patients reduce their fluid intake to avoid urination, which can lead to dehydration and more concentrated urine that causes greater burning.
For example, a woman with extensive vulval ulcers may be able to pass urine more comfortably while pouring clean lukewarm water over the external area. However, an inability to pass urine, increasing lower abdominal pressure or reduced urinary output requires immediate assessment rather than home management.
HSV proctitis can affect the rectum and anal canal, particularly after receptive anal exposure. Symptoms may include anorectal pain, tenesmus, constipation, mucus discharge, bleeding, painful bowel movements and ulceration around or inside the anus [1,6].
Internal rectal lesions may not be visible during an external examination. A patient with severe rectal pain, discharge and systemic symptoms may require specialist assessment because HSV proctitis can resemble inflammatory bowel disease, bacterial proctitis, anal fissure, haemorrhoids or other sexually transmitted infections.
Secondary bacterial or fungal infection of herpetic lesions is uncommon but may occur, particularly when lesions remain open, moist or repeatedly irritated. Increasing redness, swelling, purulent discharge, unpleasant odour, worsening pain or renewed fever after initial improvement may suggest superinfection [6].
Not every persistent ulcer is caused by uncontrolled HSV. Syphilis, chancroid, inflammatory dermatoses, fixed drug eruption, Behçet disease, trauma and neoplastic conditions can produce genital ulceration. A lesion that persists, enlarges, bleeds unusually or repeatedly tests negative for HSV requires broader investigation.
Skin Complications
HSV can spread extensively through skin affected by eczema or another condition that has disrupted the protective barrier. Eczema herpeticum may produce numerous painful, similarly shaped erosions or blisters accompanied by fever, fatigue and rapidly worsening skin inflammation [2,6].
This complication can involve the face, neck, trunk or other areas of damaged skin. Eye involvement is an additional concern when lesions develop close to the eyelids. Prompt systemic antiviral treatment is required because the infection can progress beyond a localized cold sore.
For example, a patient with atopic dermatitis who develops dozens of painful punched-out erosions and fever should not treat the eruption only as an eczema flare. Rapid clinical assessment is required to distinguish eczema herpeticum from bacterial infection or severe dermatitis.
Herpetic whitlow occurs when HSV infects a finger, producing pain, swelling and grouped vesicles. It may follow direct contact with oral or genital lesions, particularly when the skin around the nail is broken. Incision and drainage should not be performed as though the lesion were an ordinary bacterial abscess unless the diagnosis has been properly established.
Autoinoculation to a new body site is more likely during a newly acquired infection, before an established immune response develops, or when the skin barrier is severely impaired. Repeated transfer to multiple body sites is not the usual pattern in an immunocompetent patient with established infection [6].
Recurrent erythema multiforme may be associated with HSV, particularly recurrent oral HSV-1. It usually appears as symmetrical target-like skin lesions and may recur after herpes episodes. Extensive mucosal involvement, widespread blistering or systemic illness requires urgent assessment to exclude more serious dermatological conditions.
HSV-2 and HIV Risk
HSV-2 infection is associated with an approximately twofold to threefold increased risk of acquiring HIV. Genital ulcers can disrupt the protective mucosal barrier, while HSV-related inflammation can recruit immune cells that are susceptible to HIV infection [1,2].
The increased risk is not limited to days when visible ulcers are present. Persistent microscopic inflammation may remain at genital sites affected by HSV-2, which contributes to the biological association between the two infections.
A person diagnosed with genital herpes should therefore be offered appropriate HIV testing according to clinical guidelines and exposure history. Other sexually transmitted infections should also be considered because syphilis, chlamydia, gonorrhoea and hepatitis infections can coexist without producing obvious symptoms.
In a person living with HIV, untreated or advanced immune deficiency can make HSV outbreaks more prolonged, extensive, painful or resistant to standard treatment. Lesions may become chronic, merge into larger ulcerated areas or involve multiple anatomical sites [1,6].
Effective HIV treatment improves immune function and generally reduces the risk of severe or persistent HSV disease. A chronic genital ulcer in an immunocompromised patient requires virological confirmation, assessment for antiviral resistance and exclusion of other infectious or malignant causes.
Complications During Immune Suppression
Patients receiving chemotherapy, organ-transplant medicines, biological therapies, prolonged corticosteroids or other immunosuppressive treatment may experience more extensive HSV reactivation. The infection can involve large mucocutaneous areas or, in severe cases, spread to internal organs [1,2,6].
Disseminated HSV may affect the liver, lungs, oesophagus, central nervous system or multiple organ systems. Symptoms depend on the organs involved and may include persistent fever, severe weakness, difficulty swallowing, chest symptoms, abdominal pain, jaundice, confusion or rapidly progressive skin lesions.
For example, a patient receiving chemotherapy who develops painful swallowing and oral ulcers may require evaluation for herpetic oesophagitis rather than assuming that every lesion is routine treatment-related mucositis.
HSV hepatitis is uncommon but potentially life-threatening. It may cause fever, abdominal discomfort and rapidly rising liver enzymes, sometimes without prominent skin lesions. Blood HSV PCR becomes clinically relevant when disseminated infection or HSV hepatitis is suspected, unlike routine localized genital infection [1].
Antiviral resistance remains uncommon in immunocompetent patients but is more likely in people with substantial immune suppression who have received prolonged or repeated antiviral treatment. Persistent lesions that continue to enlarge despite correctly dosed therapy require specialist investigation and susceptibility testing where available [6].
When Urgent Care Is Required
Eye pain, blurred vision, marked light sensitivity or one-sided eye redness requires urgent ophthalmic assessment. Delay can increase the risk of corneal damage and visual impairment.
Severe headache, fever, neck stiffness, confusion, personality change, difficulty speaking, weakness, seizures or reduced consciousness requires emergency neurological evaluation. These symptoms should not be observed at home while waiting for a routine appointment.
Inability to pass urine, increasing bladder pressure, leg weakness, altered genital sensation or severe sacral pain requires prompt assessment for autonomic or sacral nerve involvement.
Rapidly spreading lesions, extensive painful erosions, high fever, severe weakness, jaundice, breathing difficulty or difficulty swallowing requires urgent evaluation, particularly in an immunocompromised patient.
A newborn with blisters, poor feeding, unusual sleepiness, fever, low temperature, breathing difficulty, irritability or seizures requires immediate paediatric assessment. Neonatal HSV can progress rapidly and may initially occur without obvious skin lesions [1,2].
Ayurvedic Assessment of Complicated HSV
Complicated HSV requires the immediate management of the affected organ or system together with an individualized Ayurvedic assessment after the patient is clinically stable. Eye involvement, encephalitis, meningitis, urinary retention, neonatal infection and disseminated disease require urgent specialist care and cannot be assessed through the skin manifestation alone.
The Ayurvedic evaluation considers the intensity of Daha, pain, inflammation, ulceration, nerve involvement, tissue healing, bowel and urinary function, sleep, Agni and the patient’s overall strength. The affected Dhatu and Srotas are assessed according to the full clinical presentation rather than assuming that every HSV complication represents the same Dosha pattern.
For example, a patient with recurrent burning erosions, heat and inflammatory discharge presents differently from a patient with fissuring, dryness, sacral pain and urinary difficulty. These variations influence the selection and sequence of treatment after the acute complication has been stabilized.
Rasayana planning requires consideration of the patient’s immune status, liver and kidney function, concurrent antiviral medicines, chemotherapy or immunosuppressive treatment. Herbo-mineral medicines should not be prescribed from a standard list without evaluating pharmaceutical quality, dose, interactions and the patient’s capacity to tolerate treatment.
Visible healing of a complication is one stage of recovery. Continued assessment includes neurological or ocular function, recurrence pattern, tissue repair, symptom-free duration, associated health parameters and appropriately selected serial laboratory findings.
Can They Be Cured Permanently?
HSV-1 vs HSV-2 typing helps predict recurrence, shedding and transmission patterns, but the viral label alone does not determine whether permanent recovery has occurred. Yes, the treatment objective can extend beyond temporary control of blisters, burning and itching. A curative-intent approach must evaluate whether clinical stability continues, associated health disturbances improve and serial laboratory findings remain consistent after the active treatment phase.
Modern English Medicine antiviral drugs reduce viral replication during active episodes and suppress recurrent outbreaks while they are being taken. They can shorten lesion duration, reduce pain, decrease shedding and lower transmission risk, but they do not directly remove latent viral material from sensory nerve pathways [1]. This is why some patients experience another outbreak after episodic treatment ends or after suppressive medication is discontinued.
The absence of a blister is therefore an important improvement, but it is not the only criterion used to assess permanent recovery. A patient may have no large visible lesion while continuing to experience recurrent fissures, genital burning, urinary discomfort, localized nerve sensitivity or dependence on daily suppressive medication. These findings indicate that the clinical pattern has changed, but further evaluation remains necessary.
Why Viral Type Is Only One Part of Recovery
Genital HSV-2 generally recurs and sheds more frequently than genital HSV-1, while genital HSV-1 activity often declines substantially during the first year [1,4,5]. These differences influence the expected course of treatment, but they do not determine the final outcome for every patient.
For example, a patient with genital HSV-1 may have one severe first episode followed by prolonged stability, while another may continue to experience occasional fissures or burning. A patient with HSV-2 may initially experience frequent outbreaks and later develop progressively longer symptom-free intervals. The viral type helps establish the expected pattern, but the individual response must be measured over time.
The anatomical site also matters. Oral HSV-1, genital HSV-1 and genital HSV-2 differ in their usual recurrence and shedding behaviour. A positive HSV-1 IgG result without lesion confirmation does not establish whether the infection is oral or genital. Long-term evaluation must therefore begin with an accurate baseline that includes the viral type, site, specimen used for diagnosis, outbreak frequency and the patient’s complete symptom history [1,6].
The treatment history is equally important. A patient who remains symptom-free only while taking daily suppressive antivirals has achieved effective suppression. A patient who remains clinically stable after treatment has been reduced or withdrawn under medical supervision demonstrates a different level of recovery. Medication changes should be supervised because sudden discontinuation may be inappropriate during pregnancy, immune suppression or frequent recurrent disease.
Associated health factors can influence the recurrence pattern and the patient’s ability to heal. Poorly controlled diabetes, chronic sleep loss, severe constipation, recurrent candidiasis, nutritional deficiency, immune suppression and persistent mucosal inflammation may coexist with HSV. Correcting these conditions does not replace antiviral or Ayurvedic treatment, but it removes factors that may interfere with sustained recovery.
For example, a patient may report that blisters have stopped but genital burning continues. Further examination may identify candidiasis, contact dermatitis, pelvic-floor dysfunction or urinary disease. Treating the remaining condition prevents persistent symptoms from being incorrectly labelled as continuing HSV activity.
Clinical Criteria for Permanent Recovery
Permanent recovery requires sustained clinical stability rather than a short symptom-free interval after treatment. The assessment should document whether the number of outbreaks has progressively decreased, whether lesions have stopped recurring, whether prodromal burning or tingling has resolved and whether healed tissues remain stable.
The duration of each episode also matters. A reduction from ten painful days to two mild days represents improvement, but it is not the same as complete cessation of recurrence. The patient should record the location, intensity, duration and associated symptoms of each suspected episode so that gradual change can be measured accurately.
The symptom-free interval should lengthen progressively. A patient who previously experienced monthly outbreaks and later remains symptom-free for six months has achieved a clinically meaningful change. Continued observation is still required to establish whether that stability is durable.
Freedom from repeated medication is another relevant criterion. A patient who no longer requires frequent episodic treatment or daily suppression may have achieved a deeper level of stability than a patient whose symptoms return immediately whenever medicine is stopped. Any reduction in prescribed antiviral treatment should be undertaken with the treating clinician, especially in pregnancy or immune-compromised states.
Associated symptoms should improve alongside the visible lesions. Persistent genital sensitivity, urinary burning, rectal discomfort, nerve pain, sleep disturbance, bowel irregularity or recurrent mucosal inflammation may indicate that the patient’s broader clinical condition still requires attention.
Quality of life is also part of recovery. Fear of transmission, avoidance of intimacy, sleep disruption and anxiety before every minor skin sensation can continue even after outbreaks decrease. Accurate counselling, partner communication and objective follow-up findings help the patient distinguish true recurrence from unrelated irritation.
A single symptom-free week, one healed lesion or temporary improvement during suppressive treatment cannot establish permanent recovery. The clinical pattern must remain stable over an adequate follow-up period and should be supported by serial findings rather than one isolated observation.
Laboratory Criteria for Long-Term Assessment
Laboratory evaluation should begin with the original diagnostic evidence. The patient should retain the test name, specimen type, numerical index value, reference range, viral type and date of testing. Without this baseline, later results may be difficult to compare accurately.
Type-specific IgG may be followed when it formed part of the original diagnosis. Serial testing is most interpretable when the same validated assay, laboratory method and reference range are used. Values obtained from different platforms should not be compared as though they measure viral activity on an identical scale.
When a previously positive type-specific IgG result falls below the assay threshold, the result should be repeated and confirmed. A positive-to-negative change becomes more clinically meaningful when it is reproducible and occurs together with sustained absence of outbreaks, stable tissue healing and improvement in associated health findings.
For example, a single negative result from a different laboratory after a strongly positive baseline should not be interpreted without reviewing the assay method and index values. Repeated below-threshold findings using a validated method, combined with long-term clinical stability, provide a stronger recovery pattern than one isolated report.
DNA PCR must be interpreted according to the specimen tested. A lesion PCR detects viral DNA within the sampled lesion, while blood, cerebrospinal fluid or ocular testing is reserved for specific systemic, neurological or eye-related indications [1]. A negative blood PCR cannot independently prove the absence of localized latent oral or genital infection.
If a fresh lesion reappears during follow-up, type-specific lesion NAAT/PCR provides the most relevant opportunity to assess whether HSV is present in that episode. Repeatedly negative results from correctly sampled fresh lesions, together with sustained clinical stability and exclusion of alternative diagnoses, carry greater value than testing a healed lesion.
Where serial type-specific IgG changes from positive to below the assay threshold and appropriately selected DNA PCR findings remain undetectable, the findings should be interpreted together with the patient’s complete clinical course. Neither result should be separated from the original diagnosis, specimen type, treatment history and duration of follow-up.
A permanent-recovery assessment therefore requires consistency between the clinical and laboratory findings. Continuing outbreaks with one negative blood test do not demonstrate complete recovery. Conversely, sustained clinical stability supported by repeated, appropriately selected investigations provides a more comprehensive basis for long-term evaluation.
Ayurvedic Curative-Intent Approach
The Ayurvedic curative-intent model evaluates why the patient continues to experience recurrence rather than treating each visible lesion as an isolated event. The treatment sequence may include correction of digestive and bowel disturbance, management of associated disease, individualized Panchakarma where suitable and a sustained Rasayana phase.
Panchakarma may help prepare selected patients for deeper treatment by addressing bowel irregularity, metabolic burden and treatment tolerance. It is not used identically in every patient and should not be performed during pregnancy, severe weakness, dehydration or an acute medically unstable condition.
Rasayana remains central to the long-term phase because the objective is not limited to drying a blister. The treatment is directed toward stable tissue healing, neurological and mucosal recovery, improved physiological resilience and reduction of the tendency toward repeated clinical breakdown.
For example, two patients with confirmed HSV-2 may require different treatment plans. One may present with recurrent burning erosions, loose stools and inflammatory symptoms, while another has dry fissures, constipation, sacral pain and poor sleep. The viral type is the same, but the treatment sequence and formulation requirements differ.
The duration of treatment also varies. A recently acquired genital HSV-1 infection in an otherwise healthy patient cannot automatically be managed for the same duration as longstanding recurrent HSV-2 accompanied by diabetes, bowel disturbance, immune suppression or multiple associated infections.
The curative-intent model therefore evaluates the disappearance of outbreaks, extension of symptom-free intervals, restoration of associated health parameters, reduced dependence on repeated medication and serial laboratory findings. These criteria are assessed together rather than using one lesion, one antibody result or one PCR report as the sole measure of outcome.
For the complete discussion of viral latency, serial IgG and DNA PCR assessment, clinical evidence, treatment stages, Panchakarma, Rasayana and the criteria used to evaluate permanent recovery, read Can Herpes Be Cured Permanently? Real Cure Approach.
What to Do After a Positive Result

HSV-1 vs HSV-2 results should be reviewed according to the test method, specimen type, numerical value, symptoms and timing of possible exposure before treatment decisions are made. A positive result confirms different information depending on whether HSV was detected directly from a lesion or whether antibodies were found in blood. The first priority is therefore to establish exactly what the report proves and what it does not prove [1,6].
Confirm the Test and Viral Type
A positive type-specific NAAT/PCR result from a fresh oral or genital lesion confirms that HSV was present in the sampled lesion. The report should state whether HSV-1 or HSV-2 was detected because the type helps estimate the expected recurrence and shedding pattern [1,6].
A positive blood IgG result confirms previous exposure to the corresponding HSV type but does not prove that current symptoms are caused by herpes. HSV-1 IgG usually cannot determine whether the infection is oral or genital, while confirmed HSV-2 IgG generally indicates anogenital infection [1].
The complete report should be reviewed rather than relying only on the word “positive.” Important details include the assay name, HSV type, index value, laboratory reference range, specimen type and date of collection.
For example, a positive HSV-1 IgG result in a patient with no history of genital lesions may reflect oral infection acquired years earlier. It should not automatically be interpreted as genital herpes or as evidence of recent sexual transmission.
A positive lesion PCR and a positive antibody result also have different clinical significance. The lesion result identifies HSV in an active site, whereas IgG shows that the immune system has encountered the virus at some point.
Review Low-Positive HSV-2 Results
A low-positive HSV-2 IgG result may occasionally be falsely reactive. The numerical index value should therefore be reviewed, particularly when the patient has never had compatible symptoms and the result is only slightly above the assay cutoff [1,8].
Confirmation may be performed with a different validated type-specific method, an inhibition assay, Biokit or Western blot where available. The purpose is to avoid establishing a lifelong diagnosis from a borderline result that has not been independently verified [1,8].
For example, an HSV-2 index value just above the positive threshold in an asymptomatic patient should be interpreted differently from a strongly positive result supported by a previous HSV-2-positive genital lesion.
A borderline result should not be used to accuse a partner of recent transmission. Blood testing cannot identify when the infection occurred or who transmitted it.
If confirmation is negative or indeterminate, the clinician should review the original assay, timing, exposure history and any previous laboratory findings before reaching a final conclusion.
Test Fresh Lesions Promptly
A patient with a positive blood result and recurrent oral or genital symptoms should seek testing during the next fresh lesion whenever possible. A type-specific lesion NAAT/PCR can determine whether the episode is caused by HSV-1, HSV-2 or another condition [1,6].
Sampling is most useful when the lesion is new, moist or ulcerated. Waiting until it has crusted or nearly healed can reduce the amount of detectable virus and increase the chance of a negative result.
A small fissure, raw patch or superficial erosion may still be suitable for sampling. Patients do not need to wait for a large cluster of blisters when their episodes repeatedly appear in an atypical form.
For example, a woman who repeatedly develops a painful crack at the vaginal opening should arrange assessment as soon as the fissure appears. Testing several days later, after topical medicines and partial healing, may provide less reliable evidence.
Photographs taken at the beginning of an episode may help document the appearance and location, but they cannot replace laboratory confirmation.
Establish Whether the Infection Is Oral or Genital
The anatomical site influences counselling, recurrence expectations and transmission precautions. Oral HSV-1, genital HSV-1 and genital HSV-2 can behave differently even when the blood report appears similar.
A positive HSV-1 IgG result without a type-confirmed lesion does not establish the infection site. The patient’s history of cold sores, genital lesions, oral-genital exposure and previous swab results should be reviewed together.
Genital HSV-1 usually recurs and sheds less frequently than genital HSV-2, although transmission remains possible. Genital HSV-2 generally requires more detailed counselling about recurrent symptoms, asymptomatic shedding and partner protection [1,4].
An oral lesion should not automatically be labelled HSV-1, and a genital lesion should not automatically be labelled HSV-2. Direct lesion testing provides greater certainty than anatomical assumptions.
Assess Current Symptoms and Severity
The patient should document whether the positive result is associated with active blisters, ulcers, fissures, burning, itching, painful urination, rectal pain, nerve discomfort or systemic symptoms.
A first genital episode may require prompt systemic antiviral treatment because symptoms can worsen or continue for several weeks without appropriate management [1].
Recurrent mild symptoms may be managed differently from an extensive first episode. The treatment decision should consider lesion number, pain, urinary difficulty, fever, recurrence frequency, immune status and whether the patient can begin therapy early.
Persistent genital burning without a confirmed lesion requires broader assessment. Candidiasis, bacterial vaginosis, urinary infection, contact dermatitis, vulvodynia, pelvic-floor dysfunction, prostatitis and inflammatory skin disease may coexist with or imitate herpes [6].
For example, a patient may have confirmed HSV-2 but continue to experience daily burning between outbreaks because of contact dermatitis. Treating every episode of burning as viral recurrence may leave the actual cause untreated.
Screen for Other Relevant Infections
A confirmed genital HSV diagnosis should prompt appropriate assessment for other sexually transmitted infections according to the patient’s exposure history, symptoms and local clinical guidance.
HIV testing is particularly important because HSV-2 is associated with an increased risk of acquiring HIV, and immune deficiency can make HSV disease more frequent, extensive or prolonged [1].
Syphilis testing may be required because syphilitic ulcers can resemble herpes or coexist with it. Gonorrhoea and chlamydia testing may also be appropriate when there is urethral discomfort, pelvic pain, discharge, rectal symptoms or recent sexual exposure.
Hepatitis testing should be considered according to vaccination history, sexual exposure, blood exposure and regional recommendations.
Testing should be selected according to actual risk rather than ordering every available panel without clinical purpose.
Inform the Current Partner
Partner communication allows both people to understand transmission risk, recognize symptoms and make informed decisions about testing, barrier use and temporary avoidance of sexual contact.
The patient should explain that HSV can be transmitted during visible outbreaks, prodromal symptoms and asymptomatic shedding. The absence of lesions reduces an obvious sign of activity but does not guarantee that transmission is impossible [1].
The result should not be presented as proof of infidelity. A person may have acquired HSV months or years before the first recognized outbreak, and blood testing cannot establish the source or exact date of infection.
A partner with compatible symptoms should seek lesion testing promptly. An asymptomatic partner may discuss type-specific testing with a clinician after understanding the possible limitations and the risk of false-positive results [1,7,8].
For example, an asymptomatic partner of a person with confirmed genital HSV-2 may choose type-specific serology after counselling. A positive result may show that both partners already have the same HSV type, while a negative result may support additional transmission-reduction planning.
Reduce Transmission During Active Symptoms
Oral, genital and anal contact should be avoided when blisters, ulcers, fissures, tingling, burning or other prodromal symptoms are present.
Condoms reduce genital transmission risk but do not cover every area from which HSV may shed. They should be used consistently while recognizing that protection is not complete [1].
Barrier protection during oral sex can reduce oral-genital exposure. A person with an active cold sore should avoid kissing and oral sex until the lesion has fully healed.
Hands should be washed after touching or applying medicine to a lesion. The eyes should not be touched after contact with an oral or genital lesion.
Personal items that directly contact an active oral lesion, such as lip products, should not be shared during the outbreak.
Consider Pregnancy and Preconception Plans
A pregnant woman with a positive HSV result should inform her obstetric team, particularly if the infection was newly diagnosed, symptoms developed during pregnancy or the viral type and site remain uncertain.
The timing of infection is clinically important. Newly acquired genital HSV late in pregnancy carries a greater neonatal risk than longstanding recurrent infection because maternal protective antibodies may not yet have developed [1,9].
Fresh genital lesions during pregnancy should be tested promptly. A first recognized lesion does not always prove recent infection, so lesion PCR, type-specific IgG and previous history should be reviewed together.
Women with recurrent genital herpes may be offered suppressive antiviral treatment during the final weeks of pregnancy to reduce recurrence and shedding near delivery. Management at labour depends on current lesions, prodromal symptoms, infection history and obstetric assessment [1,9].
A positive HSV-1 IgG result alone does not establish genital infection or determine delivery method. The anatomical site and clinical history must be clarified.
Patients planning pregnancy should review antiviral medicines, Ayurvedic formulations, supplements and herbo-mineral preparations before conception. A treatment used before pregnancy should not automatically be continued unchanged after conception.
Create a Documented Baseline
A reliable baseline is necessary for evaluating future progress. The patient should retain the original laboratory report rather than keeping only a handwritten note or verbal summary.
The baseline should include the HSV type, specimen source, test method, numerical IgG value, reference range, date, lesion location, recurrence history and all medicines used.
The frequency and duration of outbreaks should also be recorded. A patient who experiences six episodes per year has a different baseline from a patient with one remote lesion and no subsequent symptoms.
Associated symptoms such as genital burning, urinary discomfort, bowel disturbance, sleep disruption, nerve pain and recurrent candidiasis should be documented separately. This helps distinguish improvement in HSV recurrence from improvement in other coexisting conditions.
For example, a patient may have fewer blisters after treatment but continue to experience urinary burning because of an untreated urinary infection. Separate documentation prevents one condition from being confused with another.
Begin an Individualized Treatment Plan
Treatment should be based on whether the patient has a first episode, recurrent disease, frequent shedding concerns, pregnancy, immune suppression or a severe complication.
Modern English Medicine may use episodic antiviral treatment for individual recurrences or daily suppressive treatment when episodes are frequent, painful or associated with partner-transmission concerns [1].
Ayurvedic treatment should assess Prakriti, current Dosha imbalance, Agni, bowel function, sleep, tissue healing, recurrence pattern and associated illnesses before selecting medicines or Panchakarma.
A patient with burning, moist erosions and loose stools may require a different Ayurvedic sequence from a patient with dry fissures, constipation, sacral discomfort and poor sleep, even when both have confirmed HSV-2.
The initial treatment objective is to control active symptoms and stabilize the patient. The longer-term curative-intent phase addresses recurrence tendency, tissue resilience, associated health disturbances and sustained recovery through individualized Rasayana planning.
Panchakarma may be considered in suitable patients according to strength, season, digestive condition and medical stability. It should not be started indiscriminately during pregnancy, severe weakness, dehydration or an acute complicated outbreak.
Monitor Progress Over Time
Progress should be evaluated through the frequency and severity of outbreaks, duration of symptoms, tissue healing, length of symptom-free intervals and need for repeated medication.
A patient who moves from monthly outbreaks to one mild episode in six months has shown substantial improvement, although longer observation is required before the result is considered permanent.
Persistent fissures, burning, urinary symptoms or nerve pain should be reassessed rather than assuming that the treatment has failed or that every symptom is continuing HSV activity.
Serial IgG testing, when clinically selected, should use the same validated method whenever possible. Unexpected changes should be confirmed before they are used to judge the outcome.
If a new lesion appears during follow-up, prompt type-specific lesion NAAT/PCR provides the most relevant evidence of whether HSV is active in that episode.
Sustained recovery is assessed through the combined pattern of clinical stability, longer symptom-free intervals, reduced treatment dependence, improvement in associated health findings and consistent serial laboratory evidence rather than through one isolated report.
Seek Urgent Care When Necessary
Eye pain, blurred vision, light sensitivity or significant eye redness requires urgent ophthalmic assessment.
Severe headache, neck stiffness, confusion, speech disturbance, weakness, seizures or altered consciousness requires emergency neurological evaluation.
Inability to urinate, increasing bladder pressure, severe sacral pain or new leg weakness requires prompt medical assessment.
Extensive rapidly spreading lesions, high fever, difficulty swallowing, jaundice or severe weakness requires urgent review, especially in an immunocompromised patient.
Any suspected first genital outbreak during late pregnancy should be assessed promptly by the obstetric team.
Blisters, poor feeding, unusual sleepiness, breathing difficulty, fever, low temperature or seizures in a newborn require immediate emergency care.
FAQs
HSV-1 vs HSV-2 questions commonly arise after a positive blood test, a first genital outbreak or recurrent symptoms without typical blisters. The viral type, anatomical location, test method and recurrence pattern must be interpreted together before treatment or long-term recovery is assessed.
What Is the Main Difference Between HSV-1 and HSV-2?
HSV-1 most commonly causes oral herpes, while HSV-2 most commonly causes genital herpes. However, HSV-1 can cause genital infection, and HSV-2 can occasionally infect the mouth. Genital HSV-2 usually recurs and sheds more frequently than genital HSV-1.
Is HSV-1 or HSV-2 Worse?
Neither type is universally worse in every patient. Genital HSV-2 generally causes more frequent recurrences and asymptomatic shedding, while HSV-1 can still cause severe oral, genital, ocular or neurological disease .
Can HSV-1 Cause Genital Herpes?
Yes. Genital HSV-1 is commonly transmitted through oral-genital contact, including when the partner has no visible cold sore. It may cause a painful first episode but usually recurs less frequently than genital HSV-2 .
Can HSV-2 Cause Oral Herpes?
Yes, but oral HSV-2 is uncommon. HSV-2 is better adapted to the genital region and generally reactivates less frequently when it infects the mouth.
Can HSV-1 Turn Into HSV-2?
No. HSV-1 and HSV-2 are separate viral types, and one cannot transform into the other. A person with HSV-1 can later acquire HSV-2 through a separate exposure.
Can a Person Have Both HSV-1 and HSV-2?
Yes. A person may have oral HSV-1 and genital HSV-2 or may acquire both viral types at different times. Blood tests can identify antibodies to both types but may not establish the anatomical site of HSV-1 infection.
Does Positive HSV-1 IgG Mean Genital Herpes?
No. Positive HSV-1 IgG confirms previous exposure but usually cannot determine whether the infection is oral or genital. A type-specific sample from a genital lesion provides stronger evidence of genital HSV-1.
Does Positive HSV-2 IgG Mean a Recent Infection?
No. HSV-2 IgG cannot determine when infection occurred or who transmitted it. Low-positive results may require confirmation because some commercial tests can produce false-reactive findings near the assay cutoff .
Can Herpes Spread Without Blisters?
Yes. HSV can spread through asymptomatic shedding when no blister, ulcer or crust is visible. Genital HSV-2 generally sheds more frequently than genital HSV-1.
Can HSV Cause Symptoms Without Visible Blisters?
Yes. HSV may cause tingling, burning, itching, fissures, redness, painful urination or localized nerve discomfort without a typical blister cluster. Similar symptoms can also result from candidiasis, dermatitis, urinary disorders or pelvic-floor dysfunction.
Which Test Is Best for HSV-1 and HSV-2?
A type-specific lesion NAAT/PCR is the preferred test when a fresh blister, fissure, erosion or ulcer is present. Type-specific IgG may help when no lesion is available, but it shows previous exposure rather than active viral replication.
Is HSV IgM a Reliable Test?
No. HSV IgM is not reliably type-specific and may become positive during either an initial infection or a recurrence. It cannot accurately determine whether HSV was acquired recently.
Can a Negative HSV Test Exclude Infection?
Not always. A negative result from an old or healing lesion may occur because viral shedding has already stopped. A negative IgG result obtained soon after exposure may also occur before antibodies have developed.
Which Type Causes More Genital Recurrences?
Genital HSV-2 generally causes more recurrences than genital HSV-1. Median estimates suggest approximately five HSV-2 recurrences during the first year compared with approximately one recurrence after genital HSV-1, although individual patterns vary.
Can Condoms Completely Prevent HSV Transmission?
No. Condoms reduce transmission risk but do not cover every area from which HSV may shed, including the vulva, scrotum, buttocks, perineum and perianal skin. Protection improves when condoms are combined with avoiding contact during symptoms and appropriate suppressive treatment.
Does HSV Affect Pregnancy?
Either HSV-1 or HSV-2 can cause genital infection during pregnancy. The greatest neonatal risk occurs when genital HSV is acquired close to delivery because maternal protective antibodies may not have had sufficient time to develop.
Does HSV Cause Infertility?
HSV is not generally considered a direct cause of infertility. Patients with fertility difficulty still require evaluation for ovulatory disorders, endometriosis, tubal disease, hormonal abnormalities, semen problems and other reproductive conditions.
What Should Be Done After a Positive HSV Result?
The report should be reviewed for the HSV type, specimen source, assay method, numerical value and reference range. Fresh lesions should be tested promptly, low-positive HSV-2 results may require confirmation, and associated genital symptoms should be evaluated for possible coexisting conditions.
Can HSV-1 or HSV-2 Be Cured Permanently?
Permanent recovery should be assessed through sustained absence of outbreaks, stable tissue healing, resolution of associated symptoms, reduced dependence on repeated medication and consistent serial laboratory findings. One healed lesion, one symptom-free month or one isolated test result is not sufficient to establish the final outcome.
The complete curative-intent framework, including viral latency, serial IgG and DNA PCR assessment, Panchakarma, Rasayana and long-term recovery criteria, is explained in the pillar article Can Herpes Be Cured Permanently? Real Cure Approach.
References
[1] Centers for Disease Control and Prevention. (2021). Genital herpes. In Sexually transmitted infections treatment guidelines, 2021. CDC clinical guideline
Brief: Covers differences between genital HSV-1 and HSV-2, lesion PCR, type-specific IgG, confirmation of low-positive results, antiviral treatment, asymptomatic shedding, pregnancy and complications.
[2] World Health Organization. (2025, May 30). Herpes simplex virus. WHO fact sheet
Brief: Reviews transmission, symptoms, recurrence and antiviral treatment. Provides global estimates of approximately 3.8 billion HSV-1 infections among people younger than 50 and 520 million HSV-2 infections among people aged 15–49.
[3] World Health Organization. (2024, December 11). Over 1 in 5 adults worldwide has a genital herpes infection—WHO. WHO global estimates
Brief: Reports an estimated 846 million people aged 15–49 living with genital herpes in 2020. Discusses the contributions of genital HSV-1, HSV-2 and dual infection to the global burden.
[4] Johnston, C., & Wald, A. (2024). Genital herpes. JAMA, 332(10), 835–836. JAMA clinical review
Brief: Summarises diagnosis, recurrence, asymptomatic shedding and treatment. Supports the comparison of approximately five genital HSV-2 recurrences versus one genital HSV-1 recurrence during the first year.
[5] Johnston, C., Magaret, A., Son, H., Stern, M., Rathbun, M., Renner, D., Szpara, M. L., Gunby, S., Ott, M., Jing, L., Campbell, V. L., Huang, M.-L., Selke, S., Jerome, K. R., Koelle, D. M., & Wald, A. (2022). Viral shedding 1 year following first-episode genital HSV-1 infection. JAMA, 328(17), 1730–1739. Full text
Brief: This prospective cohort of 82 participants detected genital HSV-1 shedding on 12.1% of sampled days approximately two months after infection and 7.1% approximately eleven months after infection. Most shedding occurred without symptoms.
[6] Patel, R., Green, J., Moran, B., Clarke, E., Seneviratne, K., Evans, C., Young, F., Nicholson, M., Pelosi, E., Kingston, M., & Foley, E. (2025). British Association of Sexual Health and HIV UK national guideline for the management of anogenital herpes, 2024. International Journal of STD & AIDS, 36(2), 90–105. Full text
Brief: Covers typical and atypical presentations, lesion testing, counselling, antiviral treatment and complications. Includes fissures, erosions, proctitis, urinary retention and care of immunocompromised patients.
[7] U.S. Preventive Services Task Force. (2023, February 14). Genital herpes infection: Serologic screening. USPSTF recommendation
Brief: Recommends against routine serological screening in asymptomatic adolescents and adults, including pregnant people, because false-positive diagnoses can cause harm. Supports careful selection and interpretation of blood testing.
[8] U.S. Food and Drug Administration. (2023, December 27). HSV-2 tests for genital herpes can produce false reactive results: Letter to clinical laboratory staff and health care providers. FDA safety communication
Brief: Highlights false-reactive HSV-2 results, particularly near the assay cutoff or in people with a low likelihood of infection. Supports counselling and confirmatory testing according to appropriate clinical guidance.
[9] American College of Obstetricians and Gynecologists. (2020). Management of genital herpes in pregnancy: ACOG Practice Bulletin No. 220. Obstetrics & Gynecology, 135(5), e193–e202. ACOG clinical guidance
Brief: Covers maternal assessment, neonatal risk, antiviral management and delivery planning. Addresses genital lesions or prodromal symptoms during labour and first episodes acquired late in pregnancy.
[10] Corey, L., Wald, A., Patel, R., Sacks, S. L., Tyring, S. K., Warren, T., Douglas, J. M., Jr., Paavonen, J., Morrow, R. A., Beutner, K. R., Stratchounsky, L. S., Mertz, G., Keene, O. N., Watson, H. A., Tait, D., & Vargas-Cortes, M. (2004). Once-daily valacyclovir to reduce the risk of transmission of genital herpes. The New England Journal of Medicine, 350(1), 11–20. PubMed
Brief: This randomised trial enrolled 1,484 immunocompetent heterosexual HSV-2-discordant couples. Daily valacyclovir reduced symptomatic transmission, overall acquisition, genital shedding and recurrence compared with placebo.