




- Understanding Cold Sores vs Herpes
- What Is a Cold Sore?
- What Is Herpes?
- Cold Sores vs Herpes: Key Differences and Similarities
- Cold Sores vs Oral and Genital Herpes
- Are Cold Sores Always Herpes?
- Cold Sores vs Herpes: Outbreak Stages
- Cold Sores vs Herpes Transmission
- Is a Cold Sore an STI?
- Cold Sores vs Herpes Recurrence
- Cold Sores vs Herpes Testing
- Cold Sores vs Herpes: When to Seek Care
- Cold Sores vs Herpes Treatment
- Cold Sores vs Herpes in Ayurveda
- Can Herpes Be Cured Permanently?
- Ayurvedic Diet for Cold Sores and Herpes
- Modern Treatment: Suppression Only
- Long-Term Complications if Herpes Is Left Untreated
- Frequently Asked Questions (FAQs)
- References
Here’s Why the Confusion Exists.
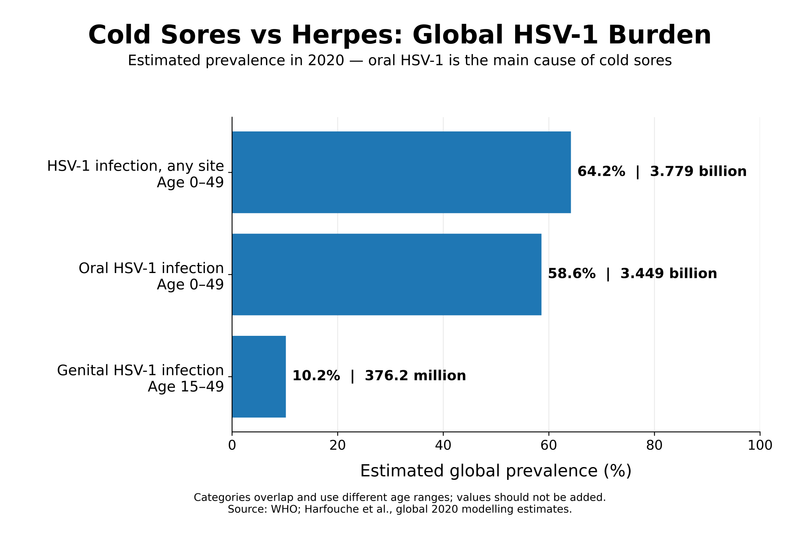
The topic Cold Sores vs Herpes often sparks misunderstanding, many assume they’re entirely different conditions. In reality, cold sores are a visible symptom of the herpes simplex virus (HSV), typically HSV-1. According to the World Health Organization, over 3.7 billion people under age 50 are infected with HSV-1 globally [1]. Yet most individuals don’t realize that their cold sore is actually a form of oral herpes.
The confusion stems from how we label and perceive the word “herpes.” While genital herpes (often caused by HSV-2) carries a heavy stigma, cold sores are socially accepted and often seen as minor. This false divide in public understanding leads many to ignore the viral nature of cold sores and the potential risks of transmission.
Understanding Cold Sores vs Herpes
Yes. True cold sores are a form of herpes, usually caused by herpes simplex virus type 1, or HSV-1. In the comparison of cold sores vs herpes, the main distinction is that a cold sore is a visible symptom, while herpes refers to the broader viral infection that can affect the mouth, genitals, eyes, fingers or surrounding skin. HSV-2 can also infect the oral region, although it causes far fewer oral infections than HSV-1 [1,2,6].
A cold sore is commonly called a fever blister or herpes labialis. It usually begins with tingling, burning, itching or tenderness around the lip before developing into one or more closely grouped, fluid-filled blisters. The blisters may break, form a shallow ulcer and then crust before the skin heals. Recurrent cold sores commonly appear at or near the lip border, although a first oral HSV infection may cause more extensive sores inside the mouth, swollen gums, fever, fatigue or enlarged lymph nodes [6,8].
A Cold Sore Is a Symptom, Not a Separate Virus
The terms used to describe HSV can be confusing because they refer to different parts of the same clinical picture. HSV-1 and HSV-2 identify the virus type. Oral herpes identifies the anatomical site of infection. A cold sore describes the visible blister or ulcer that may appear when oral HSV becomes active.
This means a person can carry oral HSV without having a visible cold sore at the time. Some people develop frequent recurrences, some experience only mild tingling or irritation, and others remain without recognizable symptoms for long periods. The absence of a blister does not necessarily mean the infection was never present, because HSV can remain inactive within sensory nerve tissue and reactivate periodically [1,8].
A cold sore does not automatically mean that a person has genital herpes. Many oral HSV-1 infections are acquired during childhood or adulthood through nonsexual oral contact, including kissing. The presence of a cold sore therefore cannot determine when the infection occurred, who transmitted it or whether it was sexually acquired [1,2].
However, oral HSV-1 can be transmitted to the genital region through oral-genital contact. In that situation, the infection remains HSV-1 but is classified by its new location as genital HSV-1. Similarly, although HSV-2 is more strongly associated with genital herpes, it can occasionally infect the mouth. Virus type and body location must therefore be considered separately when interpreting symptoms or laboratory reports [1,2].
Are All Sores on the Lips or Inside the Mouth Herpes?
Not every painful spot around the mouth is a cold sore. Pimples, angular cheilitis, contact dermatitis, impetigo, cracked lips, traumatic ulcers and canker sores may resemble herpes but have different causes and require different management.
Canker sores, also called aphthous ulcers, usually form inside the lips, cheeks or on the tongue. They are commonly round or oval, with a white or yellow centre and a red border. Unlike cold sores, canker sores are not caused by HSV and are not contagious. Cold sores more often appear as a cluster of small blisters on or around the outer lip, although oral HSV can occasionally produce internal mouth lesions, particularly during a first infection [6].
Location alone may not always establish the diagnosis. A fresh cluster of blisters preceded by tingling is more suggestive of HSV than a single internal mouth ulcer, but atypical, recurrent or unexplained lesions may require clinical examination and appropriate testing. Visual diagnosis becomes less reliable when the lesion is already healing, when symptoms are mild or when the patient has applied creams that alter its appearance.
What a Cold Sore Does and Does Not Tell You
A medically confirmed cold sore establishes that HSV is affecting the oral region, most commonly HSV-1. It does not prove genital infection, recent sexual transmission, infidelity or a newly acquired infection. HSV may remain unrecognized for years before the first noticeable recurrence, and routine antibody testing cannot determine the precise date or anatomical site of an HSV-1 infection [2–4].
A cold sore should nevertheless be treated as potentially contagious from the earliest tingling or burning stage until the lesion has fully healed. Direct contact with the affected area should be avoided, particularly kissing, oral sex and touching the sore before touching the eyes. Transmission risk is highest when an active blister or ulcer is present, although viral shedding may occasionally occur without visible symptoms [1,2].
From an Ayurvedic clinical perspective, HSV should not be presented as identical to a single classical disease description. Ayurveda evaluates the individual pattern of burning, redness, blistering, recurrence, digestion, sleep, stress and general resistance. Pitta refers to heat and inflammatory activity, Rakta to the blood tissue, and Ojas to systemic vitality and resilience. Pitta-Rakta involvement may help explain the inflammatory symptom pattern in some patients, but it does not replace virological diagnosis or establish a direct equivalence between HSV and Visarpa described in the classical texts [10].
What Is a Cold Sore?

Cold sores are fluid-filled blisters usually caused by HSV-1, and they’re more serious than they appear. Cold sores—also called fever blisters—are small, painful lesions that usually appear around the lips, mouth, or nose. While they may seem minor, they are in fact one of the most visible symptoms of herpes simplex virus type 1 (HSV-1). In some cases, they can also be caused by HSV-2, particularly through oral-genital contact [2].
Key Points of a Cold Sore:
- Initial symptoms: Tingling, itching, burning before the blister appears
- Blister stage: Red, swollen bumps that become fluid-filled and painful
- Crusting phase: Blisters burst, dry out, and form a yellow-brown crust
- Healing: Usually clears within 7–10 days without scarring
Cold sores are highly contagious, especially during the blister and crusting stages. However, asymptomatic shedding—when the virus is spread without visible symptoms—makes them dangerous even when no sores are present [1].
Common Triggers:
- Physical or emotional stress
- Hormonal changes (e.g., menstruation)
- Fever or respiratory illness
- Excessive sun exposure or windburn
- Immune suppression (e.g., post-viral fatigue)
Ayurvedic Understanding of Cold Sores
In Ayurveda, cold sores align with Mukha Daha (burning in the mouth), Utsanna Vrana (raised wound), and Rakta Dushti (vitiation of blood tissue). They are typically classified as a Pitta-Rakta disorder, where excess heat in the blood manifests externally during lowered immunity or stress [2].
Cold Sores as a Sign of:
- Pitta aggravation: Seen in burning, inflammation, and redness
- Rakta Dushti: Impure blood due to toxins (Ama) or viral burden
- Srotas dushti: Blockage in microchannels of the skin (Tvak) and mucosa (Mukha srotas)
Clinical Note:
Although cold sores are self-limiting in healthy individuals, frequent recurrences may indicate poor immune resilience and chronic viral latency. This opens the gateway for Ayurvedic Rasayana therapy, which targets both systemic immunity and local viral load.
What Is Herpes?
Herpes as a Systemic Viral Infection
Herpes is a chronic viral condition caused by the herpes simplex virus (HSV), classified into two major types HSV-1 and HSV-2. HSV-1 is primarily responsible for oral herpes, including cold sores around the mouth, but it has increasingly been identified in genital infections due to oral-genital transmission. HSV-2, on the other hand, more commonly causes genital herpes and is known for its higher rates of recurrence and asymptomatic viral shedding [3].
How the Herpes Virus Functions
Once the virus enters the body through mucosal membranes or broken skin, it establishes a lifelong presence. It travels through sensory nerves and becomes dormant in nerve ganglia, most commonly the trigeminal ganglion in oral herpes and the sacral ganglia in genital herpes. This latency phase allows the virus to remain undetected by the immune system. When triggered by factors such as stress, sunlight, hormonal shifts, or immune suppression, the virus reactivates and travels back to the skin, causing recurrent lesions or asymptomatic shedding [4].
Globally, over 67% of people under the age of 50 are infected with HSV-1, while about 13% are infected with HSV-2 [5]. The majority of infections remain unrecognized due to the absence of noticeable symptoms or misattribution to other minor skin conditions.
Ayurvedic Interpretation of Herpes
In classical Ayurveda, herpes is interpreted through the lens of systemic imbalance, primarily involving aggravated Pitta and Kapha Doshas. The condition affects multiple tissues (Dhatus) notably Rasa (plasma), Rakta (blood), and Mamsa (muscle) and disrupts important bodily channels (Srotas), particularly Tvak (skin), Shukra (reproductive tissue), and Majja (nervous system).
The condition is often associated with disease categories such as Upadansha (venereal ulcers), Pittaja Visarpa (spreading inflammatory lesions), or Krimi Janya Twak Vikara (viral/parasitic skin disorders). These descriptions appear in texts such as Charaka Samhita Chikitsa Sthana, where such conditions are classified under endogenous imbalances (Nija Rogas) due to internal vitiation of Doshas and accumulation of Ama (toxins) (([All Refrence][Kumar, A., & Choudhary, R. (2021). Ayurvedic strategies in management of viral diseases. Journal of Ayurveda and Integrative Medicine, 12(2), 312–320. https://doi.org/10.1016/j.jaim.2020.05.007]).
Clinical Relevance
While modern antivirals can reduce outbreaks and viral load temporarily, they do not eliminate the latent virus from the body. Ayurveda adopts a more integrative path targeting the root cause through detoxification (Shodhana), immune modulation, and Rasayana therapy. The goal is not just viral suppression, but the rejuvenation of Dhatus, restoration of Ojas, and complete elimination of the disease origin.
Cold Sores vs Herpes: Key Differences and Similarities
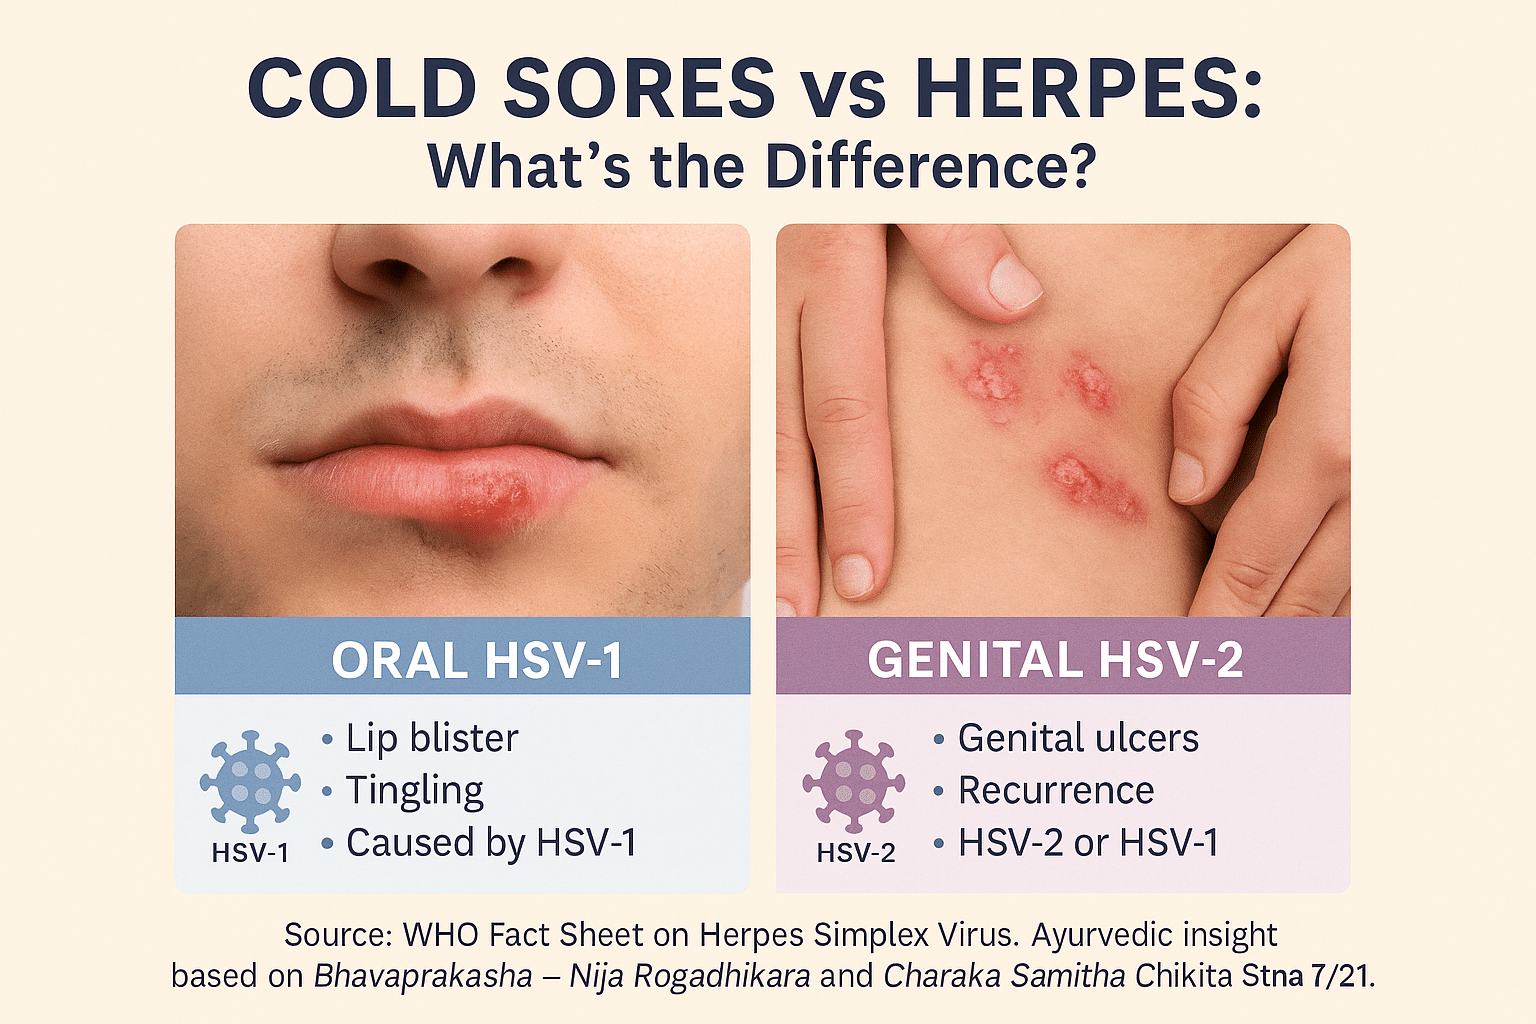
Understanding the Overlap
Many people wonder whether cold sores and herpes are the same thing. The short answer is: cold sores are a form of herpes, typically caused by HSV-1. However, herpes as a condition includes both oral and genital infections, caused by either HSV-1 or HSV-2. While they share many features, understanding their differences is essential for diagnosis, prevention, and treatment [6].
Cold Sores vs Oral and Genital Herpes
When comparing cold sores vs herpes, the clinically important differences involve the site of infection, the HSV type involved, the pattern of recurrence and the route of transmission. Cold sores are most often associated with oral HSV-1, while genital herpes is more commonly associated with HSV-2. However, either HSV type can infect either the oral or genital region, so symptoms and lesion location cannot always identify the viral type without appropriate testing [1,2,4].
| Clinical feature | Cold sore | Oral herpes | Genital herpes |
|---|---|---|---|
| What the term means | A visible blister or ulcer caused by oral HSV | HSV infection involving the mouth, lips or nearby facial skin | HSV infection involving the genital, anal or surrounding region |
| Most commonly associated virus | HSV-1 | HSV-1; oral HSV-2 is less common | HSV-2 more commonly; HSV-1 can also cause genital infection |
| Typical location | Lip border, lips or skin surrounding the mouth | Lips, gums, palate, tongue, inside the mouth or nearby facial skin | Vulva, vagina, cervix, penis, scrotum, perineum, anus, buttocks or upper thighs |
| Typical appearance | One or more grouped, fluid-filled blisters that rupture, crust and heal | Cold sores, mouth ulcers, inflamed gums or no visible lesions | Grouped blisters, shallow ulcers, fissures, redness, tender bumps or no visible lesions |
| Common warning symptoms | Tingling, burning, itching or tenderness near the lip | Oral tingling, burning, gum pain, mouth soreness or facial sensitivity | Genital tingling, itching, burning, nerve-like pain or pain during urination |
| First recognized infection | May cause a single localized episode or extensive oral symptoms | May cause fever, swollen gums, multiple mouth sores, fatigue and enlarged lymph nodes | May cause widespread genital lesions, fever, body aches, headache and swollen groin lymph nodes |
| Recurrence pattern | Commonly returns near the same area of the lip | Oral HSV-1 may recur periodically as cold sores | Genital HSV-2 generally recurs more frequently than genital HSV-1 |
| Transmission route | Direct oral contact, kissing or oral-genital contact | Contact with infected oral skin, mucosa or secretions | Genital, anal or oral sexual skin-to-skin contact |
| Can spread without visible sores? | Yes, because asymptomatic viral shedding can occur | Yes | Yes |
| Does it automatically mean an STI? | No. Oral HSV-1 may be acquired through nonsexual contact | No. The classification depends on how and where it was acquired | Genital herpes is generally classified as a sexually transmitted infection |
| Can it cause infection at another body site? | Oral HSV-1 can cause genital HSV-1 through oral sex | Oral infection can be transmitted to genital skin through direct contact | Genital HSV can occasionally infect the oral region through direct oral-genital exposure |
| Can symptoms identify HSV-1 or HSV-2? | No | No | No |
| Preferred test when a fresh lesion is present | Lesion swab for HSV PCR or another nucleic acid amplification test | Lesion swab for HSV PCR when diagnosis is uncertain | Lesion swab for type-specific HSV PCR or another nucleic acid amplification test |
| Limitation of HSV IgG testing | Cannot confirm that a lip lesion is currently caused by HSV | Cannot determine whether HSV-1 antibodies represent oral or genital infection | Can indicate prior HSV exposure but cannot establish the exact infection date |
| Clinical importance | Confirms a manifestation of oral herpes when correctly diagnosed | Includes symptomatic and asymptomatic oral HSV infection | Requires type-specific assessment because genital HSV-1 and HSV-2 have different recurrence patterns [1–4,6,8] |
Location and HSV Type
Oral herpes most commonly affects the lips, the border between the lip and surrounding skin, the area around the mouth and occasionally the nose. During a first oral infection, lesions may also involve the gums, tongue, palate or inner mouth. Recurrent oral herpes usually returns near the original site because the virus reactivates through the same sensory nerve distribution [6,8].
Genital herpes may affect the vulva, vagina, cervix, penis, scrotum, perineum, anus, buttocks or nearby upper thighs. Lesions may be obvious clusters of blisters, but they can also appear as small cuts, fissures, redness, tender bumps or shallow ulcers. Mild genital symptoms are frequently mistaken for shaving irritation, friction, yeast infection, ingrown hair or allergic dermatitis [2,4].
HSV-1 is responsible for most oral herpes and cold sores. It can also cause genital herpes when transmitted from the mouth to the genital region during oral sex. HSV-2 more commonly causes genital infection, although oral HSV-2 can occur. The labels HSV-1 and HSV-2 therefore identify the virus type rather than a fixed body location [1,2].
An oral HSV-1 infection does not normally transform into HSV-2 or automatically spread internally to the genital region. A genital HSV-1 infection develops when HSV-1 is introduced directly to genital skin or mucosa, most commonly through oral-genital contact. The same principle applies to oral HSV-2, which requires exposure of the oral region to HSV-2 [2,4].
Identifying both the viral type and the anatomical site is clinically valuable. A laboratory report showing HSV-1 IgG cannot determine whether the infection is oral or genital. When a fresh lesion is present, a properly collected lesion swab tested by PCR or another nucleic acid amplification method can confirm HSV and distinguish HSV-1 from HSV-2 more accurately [3,4].
Symptoms and Recurrence Patterns
Recurrent cold sores commonly begin with localized tingling, burning, itching or tenderness. Small grouped blisters may then appear, rupture, form a shallow ulcer and develop a crust before healing. The complete episode commonly lasts approximately one to two weeks, although treatment started during the prodromal stage may shorten the symptomatic period [6,8].
A first oral HSV infection may be more extensive than a recurrent cold sore. Some patients develop fever, painful gums, multiple mouth ulcers, swollen lymph nodes, fatigue or difficulty eating and drinking. Others experience such mild symptoms that the first infection is never recognized [6,8].
Genital herpes can produce burning, itching, nerve-like discomfort, painful blisters, ulcers, genital tenderness and pain during urination when urine contacts an external lesion. A first recognized episode may also cause fever, body aches, headache or enlarged groin lymph nodes. Cervical, vaginal or internal anal lesions may not be visible without clinical examination [2,4].
Symptoms alone cannot reliably distinguish genital HSV-1 from genital HSV-2. Both may cause similar lesions during an initial episode, but their long-term recurrence patterns differ. Genital HSV-2 generally reactivates and sheds more frequently than genital HSV-1. Recurrences after genital HSV-1 usually become less frequent over time, although individual patterns vary [2,4].
Oral HSV-1 commonly reactivates as a cold sore, particularly after fever, illness, sunlight exposure, local trauma, sleep deprivation or significant stress. Oral HSV-2 is less likely to recur frequently because HSV-2 is biologically better adapted to the genital region than the oral region [4,8].
Neither oral nor genital herpes always causes visible blisters. Some recurrences produce only tingling, burning, itching, redness or a small fissure. Other episodes remain entirely asymptomatic. Patients with repeated unexplained symptoms should avoid assuming that every episode is HSV, but they should also avoid excluding herpes solely because a typical blister is absent.
Transmission and Sexual Health
Oral HSV is mainly transmitted through direct contact involving the mouth, lips, saliva or affected oral skin. Kissing is a common route, while oral sex can transmit oral HSV-1 to a partner’s genital region. Genital HSV is transmitted mainly through direct genital, anal or oral contact with infected skin or mucosa [1,2].
The risk of transmission is greatest during tingling, burning, blistering, ulceration and crusting. Viral shedding can also occur when the skin appears normal, which means the absence of a visible lesion does not eliminate transmission risk. However, this does not mean that transmission occurs during every contact or that every symptom-free day carries the same degree of risk [1,2,4].
Having a cold sore does not prove that the infection was sexually acquired. Oral HSV-1 is frequently acquired through nonsexual contact, sometimes many years before the first recognized outbreak. A cold sore therefore does not establish recent exposure, infidelity or genital infection [1,2].
When oral HSV-1 is transmitted through oral sex, the receiving partner may develop genital HSV-1. The genital infection is classified according to its location, while the viral type remains HSV-1. This distinction is important because genital HSV-1 usually has a lower long-term recurrence and shedding rate than genital HSV-2 [2,4].
During an active cold sore or the warning stage before a lesion appears, patients should avoid kissing and oral-genital contact. Condoms and dental dams can reduce sexual transmission risk, but they cannot provide complete protection because HSV may be present on surrounding skin not covered by the barrier [2,4].
Clinical counselling should consider the location of symptoms, laboratory-confirmed viral type, recurrence frequency and the health status of both partners. A patient with confirmed oral HSV-1 requires different counselling from a patient with genital HSV-2, even though both infections belong to the herpes simplex virus group.
Are Cold Sores Always Herpes?
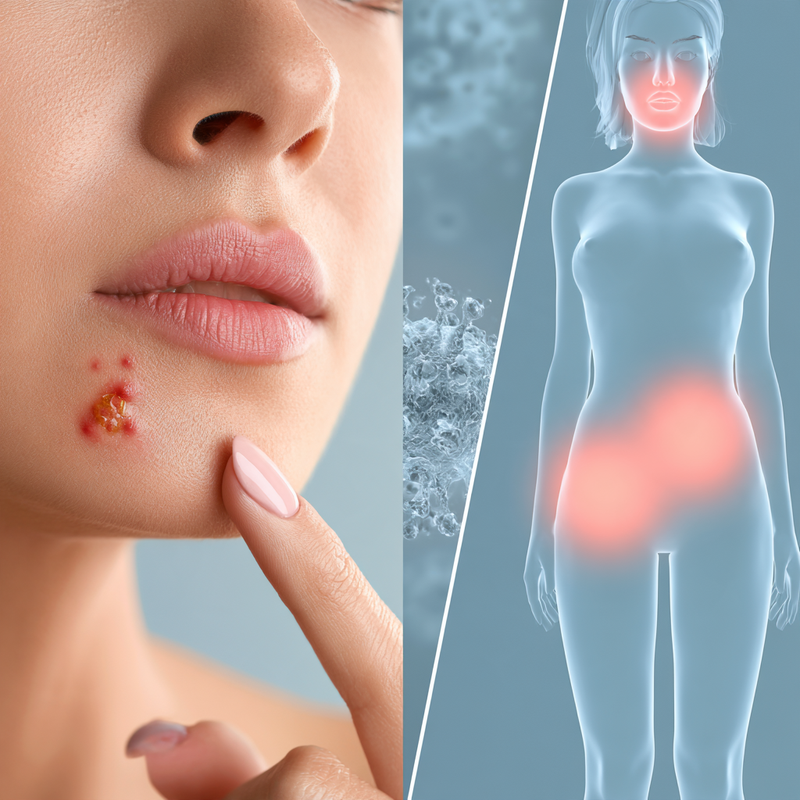
In the cold sores vs herpes comparison, the answer depends on whether the lesion is truly a cold sore. A medically diagnosed cold sore, also called herpes labialis or a fever blister, is caused by herpes simplex virus. However, patients often use the term “cold sore” for any painful bump, crack, ulcer or crust around the mouth, and many of these lesions are not caused by HSV [6,8].
When a Lip Lesion Is Likely HSV
A recurrent cold sore commonly begins with tingling, burning, itching or tenderness in a small area near the lip. Within several hours or the following day, one or more closely grouped, fluid-filled blisters may develop. The blisters can rupture, form shallow ulcers and then crust before the skin heals, usually without permanent scarring [6,8].
The location is often close to the border between the lip and surrounding facial skin. Recurrent episodes may return to approximately the same area because the virus reactivates through the same sensory nerve pathway. Sun exposure, fever, another illness, emotional stress, local trauma, hormonal changes and sleep disruption may precede an outbreak, although the pattern differs between patients [1,8].
A first oral HSV infection may look different from a typical recurrent cold sore. It can cause widespread mouth pain, inflamed or bleeding gums, multiple ulcers, fever, fatigue, swollen lymph nodes and difficulty eating or drinking. Some patients have only mild symptoms during the initial infection and do not recognize it until a later recurrence appears near the lip [6,8].
The absence of a visible blister does not exclude oral HSV. Some reactivations produce only localized tingling, burning, redness, a small fissure or mild tenderness. HSV may also shed from oral skin or mucosa without producing noticeable symptoms, although the likelihood of transmission is generally greater when prodromal symptoms, blisters or ulcers are present [1,2].
When a Lip Sore May Not Be Herpes
A canker sore usually develops inside the mouth rather than on the external lip border. It commonly appears as a single round or oval ulcer with a white or yellow centre and a red margin. Canker sores are not caused by HSV and are not contagious, although they may cause significant pain during eating, drinking or speaking [6].
A pimple generally develops on hair-bearing skin and may have a central whitehead, blocked pore or visible hair follicle. It does not usually begin with the characteristic localized tingling followed by a cluster of clear blisters. Squeezing either a suspected pimple or cold sore can increase inflammation, introduce secondary infection and make clinical assessment more difficult.
Angular cheilitis usually causes redness, cracking, soreness or crusting at one or both corners of the mouth. It may be associated with persistent moisture, denture fit, nutritional deficiency, irritation or secondary fungal or bacterial overgrowth. Unlike a typical cold sore, it often remains confined to the mouth corners and may recur as a fissure rather than a grouped blister eruption.
Impetigo can produce fragile blisters or ulcers with yellow-brown or honey-coloured crusting, particularly around the nose and mouth. It may spread across adjacent skin and is caused by bacteria rather than HSV. Contact cheilitis more often causes diffuse dryness, scaling, swelling or burning after exposure to lip products, toothpaste, cosmetics, dental materials or other irritants.
Chapped lips and traumatic cracks can also be mistaken for herpes. These lesions are usually associated with dryness, cold weather, lip licking, biting, friction or local injury. They do not normally follow the typical progression from prodromal tingling to grouped vesicles, ulceration and crusting.
Location provides useful diagnostic information but is not absolute. Recurrent cold sores usually appear outside the mouth, while canker sores usually occur inside it. Oral HSV can nevertheless cause internal lesions, especially during a first infection, and other conditions may occur on the external lip. Diagnosis should therefore consider lesion appearance, location, recurrence pattern, preceding symptoms and relevant exposure history rather than relying on one feature alone [6,8].
When Testing Is Appropriate
Clinical examination may be sufficient when a patient has a familiar recurrent lesion with a typical prodrome, grouped blisters and a predictable healing pattern. Testing becomes more important when the lesion is new, atypical, unusually severe, slow to heal, repeatedly misdiagnosed or associated with genital symptoms, pregnancy, immune suppression or possible eye involvement.
When a fresh blister or ulcer is present, a swab collected directly from the lesion for HSV PCR or another nucleic acid amplification test provides the most useful confirmation and can distinguish HSV-1 from HSV-2. Sampling is most informative before the lesion has dried or substantially healed. A negative result from an old, crusted or healing lesion may not completely exclude HSV because the amount of detectable virus decreases as healing progresses [3,4].
Type-specific HSV IgG testing may show previous exposure to HSV-1 or HSV-2, but it cannot confirm that a particular lip lesion is caused by HSV. It also cannot determine whether HSV-1 is located orally or genitally, establish the date of infection or identify the person from whom it was acquired. Laboratory findings must therefore be interpreted together with the lesion pattern, clinical history and, whenever possible, direct testing of an active lesion [3,4].
In the cold sores vs herpes discussion, canker sores are an important source of confusion because both conditions can cause painful lesions around the mouth. A cold sore is caused by herpes simplex virus, while a canker sore is a noncontagious oral ulcer that is not caused by HSV. Their location, appearance, symptom pattern and recurrence history usually provide the first diagnostic clues [6,8].
Location and Appearance
Recurrent cold sores most commonly develop on the lip border or the skin immediately surrounding the mouth. They often begin with localized tingling, itching, burning or tenderness before a cluster of small fluid-filled blisters becomes visible. The blisters may join together, rupture, form shallow ulcers and develop a crust before healing [6,8].
Canker sores usually develop inside the mouth, particularly on the inner surface of the lips or cheeks, beneath the tongue or along other soft oral tissues. They commonly appear as one or more round or oval ulcers with a white, yellow or grey centre surrounded by a red margin. They do not normally form a cluster of clear fluid-filled blisters or develop the external crust typically associated with a cold sore [6].
The location distinction is clinically useful but not absolute. A first oral HSV infection may produce widespread ulcers involving the gums, tongue, palate and other oral surfaces. Recurrent intraoral HSV lesions are more likely to involve firmer tissues such as the hard palate or attached gums, whereas canker sores more commonly affect softer, mobile tissues inside the mouth.
Cold sores frequently return near the same area of the lip because HSV reactivates through an established sensory nerve pathway. Canker sores may recur at different locations inside the mouth and do not follow a fixed nerve distribution. A patient who repeatedly develops a blister at nearly the same external lip site is therefore more likely to have recurrent herpes labialis than recurrent aphthous ulceration [8].
The symptoms preceding the lesion may also help. Cold sores are commonly preceded by tingling, burning, itching or unusual sensitivity at the future lesion site. Canker sores may begin with local soreness or burning, but they generally develop directly into an ulcer rather than passing through a visible blister stage.
Cause and Contagiousness
Cold sores result from reactivation of oral HSV, most commonly HSV-1. The virus can be transmitted through direct contact with infected oral skin or mucosa, particularly during prodromal symptoms, blistering and ulceration. Transmission can occasionally occur without a visible lesion because asymptomatic viral shedding is possible [1,2].
Canker sores are not caused by HSV and cannot be passed through kissing, sexual contact, saliva or shared household contact. They are considered inflammatory oral ulcers and may be associated with local trauma, emotional stress, irritation from dental appliances, certain foods or nutritional deficiencies. In some patients, frequent or severe canker sores may accompany gastrointestinal, immune-mediated or systemic inflammatory conditions [6].
A person with a canker sore does not pose an HSV transmission risk from that lesion. However, self-diagnosis may be unreliable when an oral ulcer is new, unusually painful, recurrent or located near the lip. Until the cause is reasonably clear, direct contact with an unexplained blistering lesion should be avoided.
Cold sores and canker sores may also respond differently to treatment. Antiviral medicines may shorten an HSV episode when started early but have no therapeutic role in an ordinary canker sore. Canker-sore management instead focuses on pain control, protection of the ulcer, identification of local irritation and investigation of recurrent disease when clinically indicated.
Applying harsh substances to either lesion can delay healing. Concentrated essential oils, strong acids, undiluted antiseptics and repeated scraping may worsen inflammation, create a secondary wound or alter the appearance needed for accurate diagnosis. Patients should also avoid deliberately rupturing a blister or repeatedly removing the surface covering of an ulcer.
When Diagnosis Is Unclear
A familiar recurrent cold sore may be diagnosed clinically when it follows a consistent pattern of prodromal tingling, grouped external blisters, crusting and healing near the same lip location. A typical canker sore may also be recognized by its isolated internal location, round ulcerated appearance and absence of contagious exposure.
Clinical review becomes more important when a lesion appears for the first time, develops in an unusual location, lasts longer than expected, repeatedly returns, causes difficulty eating or drinking, or is accompanied by fever, swollen gums or multiple oral ulcers. Recurrent mouth ulcers may require assessment for local trauma, nutritional deficiency, medication effects or underlying systemic disease.
When a fresh blister or ulcer may represent HSV, a properly collected lesion swab for PCR or another nucleic acid amplification test can confirm the diagnosis and identify HSV-1 or HSV-2. The sample is most useful while the lesion is fresh, because sensitivity declines after crusting and healing have begun [3,4].
HSV IgG testing cannot reliably determine whether a specific mouth lesion is a cold sore or a canker sore. A positive HSV-1 IgG result shows previous exposure but cannot establish the anatomical location of infection or prove that the current ulcer is caused by HSV. Direct lesion testing is therefore more informative when an active suspicious lesion is available [3,4].
From an Ayurvedic perspective, grouped recurrent blisters with burning and redness may require assessment of Pitta-Rakta involvement, while an isolated internal ulcer may require evaluation of local trauma, digestive disturbance, dietary irritation, nutritional status and stress. These clinical patterns can guide individualized treatment, but they do not replace the distinction between HSV infection and nonviral aphthous ulceration.
Cold Sores vs Herpes: Outbreak Stages
In the cold sores vs herpes comparison, the evolution of a lesion provides important diagnostic information. A recurrent cold sore usually follows a recognizable sequence of localized warning symptoms, blister formation, ulceration, crusting and skin repair. The severity and duration vary, but an uncomplicated episode commonly resolves within one to two weeks [6,8].
Prodromal Stage
The prodromal stage begins before a blister becomes visible. Patients may notice tingling, burning, itching, tightness, tenderness or unusual sensitivity in a small area of the lip or nearby skin. The sensation often develops at or close to the site of a previous outbreak because HSV commonly reactivates through the same sensory nerve pathway [8].
Some episodes progress rapidly from tingling to a visible lesion, while others remain limited to mild redness, swelling or discomfort. A recurrence that produces warning symptoms without a fully developed blister may still represent HSV reactivation, although similar sensations can also occur with irritation, allergy, dryness or local trauma.
The prodromal stage is clinically important because HSV transmission may occur before a blister becomes visible. Kissing, oral sex and direct contact with the affected area should therefore be avoided as soon as familiar warning symptoms begin, rather than waiting for the lesion to appear [1,2].
Treatment intended to shorten an outbreak is generally most effective when started during the prodromal stage or soon after the first visible change. Patients with recurrent cold sores may benefit from recognising their usual warning pattern and discussing an early-treatment plan with their clinician [8,9].
Blister and Ulcer Stages
The affected area may first become red, swollen or raised before several small fluid-filled blisters appear. These vesicles are often closely grouped and may merge into a larger irregular blister. The surrounding skin can feel painful, warm or sensitive, particularly when eating, speaking or stretching the lips [6,8].
The blister fluid contains infectious viral material. Touching, squeezing or deliberately opening the lesion can spread fluid across nearby skin, increase irritation and introduce bacteria into the damaged area. Hands should be washed after accidental contact, and the eyes should not be touched after handling the lesion.
The blisters may then rupture naturally and form shallow, moist ulcers. This stage can be painful and may produce clear or yellowish fluid. It is also one of the periods of greatest transmission risk because the protective skin barrier is disrupted and viral shedding is active [1,2].
A ruptured cold sore should not be repeatedly cleaned with alcohol, hydrogen peroxide, strong acids, undiluted essential oils or other caustic substances. These products may damage new tissue, increase burning and prolong local inflammation. Gentle cleansing and clinician-recommended treatment are more appropriate.
A fresh blister or ulcer provides the best opportunity for direct HSV testing when the diagnosis is uncertain. A lesion swab for PCR or another nucleic acid amplification test becomes less sensitive after the lesion has dried, crusted or substantially healed [3,4].
Crusting and Healing
As the ulcer begins to dry, a yellow, brown or reddish crust may form. The crust can split during talking, eating or smiling, causing brief bleeding or discomfort. Picking or peeling it prematurely may reopen the wound, delay skin repair and increase the risk of secondary bacterial infection.
The lesion gradually becomes smaller as new skin forms underneath. A cold sore is not considered completely healed merely because the blister has disappeared. Direct oral or sexual contact should remain avoided until the crust has separated naturally and the underlying skin has returned to an intact appearance [1,6].
Temporary redness, dryness or mild discolouration may remain after the crust falls away. Recurrent cold sores usually heal without permanent scarring, but scarring becomes more likely when lesions are repeatedly disturbed, secondarily infected or unusually severe.
A typical recurrent episode often resolves within seven to fourteen days. Lesions that continue enlarging, fail to show healing, repeatedly bleed or remain present beyond the expected period require reassessment because the diagnosis may be incorrect or another condition may be delaying recovery [6,8].
First Infection and Recurrent Outbreaks
The first clinically recognised oral HSV infection may be more extensive than a recurrent cold sore. Instead of one localized lesion, patients may develop multiple painful oral ulcers, inflamed gums, fever, fatigue, reduced appetite, swollen lymph nodes and difficulty drinking. Children and medically vulnerable adults require particular attention when oral pain leads to reduced fluid intake [6].
A recurrent outbreak is usually more localized and less severe. It commonly affects the lip border or nearby facial skin and may be preceded by a familiar prodrome. Some patients experience several episodes each year, while others have long symptom-free periods or never develop another clearly recognised lesion [6,8].
Frequent recurrences may be associated with fever, respiratory illness, intense sunlight, physical exhaustion, emotional stress, local trauma, dental procedures, hormonal changes or immune suppression. These factors can contribute to reactivation but do not create HSV in a person who has never acquired the virus [1,8].
Patients should record the date, location, warning symptoms, possible trigger, healing time and any treatment used during each episode. Clear photographs taken at the earliest visible stage may also help a clinician distinguish recurrent herpes from angular cheilitis, dermatitis, impetigo, acne or traumatic injury.
Symptoms Without Visible Blisters
HSV reactivation does not always produce a classic cluster of vesicles. Some patients experience localized tingling, burning, tenderness, redness or a small superficial fissure that resolves without progressing through every visible stage. Others have no recognisable symptoms despite intermittent viral shedding [1,2].
Symptoms without blisters are not specific to HSV. Neuropathic pain, contact reactions, dry skin, dental irritation and other oral conditions can produce similar sensations. Repeated treatment based only on tingling may therefore delay the diagnosis of a non-herpetic condition.
When symptoms recur in the same location with a consistent sequence, clinical suspicion of HSV becomes stronger. When the pattern changes, persists between episodes or affects multiple unrelated sites, reassessment is preferable to assuming that every facial or oral sensation represents another herpes outbreak.
Ayurvedic assessment considers whether the active phase is dominated by burning, redness, blistering, pain or excessive dryness and whether recurrences follow disturbed sleep, stress, digestive imbalance or reduced resilience. Stage-specific assessment may guide individualized care, but it should remain aligned with lesion examination and appropriate virological testing.
Cold Sores vs Herpes Transmission

Cold sores vs herpes transmission depends mainly on direct contact with infected oral or genital skin, mucosa or secretions. Oral HSV commonly spreads through kissing and other close mouth-to-mouth contact, while oral-genital contact can transmit oral HSV-1 to the genital region. Transmission is most likely during tingling, blistering, ulceration and crusting, but it can also occur when the infected area appears normal [1,2,4].
Direct Oral and Sexual Contact
A person with an active cold sore can transmit HSV when the affected lip or surrounding skin directly contacts another person’s mouth, face, genitals or damaged skin. Kissing is therefore a common route of oral HSV transmission, particularly when a blister or ulcer is present.
Oral sex can transmit HSV-1 from the mouth to a partner’s genital or anal region. The resulting infection is genital HSV-1 because the virus type remains HSV-1 while the anatomical site changes. The receiving partner may develop genital blisters, ulcers, burning, pain during urination or no recognizable symptoms [1,2].
HSV can also travel in the opposite direction. Oral contact with genital skin carrying HSV-1 or HSV-2 may cause oral infection, although oral HSV-2 is less common and generally recurs less frequently than oral HSV-1 [2,4].
Transmission does not require visible blood, deep wounds or penetrative intercourse. HSV enters through mucous membranes or small disruptions in the skin that may be too minor to see. Skin-to-skin contact involving an infected but uncovered area may therefore transmit HSV even when condoms or dental dams are used correctly [2,4].
Barrier protection reduces exposure but does not eliminate risk because HSV may be present on nearby skin that is not covered. Avoiding oral, genital and anal contact during warning symptoms and active lesions provides greater protection than relying on barriers alone during an outbreak [2,4].
Transmission Without Visible Sores
HSV may be released from oral or genital skin without causing a visible blister. This is known as asymptomatic viral shedding. A person may therefore transmit HSV while feeling well and believing that the infection is inactive [1,2].
Asymptomatic shedding is intermittent rather than continuous. The absence of a lesion lowers the apparent risk compared with an active outbreak but does not reduce it to zero. Patients should understand this distinction so that they do not assume either that transmission is impossible without sores or that every symptom-free contact will transmit HSV.
Familiar warning sensations such as tingling, burning, itching or localized tenderness may indicate that viral reactivation has begun before a blister appears. Direct oral and sexual contact should be avoided from the beginning of these symptoms until the lesion has completely healed and the skin surface has returned to normal [1,6,8].
A positive HSV IgG result does not show whether viral shedding is occurring at a particular moment. Antibody testing identifies previous immune exposure but cannot determine whether a patient is currently contagious, where HSV is located or whether a partner was exposed during a specific encounter [3,4].
Household Contact and Shared Items
Direct skin or mucosal contact is the principal route of HSV transmission. Routine contact with toilet seats, bedding, swimming pools, soap, clothing, shoes or dry household surfaces is not considered a typical means of acquiring genital herpes [2].
Patients do not need to disinfect the entire home, isolate their clothing or keep separate furniture because of a cold sore. Excessive cleaning can increase anxiety without meaningfully reducing transmission risk. Normal household hygiene and careful avoidance of direct lesion contact are more clinically useful.
During an active cold sore, it is sensible not to share lip balm, lipstick, razors, toothbrushes or objects that have just contacted the lesion or fresh oral secretions. Cups and eating utensils should be cleaned normally before another person uses them. These precautions should not be interpreted to mean that ordinary indirect contact is the main route of HSV spread.
Towels used directly on an active lesion should not be shared before washing, but casual contact with laundered towels or bedding does not create the same risk as kissing or oral-genital contact. The practical priority is preventing transfer of fresh lesion fluid or saliva and avoiding direct contact with the affected skin.
Spread to the Eye, Finger or Other Skin
Touching an active cold sore and then touching the eye may transfer HSV to ocular tissues. Eye pain, redness, light sensitivity, excessive tearing or blurred vision after possible exposure requires prompt medical evaluation because ocular herpes can threaten the cornea and vision.
HSV can also infect a finger through broken skin, producing herpetic whitlow. This may cause swelling, pain and grouped blisters around the fingertip. Patients should wash their hands after applying medicine or accidentally touching a lesion and should avoid biting nails or placing fingers in the mouth during an active outbreak.
Autoinoculation is more likely during a first infection, when immune recognition is still developing, but careful hand hygiene remains appropriate during recurrent episodes. A cold sore should not be deliberately opened, squeezed or repeatedly touched because this increases local trauma and the possibility of bacterial contamination.
Topical medicines should be applied with clean hands or a disposable applicator according to clinical instructions. Applicators, cosmetic products and containers that directly contact the lesion should not be shared.
Protecting Infants and Vulnerable Patients
Adults or children with an active cold sore should not kiss newborn babies. Neonatal HSV can cause severe skin, neurological or disseminated infection, and early symptoms may be subtle. A newborn who develops blisters, fever, poor feeding, unusual sleepiness or irritability after possible HSV exposure requires urgent medical assessment [1,2,4].
People with significant immune suppression may develop larger, more persistent or more extensive HSV lesions. They should seek medical advice promptly rather than relying only on home treatment when a suspected cold sore appears.
Patients with eczema or widespread damaged skin should also avoid direct contact with an active cold sore because HSV can spread across compromised skin and cause more extensive disease. Lesions that extend beyond the usual lip area, involve the eye or fail to heal within the expected period require clinical review.
Reducing Transmission Risk
Avoiding kissing and oral sex from the first warning sensation until complete healing is the most practical way to reduce transmission during an outbreak. Patients should also avoid touching the lesion, wash their hands after applying treatment and prevent the affected area from contacting another person’s skin.
A partner should be informed before oral or sexual contact when a patient has recurrent oral or genital HSV. This allows both partners to make informed decisions about barrier protection, symptom monitoring and avoidance of contact during higher-risk periods.
Antiviral treatment may reduce lesion duration and viral shedding when used appropriately, but it does not replace contact precautions during an active episode. Similarly, individualized Ayurvedic treatment directed at recurrence, Pitta-Rakta imbalance or reduced Ojas does not make an active lesion immediately noncontagious. Transmission precautions should continue until the skin has fully healed.
Is a Cold Sore an STI?

In the cold sores vs herpes discussion, a cold sore confirms oral herpes but does not automatically mean that the infection was sexually acquired. Most cold sores are caused by HSV-1, which can spread through both nonsexual oral contact and sexual contact. Whether an HSV infection is described as sexually transmitted depends on the route of exposure and the anatomical site involved, not simply on the viral type [1,2].
Oral HSV-1 Is Often Acquired Nonsexually
Many people acquire oral HSV-1 through close oral contact during childhood, adolescence or adulthood. Infection may occur years before the first recognized cold sore, and some people never develop an obvious blister despite carrying the virus [1,2].
A person who develops a cold sore cannot determine from the lesion when HSV was acquired. The first noticeable outbreak may represent reactivation of an infection that has remained clinically silent for a long period rather than a recent exposure.
A cold sore therefore does not establish recent sexual contact, infidelity or genital infection. It also does not show that the person who most recently kissed the patient transmitted HSV. The virus may have been acquired from an earlier close contact and remained unrecognized until illness, stress, sunlight or another trigger contributed to reactivation.
The term sexually transmitted infection is more precise than sexually transmitted disease because a person may carry and transmit HSV without having active lesions or other recognized disease symptoms. However, oral HSV-1 acquired through ordinary nonsexual oral contact should not automatically be labelled an STI solely because the same virus can also be transmitted sexually [1,2].
When Oral Herpes Becomes Sexually Transmitted
Oral HSV-1 becomes sexually transmitted when it passes from the mouth to a partner’s genital or anal region during oral sex. The recipient then has genital HSV-1. The virus has not changed into HSV-2; it remains HSV-1 but is classified according to its genital location and sexual route of acquisition [2,4].
Genital HSV-1 may cause blisters, shallow ulcers, genital burning, tenderness, nerve-like discomfort or pain during urination. Some people develop only mild redness, a small fissure or symptoms that are mistaken for friction, shaving irritation, yeast infection or an ingrown hair. Others have no recognizable symptoms after exposure [2,4].
Oral contact with genital skin carrying HSV-1 or HSV-2 may also transmit infection to the mouth. Oral HSV-2 is less common than oral HSV-1, but it can occur after direct oral-genital exposure. Symptoms alone cannot reliably identify which HSV type is present.
Genital infection caused by either HSV-1 or HSV-2 is generally considered sexually transmitted when acquired through sexual contact. This is different from a childhood oral HSV-1 infection that later produces a cold sore. Both involve herpes simplex virus, but the route and site of infection are not the same [1,2].
A person with a cold sore should avoid oral sex from the beginning of tingling, burning or localized tenderness until the lesion has completely healed. Waiting until the blister becomes visible is insufficient because viral reactivation and shedding may begin during the prodromal stage [1,2,4].
Condoms and dental dams can reduce exposure during sexual contact but cannot fully prevent HSV transmission because infected skin may extend beyond the area covered by the barrier. Barrier protection should therefore be combined with avoidance of sexual contact during warning symptoms and active lesions [2,4].
What a Cold Sore Means for a Partner
A cold sore means that the affected person has an oral HSV infection, most commonly HSV-1. It does not mean that the partner already has genital herpes, but direct oral-genital contact can expose the partner to genital HSV-1.
Partners may respond differently to exposure. A person who already carries HSV-1 may have some immune recognition of the virus, but prior HSV-1 antibodies do not guarantee complete protection against infection at another site. Transmission risk depends on the type of contact, presence of symptoms, viral shedding, skin condition and individual immune factors.
Open communication is particularly important before kissing or oral sex when warning symptoms or an active lesion are present. The discussion should focus on practical risk reduction rather than blame, because a cold sore cannot reveal when or from whom the original infection was acquired.
A partner who develops a new genital blister, ulcer, burning sensation or unexplained fissure after receiving oral sex should seek assessment while the lesion is fresh. Direct testing of an active lesion is more useful than assuming that the symptoms are genital HSV-1 based only on the partner’s cold-sore history [3,4].
The absence of symptoms in the exposed partner does not confirm that transmission occurred or did not occur. Routine testing immediately after a single exposure may also be difficult to interpret because antibodies take time to develop, and HSV-1 antibody testing cannot identify whether an infection is oral or genital [3,4].
What HSV Testing Can and Cannot Establish
A lesion swab tested by PCR or another nucleic acid amplification method can confirm HSV in an active oral or genital lesion and distinguish HSV-1 from HSV-2. The result identifies the viral type present in the sampled lesion, but it does not establish the precise date of acquisition or identify the person who transmitted it [3,4].
Type-specific HSV IgG testing may show previous exposure to HSV-1 or HSV-2. A positive HSV-1 IgG result does not reveal whether the infection is located in the mouth or genitals and cannot determine whether it was acquired sexually or nonsexually [3,4].
For this reason, an HSV-1-positive blood report should not automatically be interpreted as evidence of an STI. Clinical history, lesion location, direct lesion testing and the nature of the exposure must be considered together.
HSV IgM testing should not be used to decide whether an infection is new or sexually acquired. It is not reliably type-specific and may become positive during recurrent episodes, making it unsuitable for establishing the timing or route of infection [3,4].
A patient with recurrent cold sores but no genital symptoms should not assume that genital infection is present. Similarly, a patient with genital symptoms should not assume that oral HSV-1 is the cause without direct clinical evaluation and appropriate lesion testing.
From an Ayurvedic perspective, the route of transmission does not alone define the patient’s internal disease pattern. Assessment may include the location and frequency of lesions, burning, pain, digestive strength, sleep, stress, tissue resilience and recurrence triggers. These findings can guide individualized treatment while laboratory testing establishes the virological diagnosis.
Cold Sores vs Herpes Recurrence

In cold sores vs herpes recurrence, the visible blister is only the active phase of an infection that has remained latent within sensory nerve tissue. After the initial oral infection settles, HSV travels along sensory nerves and persists in a dormant state, most commonly within the trigeminal nerve ganglion. A later episode occurs when the virus reactivates, travels back toward the skin or mucosa and begins replicating near the original site [1,4,8].
Why the Same Area Is Affected Again
Recurrent cold sores often return to the same part of the lip or nearby skin because reactivation follows an established sensory nerve pathway. The next lesion may not appear at the exact millimetre of the previous blister, but it commonly develops within the same local region supplied by the affected nerve branch [8].
This recurrence pattern helps distinguish herpes labialis from conditions that arise unpredictably at unrelated sites. Angular cheilitis may repeatedly affect the mouth corners, contact dermatitis may involve a wider area exposed to a product, and acne may occur at different hair follicles. A cold sore more often follows a familiar sequence of localized tingling, tenderness, grouped blisters, ulceration and crusting near a previously affected area.
Recurrence does not usually mean that the patient has acquired HSV again from another person. It is generally reactivation of the existing infection. A new exposure may occur, but repeated lesions in a familiar location are more commonly related to latent HSV already present within the patient’s nerve tissue [1,4].
The first noticeable cold sore may also occur long after the original infection. A patient may therefore experience an apparently new outbreak without any recent kissing, sexual contact or known exposure. The timing of the visible lesion cannot reliably establish when HSV entered the body.
Common Reactivation Triggers
Fever and other acute illnesses are common triggers, which is why recurrent lesions are often called fever blisters. Respiratory infections, influenza-like illness and periods of physical exhaustion may temporarily alter immune control and allow HSV to reactivate [6,8].
Ultraviolet exposure is another recognised trigger. Some patients develop a lesion after prolonged sun exposure, outdoor sports, skiing, beach travel or high-altitude exposure. Lip protection with an appropriate sun-protective product may help patients whose outbreaks consistently follow ultraviolet exposure.
Emotional stress can precede an outbreak in some individuals, particularly when it is accompanied by sleep loss, poor nutrition or physical fatigue. Stress is not the cause of HSV, and not every stressful event leads to a cold sore. It may, however, contribute to reactivation in a person who already carries the virus [1,8].
Local trauma may also precipitate recurrence. Dental procedures, lip injury, cosmetic treatment, shaving, friction, biting and repeated manipulation of the skin can irritate the area supplied by an affected sensory nerve. Patients who repeatedly develop lesions after dental work should inform their dentist and treating clinician before future procedures.
Hormonal changes may influence recurrence in some patients. Episodes may appear around menstruation or during periods of significant endocrine change, but the relationship is not uniform. A lesion occurring near menstruation should not automatically be attributed to hormones without considering other triggers and alternative diagnoses.
Cold weather, wind exposure, dehydration and severe lip dryness may contribute indirectly by damaging the skin barrier or increasing local irritation. These factors do not generate HSV, but they may coincide with reactivation or make an early lesion more symptomatic.
Some outbreaks occur without an identifiable trigger. Patients should not assume that every recurrence resulted from a dietary mistake, stressful thought or single behaviour. HSV reactivation reflects an interaction between viral biology, local nerve activity and host immune control, and the exact trigger may remain unclear.
Why Recurrence Frequency Differs
Some patients develop one cold sore and have no further recognised episodes. Others experience occasional outbreaks separated by months or years, while a smaller group has frequent recurrences. The number of episodes depends on viral type, infection site, immune status, individual susceptibility and exposure to personal triggers [1,4,8].
Oral HSV-1 is well adapted to the oral region and commonly causes recurrent herpes labialis. Oral HSV-2 is less likely to produce frequent oral recurrences. In the genital region, HSV-2 generally recurs and sheds more often than genital HSV-1. These patterns explain why both the viral type and the anatomical site are important when discussing prognosis [2,4].
A recurrence may also become less severe over time. Later episodes are often smaller, more localized and shorter than the initial infection because the immune system already recognises the virus. This pattern is common but not universal. Some patients continue to experience painful or disruptive episodes despite having carried HSV for many years.
Frequent or unusually severe recurrence may be associated with immune suppression, serious systemic illness, certain medicines, poorly controlled chronic disease or significant physical stress. It does not prove that one of these conditions is present, but repeated extensive lesions deserve clinical review rather than repeated self-treatment.
Patients receiving chemotherapy, organ-transplant medicines, prolonged corticosteroid treatment or other immunosuppressive therapy may develop larger, slower-healing or atypical HSV lesions. Clinical assessment should occur promptly when lesions spread beyond the usual area, become deeply ulcerated or fail to heal within the expected period [1,4].
When Recurrent Symptoms May Not Be HSV
Not every episode of lip tingling, redness or burning represents herpes reactivation. Contact allergy, perioral dermatitis, dry skin, nerve irritation, dental disease, angular cheilitis and recurrent trauma may produce symptoms in the same general area.
A patient who has previously had a confirmed cold sore may later develop an unrelated lesion. Past HSV infection should not be used to label every future lip symptom as herpes. A change in location, appearance, duration or response to treatment should prompt reassessment.
Persistent burning between outbreaks is less typical of an uncomplicated cold sore pattern. Continuous symptoms may require evaluation for neuropathic pain, irritant exposure, oral disease, nutritional deficiency or another dermatological condition.
Repeatedly applying antiviral medicine to every unexplained sensation may delay recognition of a different disorder. When possible, a fresh atypical lesion should be examined and directly tested before long-term treatment decisions are made.
Monitoring the Recurrence Pattern
Recording each episode can help identify whether a reproducible pattern exists. Useful details include the date, exact location, warning symptoms, lesion appearance, possible trigger, healing time and treatment used. Early photographs may provide additional clinical information because the lesion can change considerably before an appointment.
A recurrence diary may reveal that episodes consistently follow intense sunlight, fever, dental procedures or sleep deprivation. It may also show that some suspected outbreaks never develop blisters and may represent a different condition.
The clinical significance of recurrence depends on more than the number of lesions. Pain, healing time, interference with eating, effects on relationships, transmission concerns and impact on daily life should also be considered. Two severe episodes may require more attention than several minor lesions that heal quickly.
Patients with frequent recurrences should also be asked about genital symptoms, eye symptoms, eczema, pregnancy, immune suppression and medicines that affect immune function. These factors may alter the urgency of evaluation and the most appropriate treatment plan.
Ayurvedic Assessment of Recurrence
Ayurvedic assessment considers why the patient repeatedly enters a state in which burning, blistering and inflammation reappear. The evaluation may include Pitta-Rakta aggravation, digestive disturbance, sleep loss, emotional strain, tissue depletion and reduced Ojas, together with the frequency, site and stage of each outbreak.
The recurrence pattern may differ between patients even when both have laboratory-confirmed HSV-1. One patient may relapse after sun exposure and overheating, while another may relapse after fever, exhaustion or disturbed sleep. Treatment should therefore be based on the complete clinical pattern rather than the virus name alone.
Acute care focuses on the current lesion, whereas recurrence-focused care examines the factors associated with repeated reactivation and the patient’s overall resilience between episodes. Ayurvedic treatment planning should remain individualized and should not replace lesion testing when the diagnosis is uncertain or the presentation has changed.
Cold Sores vs Herpes Testing
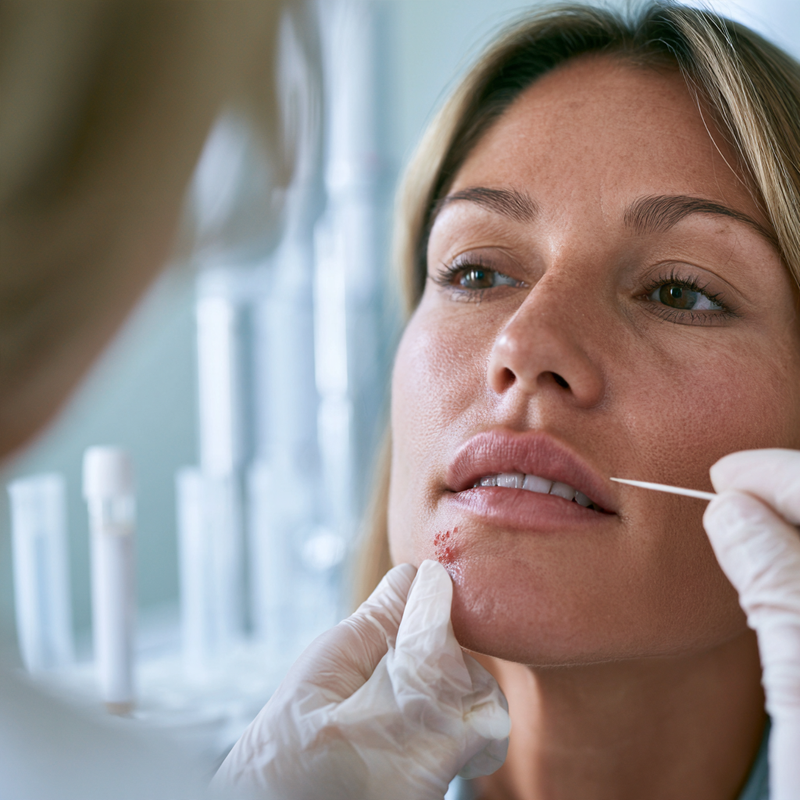
Cold sores vs herpes testing should be selected according to the clinical question. A lesion test can determine whether an active blister or ulcer contains HSV and identify the viral type, while an antibody test can indicate previous exposure. No single test can simultaneously establish the infection site, acquisition date, transmission source, current contagiousness and long-term recurrence risk [3–5].
Clinical Examination
A familiar recurrent cold sore may be recognised clinically when it begins with localized tingling or burning, develops into grouped blisters near the lip border and heals through ulceration and crusting. The repeated appearance of a similar lesion in the same region further supports recurrent herpes labialis [8].
Clinical appearance alone becomes less reliable when the lesion is inside the mouth, has already crusted, consists of only a fissure or resembles angular cheilitis, impetigo, acne, contact dermatitis or a canker sore. Genital HSV can also present as redness, shallow erosions or small cuts rather than typical grouped blisters [4,5].
Testing is particularly useful for a first recognised outbreak, an atypical lesion, unexplained oral and genital symptoms, a severe or slow-healing episode, possible exposure during pregnancy, immune suppression or a diagnosis that would materially affect a partner. A fresh lesion should be sampled before creams, repeated cleaning or natural healing substantially alters its surface.
A photograph can document the original appearance but cannot confirm HSV. Image-based assessment may help determine urgency, yet laboratory examination of lesion material is more reliable when the distinction between HSV and another blistering or ulcerative disorder remains uncertain.
Lesion PCR
HSV polymerase chain reaction, also called a nucleic acid amplification test, is the preferred direct test when a fresh blister or ulcer is available. The swab is collected from the lesion itself and analysed for HSV genetic material. Type-specific testing can distinguish HSV-1 from HSV-2, providing information that may influence counselling about recurrence and transmission [4,5].
The sample should be collected as early as possible, ideally from a fresh vesicle or newly formed ulcer. Detectable virus becomes less abundant as a lesion dries and heals, so a swab taken after substantial crusting may be less sensitive than one taken during the blister or early ulcer stage [4,5].
A positive lesion PCR confirms that HSV was present at the sampled anatomical site. HSV-1 detected from a lip lesion confirms oral HSV-1, while HSV-1 detected from a genital lesion confirms genital HSV-1. The result does not reveal when the infection was acquired, whether the sampled episode was the first infection or a recurrence, or which person transmitted it.
A negative lesion PCR does not always exclude HSV. The result may be negative when the lesion is old, the surface has healed, insufficient material was collected or viral shedding has already declined. Reassessment during a future fresh episode may be more informative when the clinical pattern remains strongly suggestive [4,5].
A swab collected from normal skin when no lesion is present is generally not a reliable way to exclude genital HSV. Shedding is intermittent, so a negative random swab only indicates that HSV was not detected at that site and moment. It does not establish that the person has never acquired HSV [4].
Viral Culture
Viral culture can identify HSV from lesion material when PCR is unavailable. It can also distinguish HSV-1 from HSV-2 when appropriate typing is performed. However, culture is less sensitive than PCR, particularly for recurrent lesions and samples collected after healing has begun [4,5].
A negative culture from a crusted or partially healed lesion should therefore be interpreted cautiously. It should not automatically override a characteristic recurrence history or a later positive type-specific test.
Culture has an additional role when a lesion persists or recurs despite correctly prescribed antiviral treatment and antiviral resistance is suspected. In that situation, growth of the virus may allow phenotypic susceptibility testing. Resistance assessment is not routinely required for an uncomplicated cold sore that heals normally [4,5].
Type-Specific HSV IgG
Type-specific HSV IgG is a blood antibody test that evaluates previous immune exposure to HSV-1 or HSV-2. Antibodies usually develop during the weeks following infection and may remain detectable long term. An IgG result should therefore be interpreted as evidence of previous exposure rather than a direct measurement of current lesion activity or viral load [3,4].
A positive HSV-1 IgG result cannot determine whether HSV-1 is located orally or genitally. Because oral HSV-1 is common and may have been acquired without recognised symptoms, a positive blood result cannot prove that a current lip, mouth or genital lesion is caused by HSV-1 [3,4].
A positive HSV-2 IgG result is more suggestive of anogenital infection because HSV-2 is predominantly sexually acquired. It still cannot establish the infection date, identify the transmitting partner or show whether viral shedding is occurring at the time of testing [4].
IgG testing may be useful when genital symptoms are recurrent or atypical but lesion PCR or culture is negative, when genital herpes was diagnosed clinically without laboratory confirmation, or when a sexual partner has confirmed genital herpes. Its value is more limited for a patient with a classic recurrent cold sore because HSV-1 serology cannot confirm that the antibodies originated from the oral site [3,4].
Testing performed too soon after a suspected new infection may be negative because antibodies have not yet reached detectable levels. When recent acquisition remains a concern, repeat type-specific testing at approximately twelve weeks may be considered rather than treating an early negative result as final [4].
Low-positive HSV-2 results from some enzyme immunoassays can be false positive. A second test using a different method may be required before a lifelong diagnosis is assigned. The numerical index value, assay used, exposure history and presence or absence of compatible symptoms should all be reviewed before interpretation [3,4].
Changes in the numerical IgG value should not be used alone to measure outbreak severity, current contagiousness or treatment response. The antibody index is not a direct count of HSV particles and is not interchangeable with viral-load testing.
Why HSV IgM Is Not Recommended
HSV IgM should not be used to decide whether an oral or genital infection is recent. Available IgM assays are not reliably type-specific and may react during recurrent episodes as well as initial infection. A positive result therefore cannot reliably distinguish HSV-1 from HSV-2 or establish when exposure occurred [4].
An IgM result can create unnecessary confusion when it is interpreted as proof of a new infection or recent partner transmission. Current diagnostic guidance does not recommend HSV IgM for routine oral or genital herpes assessment [4].
When a patient has a new lesion, direct PCR testing of that lesion is more clinically useful. When no lesion is available and the purpose is to evaluate prior exposure, an appropriately selected type-specific IgG test may provide more relevant information.
Blood PCR and Latent HSV
HSV DNA PCR performed on blood is not the routine test for an uncomplicated cold sore, recurrent oral herpes or localized genital herpes. Localized mucocutaneous HSV is best assessed by testing material from the active lesion rather than looking for viral DNA in the bloodstream [5].
Blood PCR may be considered when disseminated HSV, severe systemic infection, neonatal herpes or visceral involvement is suspected. These situations are clinically different from an otherwise localized lip or genital lesion [5].
A negative blood PCR does not exclude oral or genital HSV because localized infection may not produce detectable circulating viral DNA. It also cannot demonstrate that latent HSV is absent from sensory nerve ganglia. Blood PCR should therefore not be presented as the most accurate routine method for detecting dormant oral or genital HSV [5].
A positive blood PCR requires prompt clinical interpretation because it may indicate systemic viral involvement rather than an ordinary localized recurrence. The significance depends on age, immune status, symptoms and the reason the test was ordered.
PCR testing of other specimens serves different purposes. Cerebrospinal-fluid PCR is used when HSV infection of the central nervous system is suspected, while ocular disease requires ophthalmological assessment and specimen selection according to the structures involved. These tests should not be substituted for lesion PCR in an uncomplicated cold sore [5].
Interpreting Positive and Negative Results
A positive lesion PCR answers a focused question: HSV genetic material was present in the sampled lesion. It also identifies the type when type-specific analysis is performed. It does not determine how long the infection has been present or predict exactly how often future outbreaks will occur.
A negative lesion PCR means HSV was not detected in that specimen. Interpretation depends on the lesion’s age, specimen quality and clinical pattern. A negative result from an early, adequately sampled blister carries more diagnostic weight than a negative result from a dry lesion collected near the end of healing [4,5].
A positive HSV-1 IgG result indicates previous exposure but cannot locate the infection. A patient may have longstanding asymptomatic oral HSV-1 while a current genital lesion has another cause. Conversely, a patient with genital HSV-1 may have no history of cold sores.
A negative IgG result after a very recent exposure may reflect the antibody-development window rather than absence of infection. A later repeat test may be appropriate when the exposure was significant and no active lesion was available for direct testing [3,4].
Neither a negative blood PCR nor a negative swab from normal skin establishes that latent HSV has been eliminated. Similarly, persistence of IgG does not by itself prove that active viral replication or an outbreak is occurring. Each result must be interpreted according to the biological process the test measures.
Testing After Treatment
Follow-up testing should be selected for a specific clinical reason rather than repeated automatically. A patient whose lesion heals as expected may not benefit from repeated lesion swabs after the skin has returned to normal because there is no active lesion to sample.
IgG values are not routinely used as a short-term treatment-response marker. Antibodies may remain detectable after symptoms improve, and fluctuations in the reported index do not directly measure the amount of latent or replicating HSV [3,4].
When symptoms continue despite a negative lesion result, reassessment should include alternative diagnoses rather than repeating only the same HSV blood tests. Depending on the presentation, other possibilities may include aphthous ulceration, bacterial infection, fungal disease, contact dermatitis, varicella-zoster infection, inflammatory disease or another cause of oral or genital ulceration.
Persistent lesions during correctly administered antiviral therapy require evaluation of adherence, immune status, lesion diagnosis and possible resistance. A repeat lesion sample, viral culture and susceptibility testing may be considered in selected patients rather than assuming that every persistent ulcer reflects ordinary recurrent HSV [4,5].
Ayurvedic treatment planning should use laboratory findings together with the lesion pattern, recurrence history, digestive health, sleep, stress, associated illness and medicine use. Clinical improvement, recurrence frequency and appropriately selected tests should be reviewed according to their individual purpose. A laboratory result should not be interpreted outside the type of specimen tested or the biological question it can answer.
Cold Sores vs Herpes: When to Seek Care

In cold sores vs herpes, most recurrent lip lesions heal without complications, but certain symptoms require prompt medical assessment. The urgency depends on the lesion’s location, severity, duration, associated symptoms, age, pregnancy status and immune health. A first severe outbreak, an uncertain diagnosis or a lesion that behaves differently from previous episodes should not be managed repeatedly as an ordinary cold sore without clinical review [1,5,6,8].
Eye Symptoms
HSV can affect the eyelid, conjunctiva or cornea. Eye involvement requires urgent assessment because inflammation or ulceration of the cornea can impair vision if treatment is delayed [5,6].
Eye pain, redness, excessive tearing, light sensitivity, blurred vision, eyelid blisters or a sensation that something is trapped in the eye should not be treated with ordinary cold-sore creams. The patient should avoid touching or rubbing the eye and should seek same-day medical or ophthalmological assessment.
A cold sore near the eye does not prove that the cornea is infected, but the risk is greater when the lesion involves the eyelid or when visual symptoms are present. Contact lenses should not be worn until the eye has been examined and the symptoms have resolved.
Topical corticosteroid eye drops should not be started without an ophthalmologist’s direction. Corticosteroids can worsen some forms of active ocular HSV when used without appropriate antiviral treatment and clinical monitoring [5].
Patients should wash their hands after touching the mouth or applying medicine to a cold sore. Makeup applicators, eye products and contact-lens equipment that may have contacted an active lesion should not be shared.
Newborns and Young Children
A person with tingling, an active cold sore or a recently healing lesion should not kiss a newborn. Neonatal HSV can cause localized skin disease, neurological infection or disseminated infection involving several organs. Early symptoms may be subtle, and visible blisters are not always present at the beginning [1,2,5].
A newborn who may have been exposed to an active cold sore requires prompt pediatric advice. Blisters, fever, poor feeding, unusual sleepiness, irritability, breathing difficulty or reduced responsiveness require urgent medical assessment rather than home treatment.
Parents and caregivers should wash their hands before touching a newborn, particularly after applying medicine to an oral lesion. The cold sore should be covered when practical, and direct contact between the lesion and the infant’s skin should be prevented until complete healing.
A first oral HSV infection in an older infant or child may cause extensive mouth ulcers, swollen and painful gums, fever, drooling and refusal to eat or drink. The immediate concern is often dehydration rather than the visible sores alone [6].
Reduced urination, a dry mouth, absence of tears, marked lethargy or inability to retain fluids requires prompt medical review. Pain control and hydration support may be necessary even when the oral lesions are expected to heal.
Children who suck their fingers or touch an oral lesion may transfer HSV to damaged skin around a finger. Painful swelling or grouped blisters around the fingertip should be medically assessed because herpetic whitlow can resemble a bacterial nail infection and should not be cut or drained without diagnosis.
Severe or Spreading Lesions
Medical review is needed when blisters or ulcers spread rapidly beyond the usual lip area, become unusually large, involve extensive areas inside the mouth or cause severe pain. Widespread disease is more concerning in patients with impaired immunity or damaged skin barriers [1,5].
People receiving chemotherapy, transplant medicines, prolonged systemic corticosteroids or other immune-suppressing treatments may develop persistent, extensive or atypical HSV lesions. Patients living with advanced immune deficiency may also have lesions that heal slowly or extend into deeper tissues [1,5].
A patient with immune suppression should contact the treating clinician promptly when a suspected cold sore appears rather than waiting for the episode to become severe. Early antiviral assessment may reduce the risk of prolonged disease or wider tissue involvement.
Patients with eczema or extensive inflamed skin require particular caution if clusters of painful blisters begin spreading across affected areas. Rapidly spreading lesions accompanied by fever, weakness or increasing pain require urgent clinical evaluation.
Increasing redness, warmth, swelling, pus, worsening tenderness or fever after a blister has ruptured may indicate secondary bacterial infection. These changes are different from the ordinary drying and crusting phase of a cold sore and may require additional treatment.
Severe headache, altered behaviour, confusion, seizure, neck stiffness or reduced consciousness is not part of an uncomplicated cold-sore outbreak. These symptoms require emergency assessment, particularly when accompanied by fever or immune suppression [5].
Persistent or Unusual Lesions
A typical recurrent cold sore usually shows clear improvement and heals within approximately one to two weeks. A lesion that continues enlarging, repeatedly bleeds, remains ulcerated or fails to heal within the expected period requires reassessment [6,8].
A persistent lip or oral ulcer should not be assumed to be herpes solely because the patient has a history of HSV-1. Trauma, bacterial infection, fungal disease, contact dermatitis, inflammatory disorders and other oral or dermatological conditions may produce a similar appearance.
A lesion that feels hard, develops an irregular border, repeatedly recurs without a typical blister stage or remains present for more than two weeks deserves direct examination. Repeated antiviral treatment without confirming the diagnosis may delay identification of another condition.
Testing is also appropriate when the current episode differs from previous cold sores. A lesion in a new location, an unusually long prodromal phase, continuous pain between outbreaks or multiple ulcers with no grouped blister stage may indicate a different disorder.
When a fresh blister or ulcer is available, lesion PCR or another nucleic acid amplification test can help confirm HSV and identify the viral type. A lesion should ideally be sampled before it has dried, crusted or substantially healed [4,5].
Frequent or Disruptive Recurrence
Clinical review is appropriate when outbreaks become more frequent, more painful or slower to heal than the patient’s previous pattern. A sudden increase in recurrence may accompany acute illness, immune suppression, severe physical stress or a change in medication.
The need for treatment should not be judged only by the number of outbreaks. Episodes that interfere with eating, work, sleep, relationships or sexual contact may justify a preventive treatment discussion even when they occur only a few times each year.
Patients should record the date, exact location, warning symptoms, lesion duration, possible trigger and treatment response. This history helps distinguish true recurrent herpes from repeated episodes of cheilitis, dermatitis, acne, aphthous ulceration or neuropathic discomfort.
Suppressive antiviral therapy may be considered when confirmed outbreaks are frequent or substantially affect quality of life. The decision should consider recurrence pattern, renal health, other medicines, pregnancy status and the patient’s individual risk of transmission [4,8].
Repeated episodes attributed to HSV without visible lesions should be reassessed. Persistent tingling, burning or lip sensitivity between outbreaks may arise from contact allergy, dryness, local nerve irritation, dental problems or another condition requiring different treatment.
Pregnancy and Genital Symptoms
An isolated recurrent cold sore during pregnancy does not automatically mean that the fetus has genital HSV exposure. The greater obstetric concern is a new genital HSV infection during pregnancy, particularly when acquisition occurs near delivery [1,2,4].
A pregnant patient who develops new genital blisters, ulcers, burning, fissures or pain during urination should contact the obstetric clinician promptly. Direct testing of a fresh lesion can determine whether HSV is present and whether it is HSV-1 or HSV-2.
A pregnant patient whose partner has oral or genital herpes should discuss exposure prevention with the obstetric clinician. Oral sex should be avoided when a partner has a cold sore or warning symptoms, because oral HSV-1 can be transmitted to the genital region.
A history of genital herpes should be disclosed to the maternity team even when no lesions are present. Management near delivery depends on the timing of infection, recurrence history, current symptoms and examination findings [2,4].
After delivery, a parent or visitor with an active cold sore should not kiss the newborn. Careful hand hygiene and prevention of direct lesion contact remain necessary until the sore has fully healed.
Ayurvedic assessment may continue after urgent causes and complications have been excluded. Acute eye symptoms, neonatal exposure, extensive disease, dehydration, pregnancy-related genital lesions and severe immune suppression require appropriate medical evaluation before routine recurrence-focused Ayurvedic treatment is planned.
Cold Sores vs Herpes Treatment

Cold sores vs herpes treatment depends on whether the episode is a first infection, a familiar recurrence, an oral or genital presentation, and whether the patient has pregnancy, kidney disease, immune suppression or eye involvement. Modern treatment mainly aims to limit viral replication during an active episode, shorten healing time, reduce pain, decrease recurrence frequency and lower transmission risk when clinically indicated [4,5,8].
Early Episodic Treatment
Antiviral treatment is most effective when started during the prodromal stage, when tingling, burning, itching or localized tenderness begins, or soon after the first blister appears. Waiting until the lesion has fully ulcerated or crusted may reduce the benefit because viral replication is greatest during the earlier stages of the outbreak [4,8,9].
Oral antiviral medicines used for HSV include acyclovir, valacyclovir and famciclovir. These medicines interfere with viral DNA replication and may shorten lesion duration, reduce pain and accelerate healing when the diagnosis is correct and treatment begins early [4,5,8].
The prescribed regimen differs according to whether the patient has recurrent herpes labialis, a first oral infection, genital HSV-1, genital HSV-2 or extensive disease. A treatment schedule intended for a recurrent cold sore should not be applied automatically to a first severe oral or genital episode.
Patients who experience a consistent warning phase may be advised to keep their prescribed episodic medicine available so that treatment can begin promptly. The medicine should still be used according to the clinician’s instructions rather than started for every episode of unexplained lip tingling, because dermatitis, dryness, dental irritation and nerve sensitivity may produce similar symptoms.
Topical antiviral medicines, including acyclovir or penciclovir preparations, may provide a modest reduction in symptom duration when applied very early and at the recommended frequency. Their benefit is generally smaller than that of appropriately selected oral treatment, particularly when the episode is extensive or treatment begins after ulceration [8,9].
Docosanol is another topical option for uncomplicated recurrent cold sores. It may modestly shorten healing when started at the earliest symptoms, but it does not replace clinical assessment when lesions are severe, atypical, near the eye or slow to heal [8].
Topical treatment should be applied with clean hands or a disposable applicator. Vigorous rubbing, repeated removal of crusts and sharing the medicine container with another person should be avoided.
A patient who begins treatment early but continues to develop unusually extensive lesions should be reassessed. The episode may represent a first infection, bacterial superinfection, an alternative diagnosis, immune suppression or an HSV strain requiring further evaluation.
Suppressive Treatment
Daily suppressive antiviral treatment may be considered when laboratory-confirmed outbreaks are frequent, painful, prolonged or substantially disruptive. The decision should consider recurrence frequency, lesion severity, effects on work and relationships, transmission concerns, kidney function, other medicines and the patient’s treatment preference [4,5].
Suppressive treatment can reduce the number of symptomatic outbreaks and decrease asymptomatic viral shedding. It does not make transmission impossible, so patients should continue to avoid kissing or sexual contact during warning symptoms and active lesions [4].
The clinical value of suppression should be reviewed periodically. Some patients experience fewer recurrences over time and may no longer require continuous treatment, while others continue to benefit because outbreaks return when treatment is stopped.
A recurrence after stopping suppressive medicine does not mean that the medicine has driven HSV deeper into the body or weakened natural immunity. It usually reflects reactivation of the pre-existing latent infection after the antiviral effect is withdrawn.
Suppressive treatment may also be considered when recurrent disease causes significant anxiety, interferes with intimacy or leads to repeated uncertainty about transmission. Psychological burden is clinically relevant even when the visible lesions are small.
For genital HSV-2, daily antiviral suppression may reduce recurrence and transmission risk in selected patients. Genital HSV-1 usually recurs and sheds less frequently, so long-term suppression is reserved for patients with repeated or clinically important recurrences [4].
Treatment decisions for oral herpes should remain separate from treatment decisions for genital herpes. A patient who occasionally develops a small cold sore may not require the same long-term approach as someone with frequent genital HSV-2 outbreaks.
Symptom Relief and Lesion Care
A cool compress may reduce local burning, swelling and discomfort during an active cold sore. A bland protective lip preparation can help prevent excessive cracking, particularly during the crusting stage.
Appropriate nonprescription pain relief may be used when medically suitable. Patients with kidney disease, liver disease, stomach ulceration, anticoagulant use, pregnancy or medicine allergies should confirm which analgesic is appropriate before self-treatment.
Patients with painful sores inside the mouth may benefit from adequate fluid intake, soft foods and avoidance of very hot, acidic, salty or sharply textured foods that repeatedly irritate the ulcerated surface. Reduced drinking is particularly concerning in children because dehydration can develop before the oral lesions have healed.
The lesion should be kept clean without aggressive scrubbing. Alcohol, hydrogen peroxide, strong acids, concentrated essential oils and caustic home applications can damage healing tissue, increase pain and prolong inflammation.
A cold sore should not be punctured, squeezed or repeatedly peeled. Disrupting the lesion can cause bleeding, bacterial contamination and delayed healing without removing the underlying HSV infection.
Temporary crusting is part of the normal healing process. A crust that splits while eating or speaking may be protected with a bland emollient, but increasing redness, pus, warmth, swelling or worsening pain may indicate secondary bacterial infection.
Local anaesthetic preparations may provide temporary pain relief, but repeated or excessive use can irritate the area or numb the mouth enough to interfere with safe eating. Products should be used according to their instructions and avoided in young children unless specifically recommended.
Safety and Special Situations
Acyclovir, valacyclovir and famciclovir are generally well tolerated when appropriately prescribed, but dose selection must account for kidney function. Reduced renal clearance can cause medicine accumulation, particularly in older adults, dehydrated patients and people with pre-existing kidney impairment [4,5].
Possible adverse effects include headache, nausea and gastrointestinal discomfort. Kidney injury or neurological symptoms are uncommon but may occur when doses are excessive for the patient’s renal function, hydration is poor or significant drug accumulation develops.
New confusion, unusual drowsiness, tremor, agitation or reduced urine output after starting antiviral treatment requires prompt medical review. These symptoms should not be assumed to be part of an ordinary cold-sore episode.
Pregnant patients should not discontinue or start antiviral treatment solely on internet advice. Acyclovir has extensive clinical experience in pregnancy, but the indication, timing and regimen should be determined by the obstetric or treating clinician, particularly when genital lesions or a new infection are suspected [4].
Treatment of infants and young children requires weight-appropriate prescribing and assessment of hydration. Adult tablets, doses or topical products should not be adapted for a child without paediatric guidance.
Patients receiving chemotherapy, transplant medicines, systemic corticosteroids or other immune-suppressing treatments may require earlier or longer antiviral therapy. Persistent lesions in these patients may also need direct testing, culture and specialist review [5].
Antiviral resistance is uncommon in immunocompetent patients but is more clinically relevant in severe immune suppression. A lesion that persists or progresses despite correctly administered treatment should prompt confirmation of the diagnosis, review of adherence and consideration of resistance rather than automatic escalation of unsupervised medicine [4,5].
Corticosteroid creams should not be applied alone to a suspected HSV lesion without clinical guidance. Eye drops containing corticosteroids require ophthalmological supervision when ocular HSV is possible because inappropriate use can worsen corneal disease.
Treatment Goals and Limitations
Standard antiviral medicines act mainly while HSV is actively replicating. They do not directly remove latent viral material from sensory nerve ganglia, where HSV persists between clinically recognised outbreaks [4,5,8].
A successful episodic treatment may shorten the current outbreak without preventing every future recurrence. A successful suppressive regimen may reduce outbreaks and shedding while it is being used, but the patient’s underlying recurrence pattern may become apparent again after treatment is discontinued.
Healing of a lesion does not establish that every future lip symptom will be HSV. Persistent burning, scaling, cracking or tenderness after the expected healing period should prompt evaluation for dermatitis, angular cheilitis, bacterial infection, neuropathic symptoms or another oral condition.
Treatment response alone should not be used to confirm the diagnosis. A lesion may improve naturally over the same period in which a medicine is taken, while non-herpetic inflammatory lesions may temporarily improve because of protective topical care.
Patients with recurrent disease require follow-up based on outbreak frequency, symptom severity, healing time, treatment dependence, transmission concerns and the accuracy of the original diagnosis. Laboratory investigations should be repeated only when they answer a defined clinical question rather than being used as interchangeable measures of viral activity.
Ayurvedic treatment may be planned after the HSV diagnosis, disease site, recurrence pattern, digestive health, sleep, stress, medicine use and safety factors have been assessed. Acute antiviral treatment should not be delayed when the patient has ocular symptoms, neonatal exposure, extensive disease, severe immune suppression or a clinically significant first episode.
Cold Sores vs Herpes in Ayurveda

Cold sores vs herpes are interpreted in Ayurveda through the lesion stage, symptom quality, recurrence pattern, digestive function, sleep, stress, physical resilience and anatomical site. Classical Ayurvedic texts predate the identification of HSV-1 and HSV-2; therefore, they do not contain a disease name that can be treated as an exact synonym for herpes simplex infection. Modern examination and lesion testing establish the viral diagnosis, while Ayurvedic assessment identifies the individual Dosha-Dushya pattern that guides treatment [3,4].
Dosha refers to the functional principles of Vata, Pitta and Kapha. Dushya refers to the tissues affected during disease. Rakta denotes blood tissue, Tvak denotes skin, Lasika denotes tissue fluid, Mamsa denotes flesh or muscular tissue, Agni denotes digestive and metabolic capacity, and Ojas denotes systemic vitality and resilience. These concepts describe the Ayurvedic clinical pattern and are not substitutes for HSV type, antibody status, viral DNA or immune-system investigations.
Classical Diagnostic Framework
Charaka describes Visarpa according to its characteristic tendency to spread:
Sanskrit
विविधं सर्पति यतो विसर्पस्तेन स स्मृतः ।
परिसर्पोऽथवा नाम्ना सर्वतः परिसर्पणात् ॥११॥
Transliteration
vividhaṃ sarpati yato visarpastena sa smṛtaḥ |
parisarpo’thavā nāmnā sarvataḥ parisarpaṇāt ||11||
Translation
It is called Visarpa because it spreads in different directions. It is also called Parisarpa because of its tendency to spread extensively.
Text reference: Charaka Samhita, Chikitsa Sthana, Chapter 21, Visarpa Chikitsa, Verse 11 [10].
This verse defines Visarpa by rapid or extensive spreading. A recurrent cold sore, however, often remains localized to a small region of the lip and returns through the same sensory nerve distribution. It should not be labelled Visarpa merely because it forms blisters, burns or recurs. Visarpa principles become clinically relevant only when the presentation shows comparable features such as marked inflammation, redness, swelling, blistering or extension across surrounding tissue.
Visphota, Sphota and Vrana may also provide useful descriptive concepts for blistering, ruptured lesions and ulceration, but these terms describe morphology rather than a specific virus. They cannot determine whether a lesion is caused by HSV, a bacterial infection, contact dermatitis, aphthous ulceration or another condition. A fresh lesion swab for PCR or another nucleic acid amplification test remains more reliable when virological confirmation is required [3,4].
A patient with a familiar recurrent blister at the lip border may present with a limited Pitta-Rakta pattern, while widespread oral ulceration with fever and inflamed gums requires a different assessment. Genital lesions, eye symptoms, extensive eruptions and lesions in an immunocompromised patient also require site-specific medical evaluation rather than treatment based only on a classical skin-disease category.
Dosha and Tissue Pattern
Charaka identifies the principal tissues and Doshas involved in Visarpa:
Sanskrit
रक्तं लसीका त्वङ्मांसं दूष्यं दोषास्त्रयो मलाः ।
विसर्पाणां समुत्पत्तौ विज्ञेयाः सप्त धातवः ॥१५॥
Transliteration
raktaṃ lasīkā tvaṅmāṃsaṃ dūṣyaṃ doṣāstrayo malāḥ |
visarpāṇāṃ samutpattau vijñeyāḥ sapta dhātavaḥ ||15||
Translation
Rakta, Lasika, Tvak and Mamsa are the affected tissues, while Vata, Pitta and Kapha are the three vitiated Doshas. These seven factors should be understood in the development of Visarpa.
Text reference: Charaka Samhita, Chikitsa Sthana, Chapter 21, Visarpa Chikitsa, Verse 15 [10].
This tissue framework is relevant when assessing the visible and sensory features of an inflammatory blistering disorder. Tvak involvement is reflected by redness, blistering, fissuring or crusting. Rakta involvement may be considered when heat, marked erythema and inflammatory sensitivity predominate. Lasika involvement may be considered when swelling, moistness or clear discharge is present. Deeper pain, induration or tissue damage requires assessment beyond a superficial skin interpretation.
Pitta predominance is considered when the lesion is hot, red, burning, tender and rapidly inflammatory. Rakta association becomes more relevant when redness, heat and vascular inflammatory features are prominent. Vata involvement may appear as tingling, pricking, dryness, fissuring, twitching or sharp pain. Kapha involvement may be considered when swelling, heaviness, pale coloration, thick discharge or slow resolution predominates.
These patterns may coexist. A lesion can begin with Vata-associated tingling, progress to Pitta-Rakta-associated burning and redness, and later develop dryness and cracking during healing. Treatment selection should therefore follow the current stage rather than applying the same local or internal medicine throughout the entire outbreak.
Charaka describes the inflammatory behaviour of aggravated Pitta as follows:
Sanskrit
पित्तमुष्णोपचारेण विदाह्यम्लाशनैश्चितम् ।
दूष्यान् सन्दूष्य धमनीः पूरयन् वै विसर्पति ॥३१॥
Transliteration
pittam uṣṇopacāreṇa vidāhyamlāśanaiś citam |
dūṣyān sandūṣya dhamanīḥ pūrayan vai visarpati ||31||
Translation
Pitta accumulated through heating regimens and burning or sour foods vitiates the susceptible tissues, fills the channels and spreads.
Text reference: Charaka Samhita, Chikitsa Sthana, Chapter 21, Visarpa Chikitsa, Verse 31 [10].
This verse supports assessment of a heat-dominant inflammatory presentation. It does not mean that sour, spicy or heating foods create HSV infection. HSV is acquired through viral transmission, while food and environmental factors may aggravate local burning, digestive disturbance or an existing Pitta-dominant symptom pattern in susceptible patients.
A patient whose active oral lesion burns intensely may temporarily tolerate bland, soft and non-irritating food better than acidic, very salty or sharply spiced food. This is intended to reduce irritation of damaged tissue. It does not justify imposing the same permanent dietary restriction on every patient with HSV.
Agni and Recurrence Triggers
Charaka includes disturbed eating patterns, indigestion, daytime sleep and injury among the factors considered in inflammatory spreading disorders:
Sanskrit
प्रक्लिन्नानामसात्म्यानां विरुद्धानां च सेवनात् ।
अत्यादानाद्दिवास्वप्नादजीर्णाध्यशनात् क्षतात् ॥२०॥
Transliteration
praklinnānām asātmyānāṃ viruddhānāṃ ca sevanāt |
atyādānād divāsvapnād ajīrṇādhyāśanāt kṣatāt ||20||
Translation
Among the causative factors are the consumption of spoiled, unsuitable or incompatible foods, overeating, daytime sleep, eating during indigestion, eating before the previous meal has been digested and physical injury.
Text reference: Charaka Samhita, Chikitsa Sthana, Chapter 21, Visarpa Chikitsa, Verse 20 [10].
Agni is assessed through appetite, digestion, bowel regularity, post-meal heaviness, bloating, food tolerance and general energy. Digestive disturbance should not be assumed merely because HSV recurs. A patient with stable appetite, comfortable digestion and normal bowel function may not require intensive Agni-directed treatment.
When recurrences coexist with persistent indigestion, irregular eating, bloating, constipation, loose stools or poor medicine tolerance, correction of digestion becomes clinically relevant. Improving Agni may support nutrition, medicine absorption and general recovery, but it does not replace direct management of an active viral lesion.
The classical text also indicates that disease may arise through the combined effect of several aggravating factors:
Sanskrit
एतैर्निदानैर्व्यामिश्रैः कुपिता मारुतादयः ।
दूष्यान् सन्दूष्य रक्तादीन् विसर्पन्त्यहिताशिनाम् ॥२२॥
Transliteration
etair nidānair vyāmiśraiḥ kupitā mārutādayaḥ |
dūṣyān sandūṣya raktādīn visarpanty ahitāśinām ||22||
Translation
Through a combination of these causative factors, Vata and the other Doshas become aggravated, vitiate susceptible tissues beginning with Rakta and produce a spreading disorder in those following an unwholesome regimen.
Text reference: Charaka Samhita, Chikitsa Sthana, Chapter 21, Visarpa Chikitsa, Verse 22 [10].
This combined-cause model is more clinically useful than attributing every outbreak to one food. A recurrence may follow fever, ultraviolet exposure, sleep deprivation, emotional strain, dental trauma, physical exhaustion or several factors occurring together. Some outbreaks arise without an identifiable trigger [1,8].
Nidana Parivarjana means avoiding factors that repeatedly aggravate the individual patient. A suspected trigger becomes more clinically meaningful when the same relationship appears across several outbreaks. A recurrence diary documenting sleep, illness, sunlight, stress, menstruation, food tolerance, lesion location and healing time can help distinguish consistent triggers from isolated coincidences.
Universal food prohibitions may lead to unnecessary fear, weight loss or nutritional deficiency. Dietary correction should be based on digestion, constitution, lesion stage, comorbidities and a reproducible relationship between a particular exposure and recurrence.
Ojas and Rasayana
Ojas represents the Ayurvedic concept of systemic vitality, stability and capacity to withstand or recover from physiological stress. Charaka describes the clinical picture associated with Ojas depletion:
Sanskrit
बिभेति दुर्बलोऽभीक्ष्णं ध्यायति व्यथितेन्द्रियः ।
दुश्छायो दुर्मना रूक्षः क्षामश्चैवौजसः क्षये ॥७३॥
Transliteration
bibheti durbalo’bhīkṣṇaṃ dhyāyati vyathitendriyaḥ |
duśchāyo durmanā rūkṣaḥ kṣāmaścaivaujasaḥ kṣaye ||73||
Translation
When Ojas is depleted, the person becomes fearful, weak and persistently preoccupied, with disturbed senses, poor complexion, low mood, dryness and emaciation.
Text reference: Charaka Samhita, Sutra Sthana, Chapter 17, Kiyanta Shiraseeya Adhyaya, Verse 73.
Ojas should not be equated with an HSV IgG value, white-blood-cell count, viral load or a single immune biomarker. It is a broader clinical assessment of strength, recovery, nourishment, sleep, mental steadiness and resistance to repeated physiological strain.
A patient whose outbreaks repeatedly follow severe fatigue, prolonged sleep disturbance or recovery from another illness may show reduced clinical resilience. Persistent weakness, unintended weight loss, repeated infections or delayed healing nevertheless requires investigation for nutritional deficiency, diabetes, endocrine disease, medication effects, immune suppression and other medical causes.
Rasayana is introduced after assessing the active disease stage, Agni, tissue condition and patient strength. Charaka describes its broader restorative objective:
Sanskrit
दीर्घमायुः स्मृतिं मेधामारोग्यं तरुणं वयः ।
प्रभावर्णस्वरौदार्यं देहेन्द्रियबलं परम् ॥७॥
वाक्सिद्धिं प्रणतिं कान्तिं लभते ना रसायनात् ।
लाभोपायो हि शस्तानां रसादीनां रसायनम् ॥८॥
Transliteration
dīrgham āyuḥ smṛtiṃ medhām ārogyaṃ taruṇaṃ vayaḥ |
prabhāvarṇasvaraudāryaṃ dehendriyabalaṃ param ||7||
vāksiddhiṃ praṇatiṃ kāntiṃ labhate nā rasāyanāt |
lābhopāyo hi śastānāṃ rasādīnāṃ rasāyanam ||8||
Translation
Through Rasayana, a person obtains longevity, memory, intellect, health, youthfulness, lustre, healthy complexion, excellence of voice and superior strength of the body and senses. Rasayana is the means of attaining the optimal qualities of Rasa and the subsequent tissues.
Text reference: Charaka Samhita, Chikitsa Sthana, Chapter 1, Rasayana Adhyaya, Abhaya-Amalakiya Rasayana Pada, Verses 7–8.
In recurrent cold sores, Rasayana is considered for restoration between outbreaks rather than used as an automatic response to every active blister. A hot, rapidly inflamed or infected lesion may require initial control of the acute stage before nourishing or rejuvenative treatment is introduced.
The choice of Rasayana depends on digestive capacity, age, constitution, recurrence frequency, nutritional status, pregnancy, kidney and liver health, current medicines and the presence of other illnesses. The classical benefits of Rasayana should not be interpreted as a direct textual claim that a specific formulation eradicates HSV-1 or HSV-2.
Individualized Clinical Interpretation
Two patients with confirmed oral HSV-1 may have different Ayurvedic patterns. One may experience infrequent sun-triggered lesions with strong digestion and rapid healing. Another may develop frequent outbreaks associated with insomnia, digestive disturbance, prolonged fatigue and slow tissue repair. The viral type may be identical, but the treatment priorities differ.
A Pitta-Rakta-dominant active lesion may require attention to burning, redness, heat and inflammatory sensitivity. A Vata-associated presentation may show prominent tingling, sharp pain, dryness or cracking. Kapha involvement may become relevant when swelling, heaviness, thick discharge or delayed resolution is present. Mixed patterns require treatment that addresses the dominant features without worsening the secondary Doshas.
The assessment should include the exact lesion site, first infection or recurrence, prodromal symptoms, number of annual episodes, healing time, known triggers, genital symptoms, eye symptoms, pregnancy, diabetes, eczema, immune suppression and previous treatment response. A patient with a previously confirmed cold sore may later develop an unrelated pimple, fungal fissure, bacterial infection or contact reaction, so each changed presentation requires fresh examination.
Ayurvedic treatment can address the patient’s inflammatory pattern, digestion, recurrence triggers, sleep, stress and recovery capacity. Virological testing remains necessary when the diagnosis is uncertain, and urgent medical care takes priority when lesions involve the eye, affect a newborn, become widespread, cause dehydration or occur in a significantly immunocompromised patient.
Can Herpes Be Cured Permanently?

Yes within the Ayurvedic curative model, the goal is complete clinical recovery together with objective laboratory improvement. Treatment is not considered complete when one cold sore dries or one genital ulcer disappears. It continues until outbreaks stop, tingling and burning resolve, the affected skin or mucosa becomes normal, the patient remains stable without repeated suppressive medicine, and serial HSV reports show measurable change.
Dr Arjun Kumar’s documented self-case shows that this outcome is possible. His HSV-1 IgG and HSV-2 IgG reports were positive before treatment. The values increased during the second month, but after continuing the individualized Ayurvedic protocol, both HSV-1 and HSV-2 IgG entered the laboratory-negative reference range during the third month. The complete sequence was shown through direct access to the original Tata 1mg laboratory account using private mobile-number and OTP authentication, rather than through selected screenshots alone [28]. Panaceayur
Modern Medicine Controls Herpes but Does Not Cure It
Modern medicine currently has no approved treatment that removes latent HSV from sensory nerve cells. Doctors usually prescribe acyclovir, valacyclovir or famciclovir during the first episode, at the beginning of a recurrence or as daily suppressive treatment.
These antiviral medicines can shorten the present outbreak, reduce pain, lower the frequency of recurrences during treatment and reduce transmission risk in selected patients. However, official treatment guidance states that systemic antiviral drugs do not eradicate latent HSV and do not permanently change the risk or severity of recurrence after treatment is stopped [1,4]. World Health Organization
This is why many patients enter the same cycle: an outbreak appears, antiviral medicine is taken, the lesion heals, the medicine is stopped and the symptoms return months or years later. The treatment controls active viral replication, but the patient may remain dependent on episodic or daily suppression.
Patients are also commonly reassured that herpes is widespread. Approximately 3.8 billion people under 50 years of age, representing 64% of that population, have HSV-1. Approximately 520 million people aged 15–49, or 13%, have HSV-2. An estimated 205 million people aged 15–49 experienced at least one symptomatic genital-herpes episode during 2020 [1,7]. World Health Organization
Being common does not mean that herpes is harmless or that repeated suffering should simply be accepted. Prevalence statistics do not resolve recurrent blisters, genital burning, painful urination, nerve discomfort, relationship anxiety, fear of infecting a partner, pregnancy concerns or continued dependence on suppressive medication.
HSV can also cause more than oral or genital sores. Rare complications include herpetic keratitis affecting the eye, encephalitis affecting the brain, meningoencephalitis, disseminated infection and serious neonatal herpes. HSV-2 infection is also associated with an approximately threefold greater risk of acquiring HIV after exposure [1]. World Health Organization
How Ayurveda Approaches Cure
Ayurveda does not treat herpes as only a surface blister. It treats the active lesion, the recurrence pattern and the wider physiological weakness that allows repeated reactivation.
During the active stage, treatment addresses burning, itching, redness, swelling, pain, fluid-filled blisters, ulceration and tissue irritation. A hot, red and burning presentation may show greater Pitta-Rakta involvement. Tingling, electric sensations, shooting pain, dryness or fissuring may indicate associated Vata and Majja involvement. Swelling, moisture, itching and slow healing may indicate Kapha participation.
After the lesion heals, treatment continues because surface healing is only the first stage. The physician evaluates recurrence frequency, prodromal tingling, nerve symptoms, digestion, bowel function, sleep, physical exhaustion, emotional stress, hormonal changes, fever, sunlight exposure and other conditions that repeatedly precede an outbreak.
Agni refers to digestive and metabolic capacity. When the patient has constipation, acidity, bloating, poor appetite or irregular bowel movements, these problems are corrected so that the prescribed medicines can be absorbed and tolerated properly.
Ojas refers to systemic vitality and resilience. It is assessed through strength, sleep, nutritional status, recovery after illness, stress tolerance and the patient’s ability to remain stable during circumstances that previously triggered recurrence.
The Ayurvedic objective is to break the cycle of outbreak, temporary suppression and recurrence. The treatment is continued through inflammatory control, neurological recovery, Rasayana therapy and consolidation until the previous clinical pattern no longer returns.
Dr Arjun Kumar’s Live Laboratory Reports
The most important laboratory evidence presented in the main article is Dr Arjun Kumar’s three-month positive-to-negative HSV report sequence.
The documented sequence began with positive HSV-1 IgG and HSV-2 IgG reports. During the second month, the values increased rather than immediately falling. The treatment was not stopped because the clinical protocol was designed to continue beyond early symptom improvement.
During the third month, both HSV-1 IgG and HSV-2 IgG entered the negative reference range stated by the reporting laboratory. The reports retained the test names, collection dates, numerical values and laboratory interpretations [28]. Panaceayur
The reports were demonstrated through an OTP-verified video in which the original Tata 1mg laboratory account was opened directly. The video shows the positive baseline reports, the intermediate increase and the final laboratory-negative HSV-1 and HSV-2 IgG results in chronological order.
This is not only a claim that the patient felt better. It is a documented clinical sequence supported by original serial laboratory reports. The outcome included the disappearance of visible lesions, burning, itching, tingling, nerve pain and the earlier recurrence pattern, together with both HSV IgG reports entering the laboratory-negative range.
Where HSV DNA PCR is clinically appropriate, the curative model also looks for an undetectable result from the correct specimen. Laboratory findings are assessed together with the absence of lesions, prodromal symptoms, neural discomfort and recurrence rather than judging recovery only by the appearance of the skin.
Published Ayurvedic Case Evidence

Published clinical evidence also supports the ability of Ayurvedic treatment to heal active genital-herpes lesions.
A 2025 clinical case report described a 27-year-old woman with recurrent genital herpes, itching, rashes, vesicles, redness, swelling and vaginal discharge. The Ayurvedic protocol included internal medicines together with Yoni Prakshalana and Yoni Pichu. Serial clinical photographs documented the condition before treatment, during treatment and after treatment.
The authors reported visible healing of the lesions and resolution of the presenting signs and symptoms after approximately eight days of combined treatment [27]. Jaims
The local cleansing decoction contained Haridra, Guduchi and Manjistha. Jatyadi Taila was used for Yoni Pichu, while the internal treatment included Chandraprabha Vati, Arogyavardhini Vati and medicines selected for urinary symptoms, tissue healing and constipation.
This published case demonstrates rapid clinical and photographic recovery, while Dr Arjun Kumar’s documented self-case adds serial HSV-1 and HSV-2 IgG positive-to-negative laboratory evidence. Together, they support both the visible clinical response and the need for longer treatment when laboratory recovery is also the objective.
Nimba Amritadi Avaleha and the Curative Protocol
The principal medicine used in the curative model is an individualized, clinician-developed Nimba Amritadi Avaleha. It is prepared according to the patient’s HSV type, symptom location, disease duration, outbreak frequency, digestion, bowel function, nerve symptoms, associated illnesses, previous antiviral use and baseline laboratory reports.
The formulation is not designed merely to dry a cold sore. It is designed to address active inflammation, recurrent neural symptoms, Rakta-Pitta disturbance, impaired Agni, reduced Ojas and the tendency toward repeated reactivation.
Nimba forms a central part of the formulation when itching, burning, recurrent lesions and Rakta involvement are prominent. Guduchi is selected for Rasayana support, recovery and immune regulation. Haridra and Daruharidra are included according to inflammatory and tissue findings. Manjistha and Sariva are used when Rakta-Pitta features such as redness, heat and burning dominate.
Bhumyamalaki, Amalaki, Yashtimadhu, Patola, Khadira and Triphala may be added according to liver function, digestion, mucosal sensitivity, bowel pattern and general resilience. Yashtimadhu is particularly considered when oral or genital mucosal irritation requires soothing and tissue-recovery support.
Gandhak Rasayana may be added in recurrent inflammatory and skin-dominant presentations. In selected chronic or resistant cases, carefully prepared Swarna Bhasma, Rajata Bhasma, Abhraka Bhasma and other physician-selected Rasayana medicines may be incorporated after reviewing age, kidney function, liver function, metabolic health and concurrent medication.
The strength of the protocol does not come from adding the greatest number of ingredients. It comes from changing the formulation according to the patient’s disease stage and clinical pattern. A patient with active burning and ulcers requires a different balance from an asymptomatic HSV-positive patient with no visible lesions, or a patient whose main complaints are sacral pain, tingling, pelvic sensitivity and disturbed sleep.
The first phase focuses on active symptoms, inflammation, digestion and bowel correction. The second phase focuses more deeply on recurrence, Vata-Majja symptoms and Rasayana. The final phase consolidates recovery and follows the patient through circumstances that previously triggered outbreaks.
How Cure Is Documented
In this Ayurvedic model, cure is documented through clinical recovery and laboratory recovery occurring together.
Clinical recovery means complete healing of the lesions, disappearance of burning, itching, tingling and nerve pain, restoration of normal oral or genital tissue and sustained freedom from the previous outbreak pattern.
Systemic recovery means stable digestion, regular bowel function, improved sleep, better energy and greater stability during illness, stress, menstruation, travel, physical exhaustion or other former triggers.
Laboratory recovery means following the original positive HSV reports through serial testing until the values enter the negative reference range. When a clinically appropriate HSV DNA PCR is performed, an undetectable result adds further objective support.
The strongest documented outcome is a positive baseline, individualized treatment, complete symptom resolution, no recurrence, HSV IgG entering the laboratory-negative range and continued stability without repeated suppressive medication.
The full evidence, live report sequence, published case study, treatment stages, ingredients, Nimba Amritadi Avaleha protocol and laboratory follow-up are explained in Can Herpes Be Cured Permanently? Real Cure Approach.
Ayurvedic Diet for Cold Sores and Herpes

In cold sores vs herpes, diet is an essential part of Ayurvedic treatment because the wrong food can intensify burning, redness, itching, blistering and ulceration. HSV is a viral infection, but the severity of an active outbreak can be influenced by the patient’s Pitta-Rakta state, digestion, body type, sleep, heat exposure and individual triggers [1,8,10].
During an active Pitta-dominant outbreak, foods that are hot by nature, sharply pungent, sour, salty, fermented or served very hot should be completely avoided until the burning, redness, blisters and ulcers have settled.
This restriction is especially important when the lesion feels hot, red, swollen, intensely itchy, tender or burning. The diet should then remain cooling, freshly prepared, mildly seasoned and easy to digest. After the active stage has resolved, foods should be reintroduced according to the patient’s Prakriti, current imbalance and personal recurrence pattern.
Why Heating Foods Must Be Avoided
Ayurveda distinguishes between the temperature of food and its internal potency. A food may be served cold but still have Ushna, or heating, properties. Chilli, mustard, alcohol, sour fermented foods and strong spices can therefore aggravate Pitta even when they are not physically hot.
Very hot tea, soup or freshly cooked food can directly irritate an oral lesion. Heating foods can also increase the patient’s sensation of burning, redness, thirst, acidity and inflammatory discomfort. A person with a hot, red and blistering outbreak should not continue such foods simply because they are considered healthy in another context.
Charaka Samhita, Chikitsa Sthana, Chapter 21, Visarpa Chikitsa describes the aggravation of Pitta through heating regimens and burning or sour foods [10]. This classical principle does not mean that these foods create HSV. It means that they may intensify a heat-dominant inflammatory pattern after the virus has already been acquired.
The first dietary rule during an active cold sore or genital-herpes outbreak is to stop adding heat to an already heated Pitta-Rakta condition.
Pungent and Spicy Foods to Stop
Red chilli, green chilli, chilli flakes, cayenne pepper, hot paprika, chilli sauce and spicy chutneys should be stopped completely during active burning, blistering or ulceration. Even a small amount may cause immediate stinging when the lesion involves the lips or mouth.
Black pepper, long pepper, mustard seeds, mustard sauce, strong ginger preparations, garlic, raw onion, radish, horseradish and heavily spiced masala mixtures are also heating. They may be useful in some Kapha-dominant conditions, but they are not suitable during a strongly inflamed Pitta-Rakta outbreak.
Spicy restaurant food, curries containing large amounts of chilli, hot pickles, peri-peri sauces, barbecue sauces and heavily seasoned fast food should be avoided. Removing visible chilli pieces is not sufficient when the entire preparation has been cooked with strong spices.
Fresh coriander, small amounts of fennel, cardamom and mild cumin may be better tolerated, but even mild spices should be reduced when the mouth is ulcerated or extremely sensitive. The patient should use the minimum seasoning needed for digestion and taste.
Sour and Acidic Foods to Stop
Lemon, lime, grapefruit, sour oranges, concentrated citrus juices, tamarind, vinegar and sour fruit concentrates should be avoided during the active phase. They can sting an open oral lesion and may aggravate sourness, heat and burning in a Pitta-dominant patient.
Citric acid added to packaged drinks, candies, sauces, supplements and preserved foods may also irritate sensitive oral or genital tissue. Patients should read ingredient labels rather than assuming that only fresh citrus fruit is relevant.
Tomato, tomato ketchup, sour tomato sauces and heavily concentrated tomato gravies may increase irritation in patients with active burning or acidity. The response varies, but they should be removed temporarily when they clearly worsen symptoms.
Sour curd, yogurt, buttermilk made from very sour curd, aged cheese and fermented dairy products should be stopped during an intensely hot outbreak. Fresh non-sour preparations may be considered later according to digestion and body type.
Pickles, vinegar-preserved vegetables, kombucha, sour fermented drinks, fermented sauces and strongly fermented foods should also be avoided. Their sour and heating nature can aggravate Pitta in susceptible patients.
Amalaki has a sour taste but is traditionally considered cooling in potency. It should still be used carefully when there is an open oral ulcer because the sour taste may cause local stinging. It is better included through a properly designed formulation than taken as a concentrated sour juice during an active mouth lesion.
Excess Salt and Processed Foods
Excessive salt may aggravate burning, thirst, swelling and local irritation. Highly salted snacks, chips, salted nuts, instant noodles, packaged soups, papad, preserved foods, processed meats and ready-made sauces should be avoided during an active episode.
Pickles combine salt, sourness, oil and strong spices, making them particularly unsuitable for a hot Pitta-Rakta presentation. Even small quantities can prolong oral burning in a sensitive patient.
Deep-fried foods, repeatedly heated oils, fast food, greasy snacks and stale leftovers can impair digestion and increase heaviness. Poor digestion may reduce tolerance to medicines and make the overall treatment more difficult.
Smoked, charred, heavily grilled and barbecue-style foods should also be avoided when they are dry, spicy, salty or intensely heated. Food should be freshly prepared and cooked without excessive browning or burning.
Alcohol, Smoking and Stimulants
Alcohol should be completely avoided during an active outbreak. Wine, beer and spirits are heating, dehydrating and capable of worsening redness, burning, sleep disturbance and poor dietary control. Alcohol may also interfere with prescribed medicines and increase the likelihood of missed doses.
Smoking, vaping and tobacco use irritate the lips, mouth and respiratory mucosa. Smoke exposure can worsen dryness, delay tissue repair and increase local discomfort. Tobacco should not be used as a method of stress relief during an outbreak.
Coffee, energy drinks and very strong tea may aggravate heat, acidity, restlessness and sleep disruption in Pitta-sensitive patients. Patients who notice a consistent connection between caffeine and outbreaks should stop or substantially reduce it.
Very hot tea, coffee, soup and herbal drinks should be allowed to cool before consumption. The patient should not repeatedly expose an oral lesion to steaming liquids merely because the beverage itself is considered medicinal.
Foods Commonly Discussed as High in Arginine
Many patients focus only on lysine and arginine. Chocolate, cocoa, peanuts, almonds, walnuts, sesame seeds, sunflower seeds, pumpkin seeds and some protein powders are commonly restricted because of their arginine content.
Ayurveda does not plan the entire diet from one amino-acid ratio. The patient’s digestion, lesion stage, Pitta level, strength, body type and personal trigger pattern are equally important. A food that repeatedly precedes an outbreak in one patient may not create the same response in another.
Chocolate is usually unsuitable during an active Pitta outbreak because it may combine cocoa, sugar, caffeine, dairy and a heating or stimulating effect. It should be stopped when the patient has burning, acidity, disturbed sleep or a clear history of chocolate-associated recurrence.
Peanuts and heavily roasted or salted nuts may be heating, oily, difficult to digest and high in salt. They should be avoided during an active hot outbreak. Almonds, walnuts and seeds should not necessarily be removed permanently, but they may be reduced temporarily when the patient has a consistent clinical association or poor digestion.
Sesame is considered heating and is generally unsuitable during a strong Pitta-Rakta flare. Sesame oil, sesame sweets and large quantities of sesame seeds should therefore be avoided during active burning and blistering.
Protein powders containing large amounts of nuts, seeds, chocolate flavouring, artificial acids, sweeteners or stimulants should be reviewed carefully. They should not be continued automatically because they are marketed as healthy.
Lysine and arginine can be considered, but they should not replace a complete Ayurvedic assessment of Pitta, Rakta, Agni, Ojas, Prakriti and current symptoms.
Foods That Are Usually Better Tolerated
During an active outbreak, food should be fresh, mildly seasoned, soft and comfortably warm rather than steaming hot or ice-cold. The purpose is to nourish the patient without increasing burning or weakening digestion.
Plain rice, soft rice preparations, oats, wheat preparations when tolerated and well-cooked mung dal may provide gentle nourishment. Mung is generally lighter than many other pulses and can be cooked with coriander, fennel or a small quantity of mild cumin.
Bottle gourd, ridge gourd, ash gourd, zucchini, pumpkin, green beans and other mild vegetables may be used according to digestion. Vegetables should be cooked until soft when oral lesions make chewing painful.
Cucumber may be cooling, but a patient with weak digestion or bloating may tolerate lightly cooked vegetables better than large amounts of raw salad. A cooling diet should not become an entirely raw diet.
Sweet pomegranate, ripe pear, melon and soaked raisins may be suitable for some patients. Very sour fruit should be avoided. Fruit should not be taken in excessive quantities or mixed indiscriminately with heavy meals when digestion is weak.
Coconut water may help hydration in selected patients, particularly during heat exposure, but it must be used carefully in kidney disease, electrolyte disorders or when the treating clinician has restricted fluid or potassium intake.
A small quantity of ghee may support lubrication and reduce excessive dryness when digestion is stable. It should not be used in excess in patients with heaviness, nausea, poor appetite, uncontrolled metabolic disease or a Kapha-dominant pattern.
Fresh milk may be suitable for some Pitta-dominant patients when it is well tolerated, but it should not be combined with sour fruit, salty food or incompatible preparations. Patients with lactose intolerance, congestion, poor digestion or metabolic concerns may require a different option.
Natural sweet taste can help calm Pitta, but this does not justify eating refined sugar, sweets, desserts or sweetened beverages in large quantities. Excess sugar may aggravate Kapha, impair metabolic control and reduce the nutritional quality of the diet.
Water should be taken regularly at room temperature or slightly cool. Ice-cold drinks may temporarily numb burning but can disturb digestion in susceptible patients. Hydration should be steady rather than excessive.
Diet According to Body Type
The same herpes diet should not be given to every patient. Prakriti, the person’s constitutional body type, and Vikriti, the current imbalance, must both be considered.
A Pitta-dominant patient usually requires the strictest control of chilli, alcohol, fermented foods, sour fruit, vinegar, pickles, excess salt, coffee and intense sun exposure. Cooling, mildly sweet, bitter and non-irritating foods are generally better tolerated.
A Vata-Pitta patient may have burning together with dryness, cracking, anxiety, irregular appetite or constipation. This patient should avoid heating foods but should not be placed on a cold, dry or highly restrictive diet. Soft, moist, freshly cooked and warm-but-not-hot food is usually more suitable than raw salads, dry snacks or prolonged fasting.
A Kapha-Pitta patient may show burning together with swelling, heaviness, excessive moisture, slow healing or metabolic concerns. The food should remain cooling but also light. Heavy dairy, fried foods, excess sweets, large portions and oily preparations may worsen the Kapha component.
A predominantly Vata or Kapha patient may still develop a temporary Pitta-Rakta outbreak. The active diet should first calm the current heat. Once the lesion heals, the diet should gradually return toward the person’s constitutional needs so that digestion, strength and bowel function are not weakened.
The current outbreak pattern is more important than the body-type label alone. A Pitta person may occasionally show dryness and weakness, while a Vata person may experience a strongly burning and inflamed lesion. Diet should follow the patient who is present, not only the questionnaire result.
Patients can identify their likely constitutional pattern through the Prakriti Analysis Questionnaire and use it as a starting point for planning food choices. The result should then be matched with current symptoms, digestion, medical conditions and the treatment prescribed by the Ayurvedic physician.
Lifestyle Heat That Must Also Be Avoided
Food alone will not control Pitta if the patient continues to create excessive heat through daily activities. Prolonged direct sunlight, tanning, sauna, steam rooms, very hot showers and excessive heat exposure should be avoided during an active outbreak.
Intense exercise, overheating and dehydration can worsen burning and fatigue in susceptible patients. Gentle activity may continue when the patient feels well, but strenuous training should be reduced when the lesion is painful or the body is already exhausted.
Late nights and insufficient sleep should be corrected. Sleep disturbance is a common clinical trigger in recurrent cold sores, particularly when combined with travel, stress, alcohol or poor food habits [1,8].
Excessive anger, mental overwork and continuous emotional stimulation may intensify Pitta symptoms in some patients. This does not mean that emotions caused HSV. It means that sustained stress and sleep disruption may contribute to a recurrence pattern in a person who already carries the virus.
Sexual contact, kissing and oral sex should be avoided from the first tingling sensation until the lesion has fully healed. Diet may reduce aggravation, but it does not make an active lesion immediately noncontagious [1,2,4].
How Long the Restrictions Should Continue
The strict Pitta-reducing diet should continue throughout tingling, burning, redness, blistering, ulceration and early crusting. Foods should not be reintroduced merely because pain has reduced for one day.
Once the lesion is fully healed and the skin or mucosa has returned to normal, foods may be reintroduced gradually according to Prakriti and digestion. A patient should not immediately return to chilli, alcohol, pickles and fermented food after completing treatment.
Long-term restriction should be based on repeated observation. A food that precedes several outbreaks deserves greater attention than a food eaten once before one episode. Patients should record meals, sleep, stress, sunlight, menstruation, illness and lesion development to identify consistent triggers.
Permanent extreme restriction is not the aim. Removing too many foods can cause inadequate protein intake, weight loss, fatigue, constipation and anxiety around eating. The Ayurvedic objective is to remove aggravating foods while preserving adequate nourishment and digestive strength.
Diet is not a minor addition to Ayurvedic herpes treatment. It is part of the treatment because daily food can either repeatedly aggravate Pitta-Rakta or support the medicines in calming the outbreak and preventing recurrence.
Modern Treatment: Suppression Only

Antiviral Drugs Are the Primary Approach
In modern medicine, herpes is treated primarily through antiviral medications, which aim to suppress viral replication and reduce the severity and duration of outbreaks. The most commonly prescribed drugs include Acyclovir, Valacyclovir, and Famciclovir. These can be administered during active outbreaks (episodic treatment) or taken daily to prevent recurrences (suppressive therapy) [7]
These medications work by interfering with the viral DNA polymerase enzyme, slowing the replication of HSV in the body. However, they do not eliminate the virus from the nerve ganglia, where it remains latent. Once medication is stopped, the virus can reactivate under stress, fatigue, or immune suppression [21].
Limitations of Antiviral Therapy
Despite being effective in reducing symptoms, antiviral medications do not cure herpes. They have several key limitations:
- Latency remains untouched: The virus hides in the dorsal root ganglia (nerve clusters), which antivirals cannot access.
- Viral resistance risk: Long-term use can lead to resistant HSV strains, particularly in immunocompromised patients [22].
- Side effects: These include nausea, headaches, fatigue, and in some cases, kidney stress (especially with high doses of acyclovir).
- Cost and accessibility: Continuous suppressive therapy becomes financially and emotionally draining for many patients.
Ayurvedic Critique of Symptom-Based Suppression
From an Ayurvedic perspective, merely suppressing symptoms without addressing the root cause is incomplete treatment. Herpes is seen as a Rakta–Pitta–Ojas disorder involving viral load buildup, immune compromise, and tissue-level weakness.
Classical texts criticize treatments that “cool the fire without removing the fuel”—that is, temporarily reducing inflammation (blisters) while leaving behind the root pathology (viral latency and poor immunity). Modern antiviral suppression is akin to Avrana Chikitsa—masking the disease but not destroying its seed (Beeja) [23].
Integration Is Needed
While modern antivirals may play a role in emergency relief or in immunocompromised individuals, true long-term management requires a root-cause strategy. This is where Ayurveda excels—by combining detoxification (Shodhana), antiviral herbs (Krimighna Dravyas), Rasayana therapy, and Ojas restoration to attempt viral eradication rather than lifelong drug dependence.
Long-Term Complications if Herpes Is Left Untreated
The Silent Progression of Viral Latency
Herpes simplex virus is often underestimated because many of its carriers remain asymptomatic. However, chronic latency without appropriate intervention—especially immune-restorative or antiviral detoxification—can allow the virus to progressively impact multiple organ systems. Unlike acute infections, HSV quietly resides in the nerve ganglia, reactivating under specific triggers. If untreated, these subclinical reactivations accumulate over time, leading to immunological fatigue, inflammation, and degeneration of key bodily tissues. This risk is particularly elevated in those with compromised immunity, hormonal imbalances, stress-induced exhaustion, or poor metabolic resilience.
Chronic Reactivation and Neural Involvement
One of the most overlooked consequences of untreated herpes is cumulative nerve involvement, especially in cases of genital HSV-2. Each reactivation episode involves the sacral or trigeminal ganglia, and repeated inflammatory cycles eventually begin to damage the nerve pathways themselves. This leads to neurogenic pain, burning sensations along the sciatic or pelvic nerves, and persistent hypersensitivity of the skin, known in clinical settings as post-herpetic-like neuralgia. Patients may experience phantom tingling, cold flashes, or crawling sensations without any visible sores. From an Ayurvedic view, this reflects progressive Majja Dhatu Dushti and Vata-predominant vitiation of Majjavaha Srotas, a condition requiring deep Rasayana and neuro-restorative therapy.
Ocular Herpes and Herpetic Keratitis
When HSV reactivates in the ophthalmic branch of the trigeminal nerve, it can invade the eye, causing herpes simplex keratitis. This leads to corneal ulcers, inflammation, and if recurrence continues, irreversible corneal scarring and partial or full blindness. Herpetic eye disease is one of the most common causes of infectious vision loss in developed countries. From an Ayurvedic perspective, this is understood as Alochaka Pitta Dushti in combination with Rakta Dhatu aggravation, leading to progressive degeneration of Drishti Srotas unless pacified and regenerated through targeted therapies.
Encephalitis, Aseptic Meningitis, and Central Nervous System Impact
Though rare, untreated herpes can cross into the central nervous system, especially during immune suppression, leading to herpes simplex encephalitis—a severe, potentially fatal condition that causes brain inflammation. More commonly, HSV-2 can cause chronic aseptic meningitis, particularly in women. Even in non-severe cases, long-standing HSV latency is increasingly associated with cognitive fatigue, memory loss, mood swings, and impaired mental focus, mimicking symptoms seen in chronic fatigue syndrome or autoimmune encephalopathy. In Ayurveda, such CNS complications are classified under Sannipata Jwara, Manovaha Srotas Dushti, and Majja-Sara Kshaya, indicating deep degenerative states affecting both mind and memory.
Reproductive Health Disruption and Sexual Dysfunction
In untreated genital herpes, the reproductive system gradually deteriorates under the burden of chronic inflammation, viral shedding, and tissue scarring. Women may experience cervical inflammation (herpetic cervicitis), pelvic pain, vaginal dryness, and even secondary infertility due to a hostile uterine environment. In men, recurrent episodes may mimic chronic prostatitis, with groin discomfort, pain after ejaculation, reduced libido, and erectile hesitation. These symptoms may arise even in the absence of visible sores, reflecting deep Shukra Dhatu Dushti and disturbed Shukravaha Srotas, leading to both physical and psychosexual trauma. If left uncorrected, this results in depleted Ojas, poor reproductive vigor (Beeja Shakti), and marital stress.
Viral Burden and Chronic Immune Suppression
HSV infection is not static—it modulates the immune system, keeping the host in a state of chronic low-grade inflammation. Over time, this weakens Vyadhikshamatva (disease resistance) and opens the door to co-infections such as Epstein-Barr Virus (EBV), Cytomegalovirus (CMV), Candida, HPV, or even opportunistic bacterial infections. Many untreated patients eventually report fatigue, hair loss, poor wound healing, and a slow recovery from other illnesses. This reflects Rasa, Rakta, and Ojas depletion, the hallmark of chronic viral invasion in classical Ayurvedic pathology. Additionally, HSV increases the risk of HIV acquisition and transmission, as the mucosal barrier is compromised and immune surveillance is diminished.
Psychological Toll and Emotional Isolation
The psychosocial impact of untreated herpes is profound. Patients often carry hidden shame, anxiety over disclosure, and fear of rejection in intimate relationships. The chronic anticipation of outbreaks, along with the invisible burden of transmission, creates long-term emotional exhaustion. In Ayurveda, this would be categorized under Satva Kshaya (loss of mental clarity), Rajo Dushti, and Manas Roga (emotional disorders). Without addressing this emotional dimension, even the best herbal treatments may fail to yield full results, as the body-mind axis (Deha–Manas Samyoga) is fractured.
Ayurvedic Conclusion
If left untreated, herpes transitions from a localized viral condition to a multi-systemic pathology affecting Dhatu layers, immune intelligence, neurological integrity, and reproductive strength. This progression aligns with the Ayurvedic concept of Vyadhi Sankara—a convergence of multiple disorders arising from a single neglected root cause. For true recovery, the patient must undergo a multi-tiered intervention—cleansing viral residues (Shodhana), rebuilding tissue quality (Rasayana), correcting mind-body connection (Satvavajaya), and restoring immune sovereignty (Ojas Uttejana).
Frequently Asked Questions (FAQs)
What is the difference between a cold sore and herpes?
Cold sores are small fluid-filled blisters that typically form around the mouth and lips, most often caused by herpes simplex virus type 1 (HSV-1). The term herpes is a broader classification for infections caused by either HSV-1 or HSV-2, affecting both oral and genital areas. In essence, a cold sore is a form of herpes. The confusion stems from the fact that oral herpes is socially accepted while genital herpes is stigmatized, despite both originating from the same viral family.
Can HSV-1 cause genital herpes?
Yes, HSV-1 can cause genital herpes through oral-genital contact. In recent years, more first-time genital herpes infections, especially among young adults, are caused by HSV-1. Though genital HSV-1 infections tend to recur less than HSV-2, the virus still remains latent in the nervous system and can be transmitted even without visible symptoms.
Is herpes considered an STD or STI?
Yes, herpes is considered a sexually transmitted infection (STI) when spread through sexual contact. HSV-2 is almost always sexually transmitted, while HSV-1 can be spread non-sexually in early life through kissing or shared items. Ayurveda, however, does not classify disease by transmission route, but by internal pathology, viewing both oral and genital herpes as signs of systemic imbalance.
Can I have herpes and not know it?
Yes, most people with herpes are unaware they are infected because they either have no symptoms or their symptoms are mild and mistaken for something else. This contributes to unintentional spread, especially through asymptomatic viral shedding. The virus can stay dormant for years and reactivate later.
How accurate are herpes blood tests?
5.
Blood tests like IgG can indicate past exposure to HSV-1 or HSV-2 but cannot pinpoint where or when the infection occurred. IgM tests are not reliable and can produce false positives. DNA PCR testing, especially from blood samples, is currently the most accurate method, detecting active virus and differentiating between HSV-1 and HSV-2 even without symptoms.
What triggers herpes outbreaks?
Common triggers include physical or emotional stress, fever, menstruation, sun exposure, and alcohol or overheating. In Ayurveda, these factors aggravate Vata and Pitta Doshas, disturb Rakta Dhatu, and weaken Ojas, allowing the latent virus to reactivate.
Can herpes be cured permanently?
In modern medicine, there is no permanent cure. Antiviral medications manage symptoms but cannot remove the virus from the nervous system. Ayurveda treats herpes as a terrain imbalance and uses a structured approach involving Shodhana (cleansing), Rasayana (rejuvenation), and Ojas restoration. With this approach, many patients report complete symptom resolution and negative PCR results.
Are antiviral medications safe long-term?
Long-term antiviral use can lead to kidney burden, elevated liver enzymes, digestive issues, and drug resistance. These medicines only suppress symptoms without improving immune defense, and outbreaks often return when the medication is stopped. Ayurveda takes a different approach by improving the immune system and body’s resilience to prevent recurrence naturally.
Can herpes affect fertility or pregnancy?
Yes, recurring genital herpes in women can cause cervical inflammation, reduce sperm penetration, and increase the risk of miscarriage or transmission to the baby. In men, it may cause prostatitis-like symptoms, low libido, and poor semen quality. In Ayurveda, this is understood as Shukra Dhatu Dushti and Beeja Kshaya, both treatable with Rasayana herbs and minerals.
Is Panchakarma mandatory for herpes treatment in Ayurveda?
No, Panchakarma is not mandatory. It is recommended when there is high toxin accumulation or chronic recurrence, but patients can also recover with Rasayana therapy, antiviral herbs, and tailored lifestyle guidance. Even without detox, structured herbal protocols can offer full results when applied correctly.
References
[1] World Health Organization. (2025, May 30). Herpes simplex virus. WHO fact sheet
Brief: Covers global HSV prevalence, oral and genital transmission, asymptomatic shedding, recurrent symptoms, recognised triggers and complications. Provides estimates of HSV-1, HSV-2 and symptomatic genital-herpes burden.
[2] Centers for Disease Control and Prevention. (2024, February 20). About genital herpes. CDC
Brief: Explains oral and genital herpes, oral-to-genital transmission, transmission without visible sores and partner counselling. Addresses misconceptions about transmission through everyday objects and activities.
[3] Centers for Disease Control and Prevention. (2024, February 20). Screening for genital herpes. CDC
Brief: Explains when testing is appropriate, the limitations of antibody tests, timing after exposure and the possibility of incorrect results when screening asymptomatic people.
[4] Centers for Disease Control and Prevention. (2021). Herpes: STI treatment guidelines. CDC treatment guidelines
Brief: Covers lesion PCR, viral culture, HSV typing, type-specific IgG, confirmation of low-positive HSV-2 results and the limitations of IgM and blood PCR. Also addresses episodic treatment, suppressive therapy and pregnancy management.
[5] National Institutes of Health. (2025, July 14). Herpes simplex virus: Adult and adolescent opportunistic infections. ClinicalInfo.HIV.gov. NIH guideline
Brief: Describes mucocutaneous HSV presentations, diagnostic testing and disease in immunocompromised patients. Explains the role of lesion PCR, central nervous system testing and blood PCR when disseminated infection is suspected.
[6] National Institute of Dental and Craniofacial Research. (n.d.). Fever blisters and canker sores. Retrieved November 5, 2026, from NIDCR
Brief: Explains differences between cold sores and canker sores, including location, appearance and contagiousness. Provides guidance on healing, painful eating, dehydration and precautions around the eyes.
[7] Harfouche, M., AlMukdad, S., Alareeki, A., Osman, A. M. M., Gottlieb, S., Rowley, J., Abu-Raddad, L. J., & Looker, K. J. (2025). Estimated global and regional incidence and prevalence of herpes simplex virus infections and genital ulcer disease in 2020: Mathematical modelling analyses. Sexually Transmitted Infections, 101(4), 214–223. PubMed
Brief: Provides modelled estimates of global HSV infection and genital-ulcer burden in 2020. These include approximately 3.8 billion HSV-1 infections, 520 million HSV-2 infections and 205 million people experiencing symptomatic genital herpes.
[8] Leung, A. K. C., & Barankin, B. (2017). Herpes labialis: An update. Recent Patents on Inflammation & Allergy Drug Discovery, 11(2), 107–113. PubMed
Brief: Reviews recurrent cold sores, prodromal symptoms, grouped lip lesions, diagnosis, viral shedding and early antiviral treatment. Discusses suppression for frequent or severe recurrences.
[9] Wang, M., Bai, J. Q. A., & Mukovozov, I. (2026). Treatments for recurrent herpes labialis: A systematic review of randomized controlled trials. Journal of Cutaneous Medicine and Surgery. Advance online publication. PubMed
Brief: Reviews randomised trials of treatments for recurrent herpes labialis. Supports discussion of treatment effectiveness, episodic care and recurrence management.
[10] Charak Samhita Research, Training and Skill Development Centre. (n.d.). Charaka Samhita online. Visarpa Chikitsa, Chikitsa Sthana, Chapter 21 · Rasayana Chikitsa, Chikitsa Sthana, Chapter 1 · Kiyanta Shiraseeya Adhyaya, Sutra Sthana, Chapter 17
Brief: Classical sources for the article’s discussion of Visarpa, Dosha and tissue involvement, Rasayana and Ojas. The supplied mapping identifies Chikitsa Sthana 21/11, 15, 20, 22 and 31, Chikitsa Sthana 1, Abhaya-Amalakiya Rasayana Pada 7–8, and Sutra Sthana 17/73.
[11] Mailoo, V. J., & Rampes, S. (2017). Lysine for herpes simplex prophylaxis: A review of the evidence. Integrative Medicine, 16(3), 42–46. PubMed
Brief: Reviews evidence on lysine supplementation for preventing HSV recurrences. Provides context for discussing lysine, arginine, study limitations and dietary approaches.
[12] Tiwari, V., Darmani, N. A., Yue, B. Y. J. T., & Shukla, D. (2010). In vitro antiviral activity of neem (Azadirachta indica L.) bark extract against herpes simplex virus type 1 infection. Phytotherapy Research, 24(8), 1132–1140. PubMed
Brief: Reports laboratory findings that an aqueous neem-bark extract interfered with HSV-1 attachment and entry into susceptible cells. Supports the experimental ingredient rationale for Nimba.
[13] Kutluay, S. B., Doroghazi, J., Roemer, M. E., & Triezenberg, S. J. (2008). Curcumin inhibits herpes simplex virus immediate-early gene expression by a mechanism independent of p300/CBP histone acetyltransferase activity. Virology, 373(2), 239–247. PubMed
Brief: Reports reduced HSV-1 infectivity and inhibition of immediate-early viral gene expression in cell culture. Provides experimental context for discussing curcumin and Haridra.
[14] Upadhyay, R., & Tiwari, K. N. (2023). The antiviral potential of Phyllanthus species: A systematic review. Archives of Virology, 168(7), Article 177. PubMed
Brief: Summarises experimental antiviral research involving Phyllanthus species, including HSV-1 and HSV-2. Discusses reported effects on viral entry and replication.
[15] Rakshithashree, G., Lavanya, S., & Nithin, S. A. (2025). Ayurvedic management of genital herpes: A clinical case study. Journal of Ayurveda and Integrated Medical Sciences, 10(9), 250–254. Journal article
Brief: Describes a recurrent genital presentation treated with internal medicines and local Ayurvedic procedures. The report includes serial clinical photographs and reported resolution of presenting lesions and symptoms.
[16] Kumar, A. (2026, September 6). Can herpes be cured permanently? Real cure approach. Panaceayur. Article and clinical documentation
Brief: Provides the author’s self-reported treatment history, serial HSV-1 and HSV-2 IgG results and embedded laboratory-account video. Serves as the primary source for the article’s internal case documentation and personalised treatment framework.
I. All Refrences
- World Health Organization. (2020). Herpes simplex virus. https://www.who.int/news-room/fact-sheets/detail/herpes-simplex-virus ↩
- Looker, K. J., Magaret, A. S., May, M. T., et al. (2015). Global and regional estimates of prevalent and incident herpes simplex virus type 1 infections in 2012. PLOS ONE, 10(10), e0140765. https://doi.org/10.1371/journal.pone.0140765. ↩
II. All Refrence
- Schiffer, J. T., & Corey, L. (2009). Rapid host immune response and viral dynamics in herpes simplex virus-2 infection. Nature Medicine, 15, 885–890. https://doi.org/10.1038/nm.1974 ↩
- Charaka Samhita. Chikitsa Sthana 7/21. (Shree Baidyanath Ayurveda Bhawan edition). ↩
- Bhavaprakasha Nighantu. Nija Rogadhikara. (Chaukhamba Krishnadas Academy edition). ↩
- Centers for Disease Control and Prevention. (2023). Genital herpes – CDC fact sheet. https://www.cdc.gov/std/herpes/stdfact-herpes.htm ↩
- Sauerbrei, A. (2016). Diagnosis, antiviral therapy, and resistance in herpes simplex virus infections. Therapeutic Advances in Infectious Disease, 3(4), 113–129. https://doi.org/10.1177/2049936116665262 ↩
- Freeman, E. E., Weiss, H. A., Glynn, J. R., Cross, P. L., Whitworth, J. A., & Hayes, R. J. (2006). Herpes simplex virus 2 infection increases HIV acquisition in men and women: systematic review and meta-analysis of longitudinal studies. AIDS, 20(1), 73–83. https://doi.org/10.1097/01.aids.0000198081.09337.a7 ↩
- Bhavaprakasha. Madhyama Khanda, Jwara Chikitsa. (Chaukhamba Bharati Academy edition). ↩





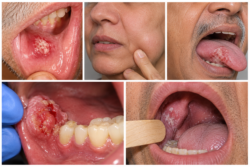
2 Responses
I took the information clear and the precautions i will follow them to keep my body safe from such diseases.thanks panaceayur
We’re truly glad to hear that you found the information clear and helpful. Following the right precautions is a powerful first step toward long-term health. If you ever need further guidance or support, we’re here to help you with personalized Ayurvedic care. Wishing you continued wellness and protection from all imbalances